Related Experiment Video
Updated: Jun 13, 2025
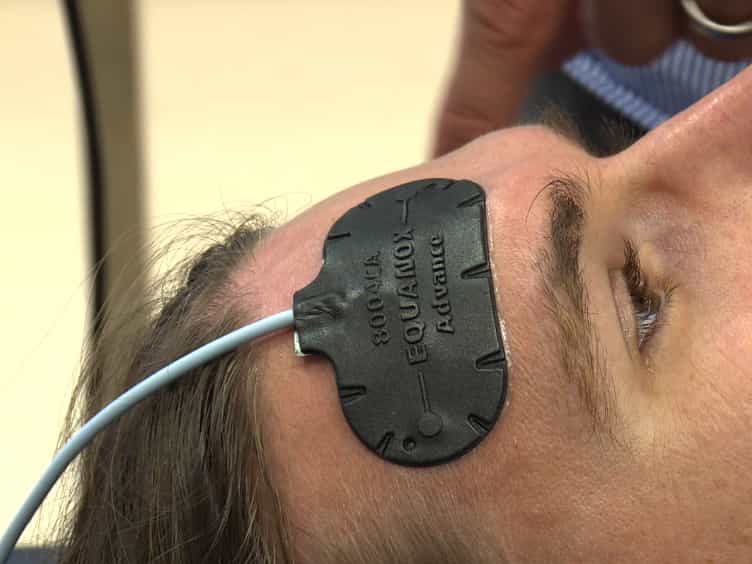

A Model to Simulate Clinically Relevant Hypoxia in Humans
Published on: December 22, 2016
Muscle oxygenation and local blood volume difference between intercostal and deltoid during dry static apnea in
Dario Vrdoljak1, Željko Dujić2, Colin D Hubbard3
1Faculty of Kinesiology, University of Split, Split, Croatia.

Abstract:
During either a static or dynamic apnea, oxygen is delivered to vital organs, i.e., the brain and heart, and there is a compensatory reduction of oxygen consumption in peripheral tissues. Additionally, maximal apnea is characterised by the initial easy-going phase and subsequent struggle phase in which involuntary breathing movements appear. The aim of this study was to compare the oxygenation and local blood volume of one active (external intercostal) and one non-active (deltoid) muscle during maximal dry static apneas in breath-hold divers while supine. Thirteen breath-hold divers performed 3 preparatory apneas followed by 3 maximal apneas with 5 min of supine rest between each apnea. During all apneas (duration, 115-323 s; IBM, 7-35) muscle oxygenation and muscle blood volume change were measured via NIRS. The variables quantified were muscle oxygen saturation (SmO2) and total hemoglobin (tHb). We found that the decline in oxygen saturation was similar in external intercostals and deltoids, even though their physiological role during a breath-hold is different. However, the external intercostals re-saturated at a significantly higher rate following a maximal apnea than the deltoid muscle (p = 0.02). Also, during the apneas, there was a significantly different response between muscles, where external intercostals had an increase and deltoid a decrease in tHb (p = 0.01). These findings indicate that despite respiratory muscle activity resulting from IBMs during breath-holds external intercostal muscle re-oxygenation occurs faster than peripheral muscles which may allow for a faster return to normal breathing.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Related Concept Videos
 01:21
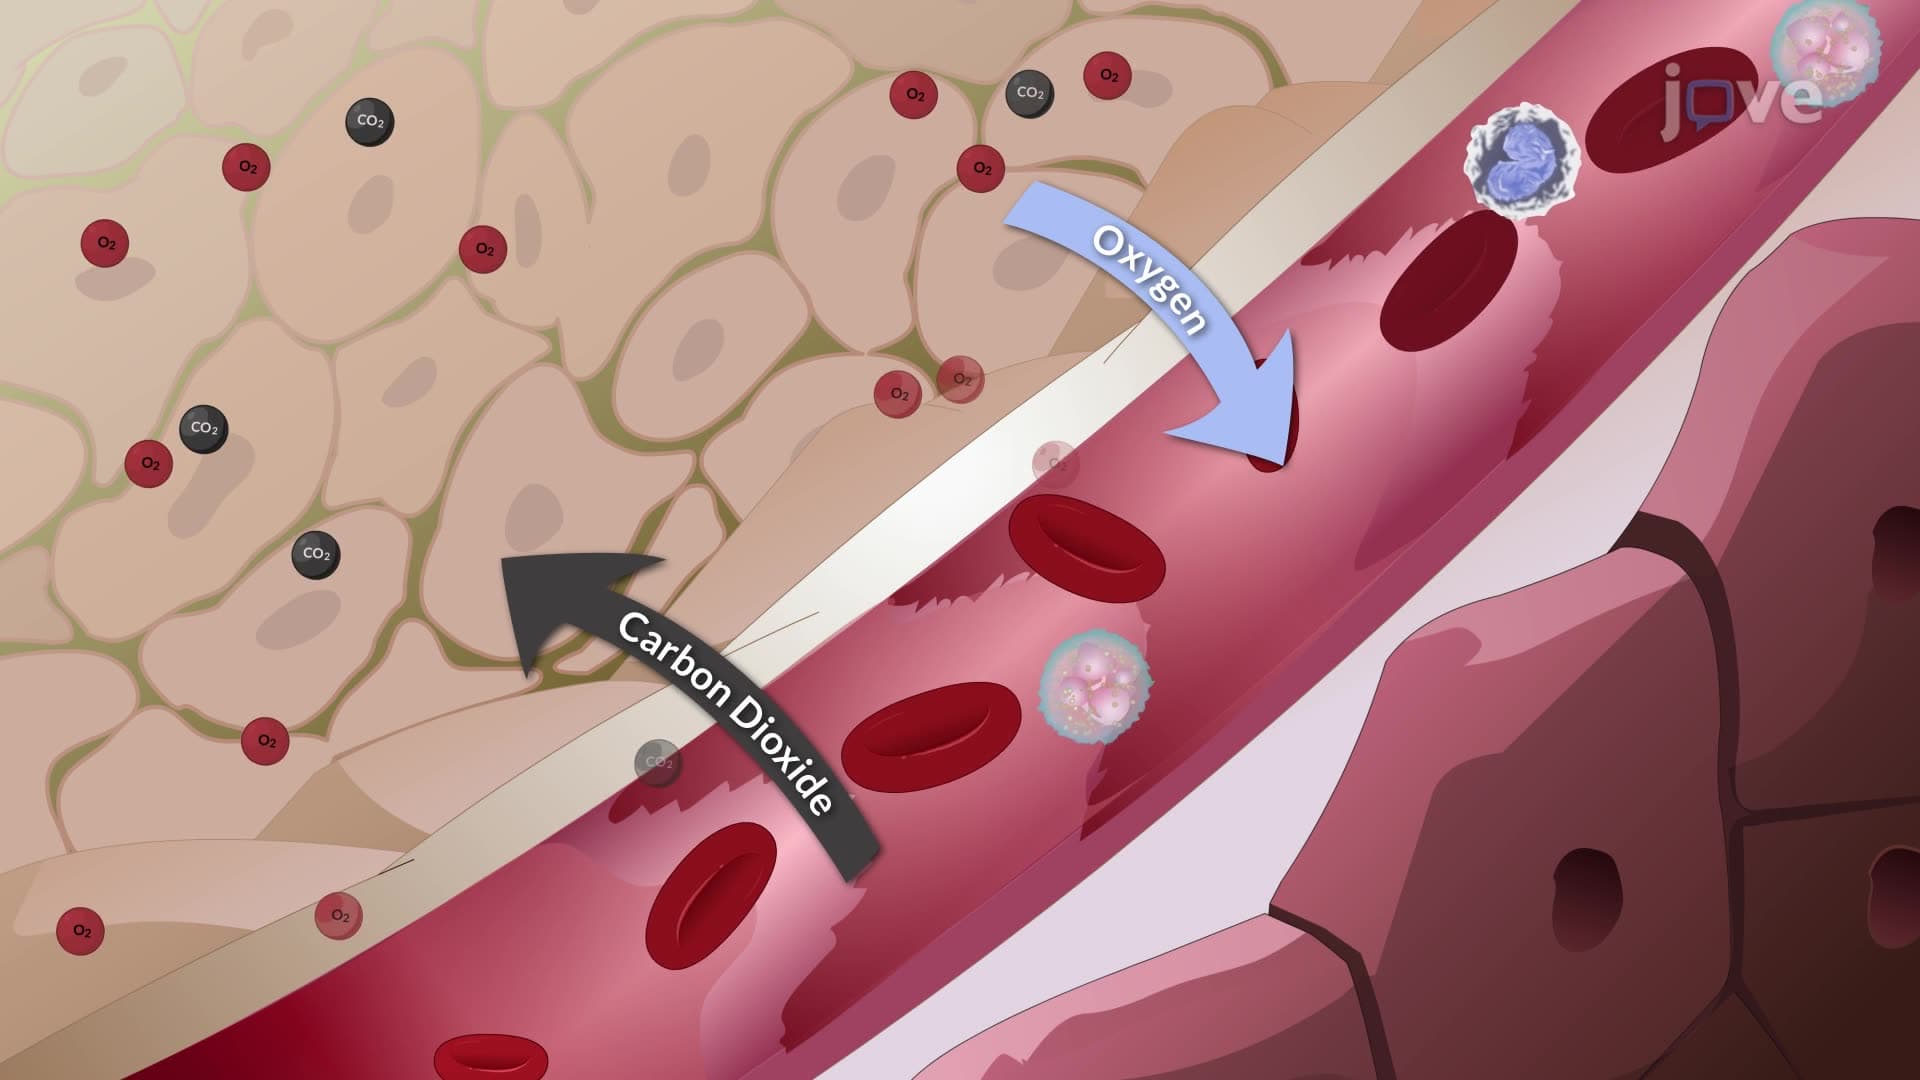
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:24
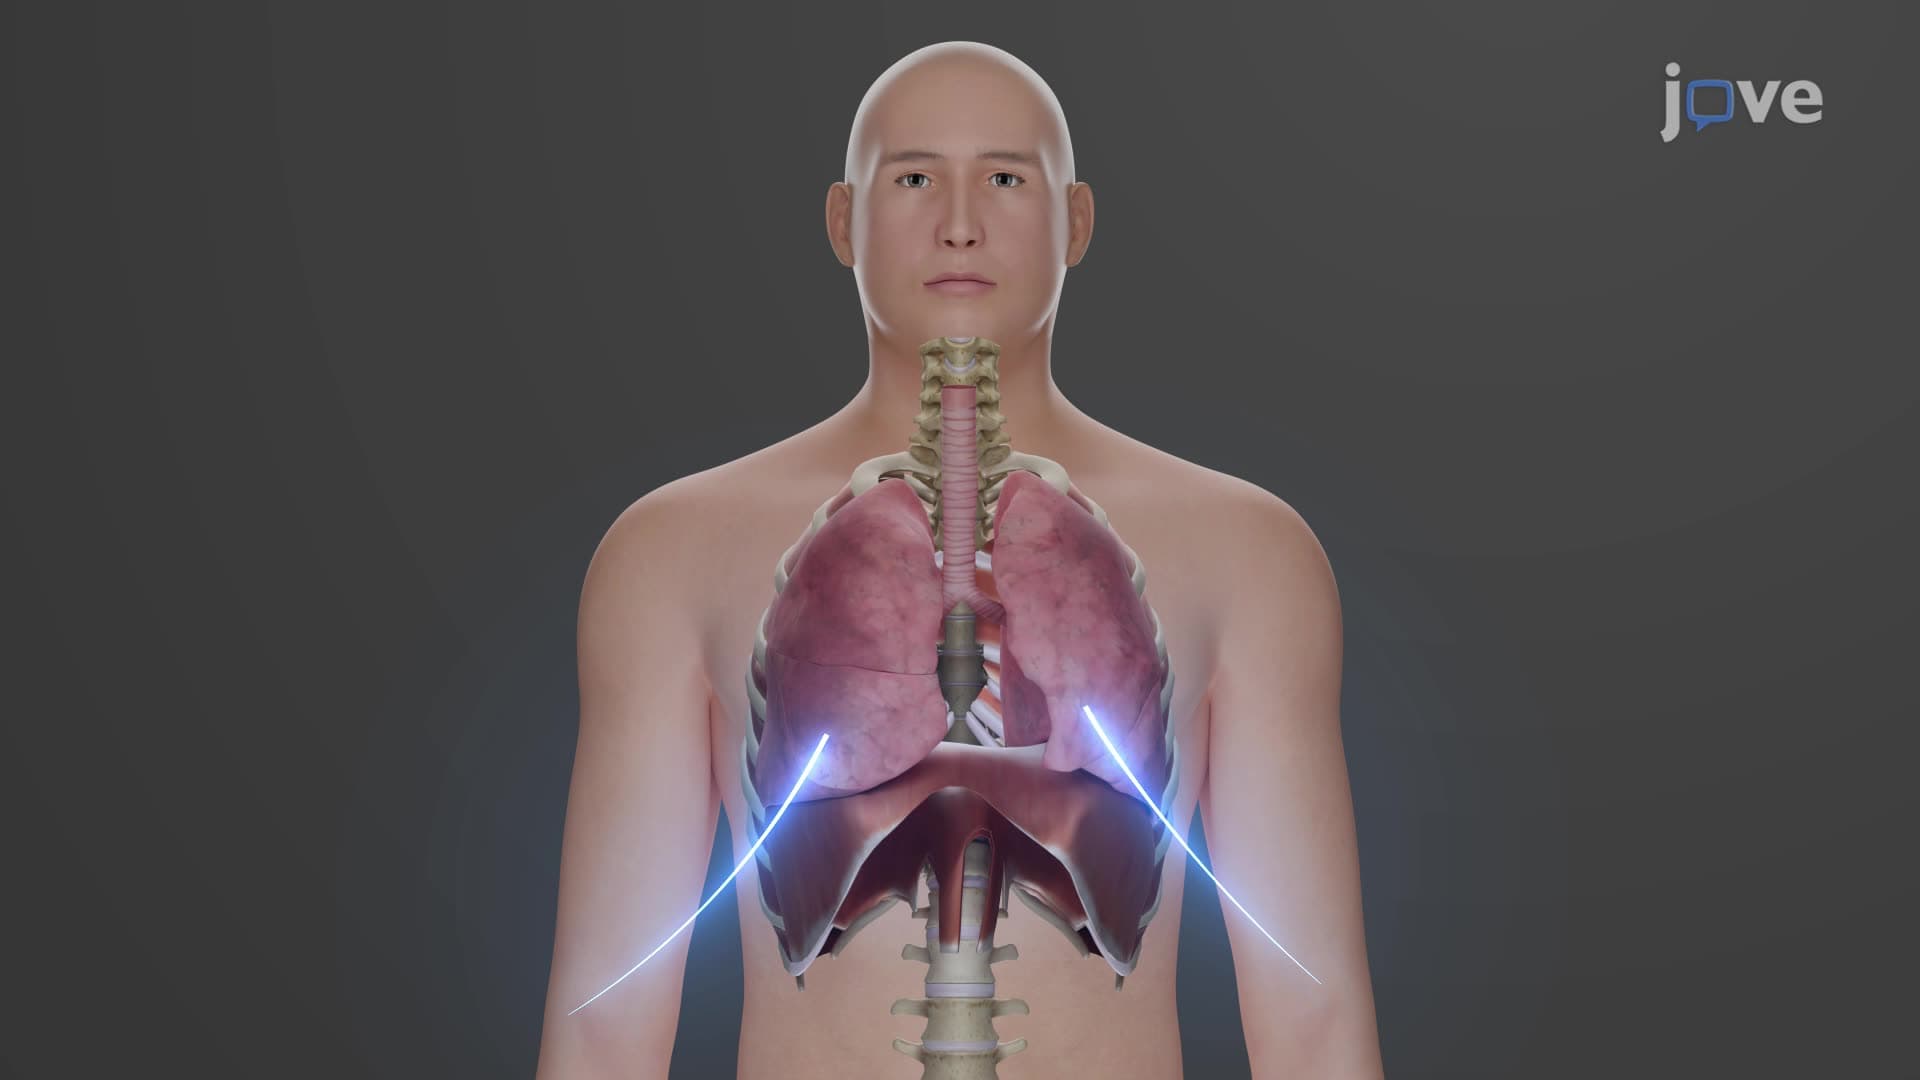
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...