Related Experiment Video
Updated: May 27, 2025


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Validating the Hierarchical Nature of the AO Spine Upper Cervical Spine Injury Classification System
Rajkishen Narayanan1, Jonathan Dalton1, Richard Bransford2
1Department of Orthopaedic Surgery, Rothman Orthopaedic Institute at Thomas Jefferson University Hospital, Philadelphia, PA.

Study Design:
Global cross-sectional survey.
Objective:
To validate the hierarchical nature of the AO Spine Upper Cervical Spine Injury Classification (UCIC) across AO geographical regions/practice experience.
Summary Of Background Data:
To create a universally validated scheme with prognostic value, AO Spine established an upper cervical spine injury classification involving three elements: injury morphology (region: I-occipital condyle and craniocervical junction; II-C1 ring and C1-2 joint; III-C2 and C2-3 joint), and (subtype: A-isolated bony injury; B-bony/ligamentous injury; C-displaced/translational injury), neurological status [N0-intact; N1-transient deficit; N2-radiculopathy; N3-incomplete spinal cord injury (SCI); N4-complete SCI, and NX-unable to examine], and case-specific modifiers (M1-injuries at risk of nonunion; M2-injuries at risk of instability; M3-patient specific factors; M4-vascular injury).
Materials And Methods:
Totally, 151 AO Spine members (orthopaedic and neurosurgery) were surveyed globally regarding the severity (zero-low severity to 100-high severity) of each UCIC variable. Primary outcomes were differences in perceived injury severity score (ISS) over various geographic/practice settings, level of experience, and subspecialty.
Results:
One hundred forty-eight responses were received. There was an increase in median perceived severity as each anatomic region (I-III) progressed from types A to B to C. Neurological status progressed similarly, except N1 and N2 were perceived similarly. Modifier M2 was perceived more severely than M3. There were no differences in ISS among levels of surgeon experience. There were small geographic differences with respondents from North and Central and South America perceiving types IC ( P =0.003), IIB ( P =0.003), and IIIB ( P =0.003) somewhat more severely than other regions. Neurosurgeons perceived types IB ( P =0.002) and IIIB ( P =0.026) as more severe than orthopaedic spine surgeons.
Conclusions:
The AO Spine UCIC has overall excellent hierarchical progression in subtype ISS. These findings are consistent across geographic regions, spine subspecialty training and experience levels.
Related Concept Videos
 01:16
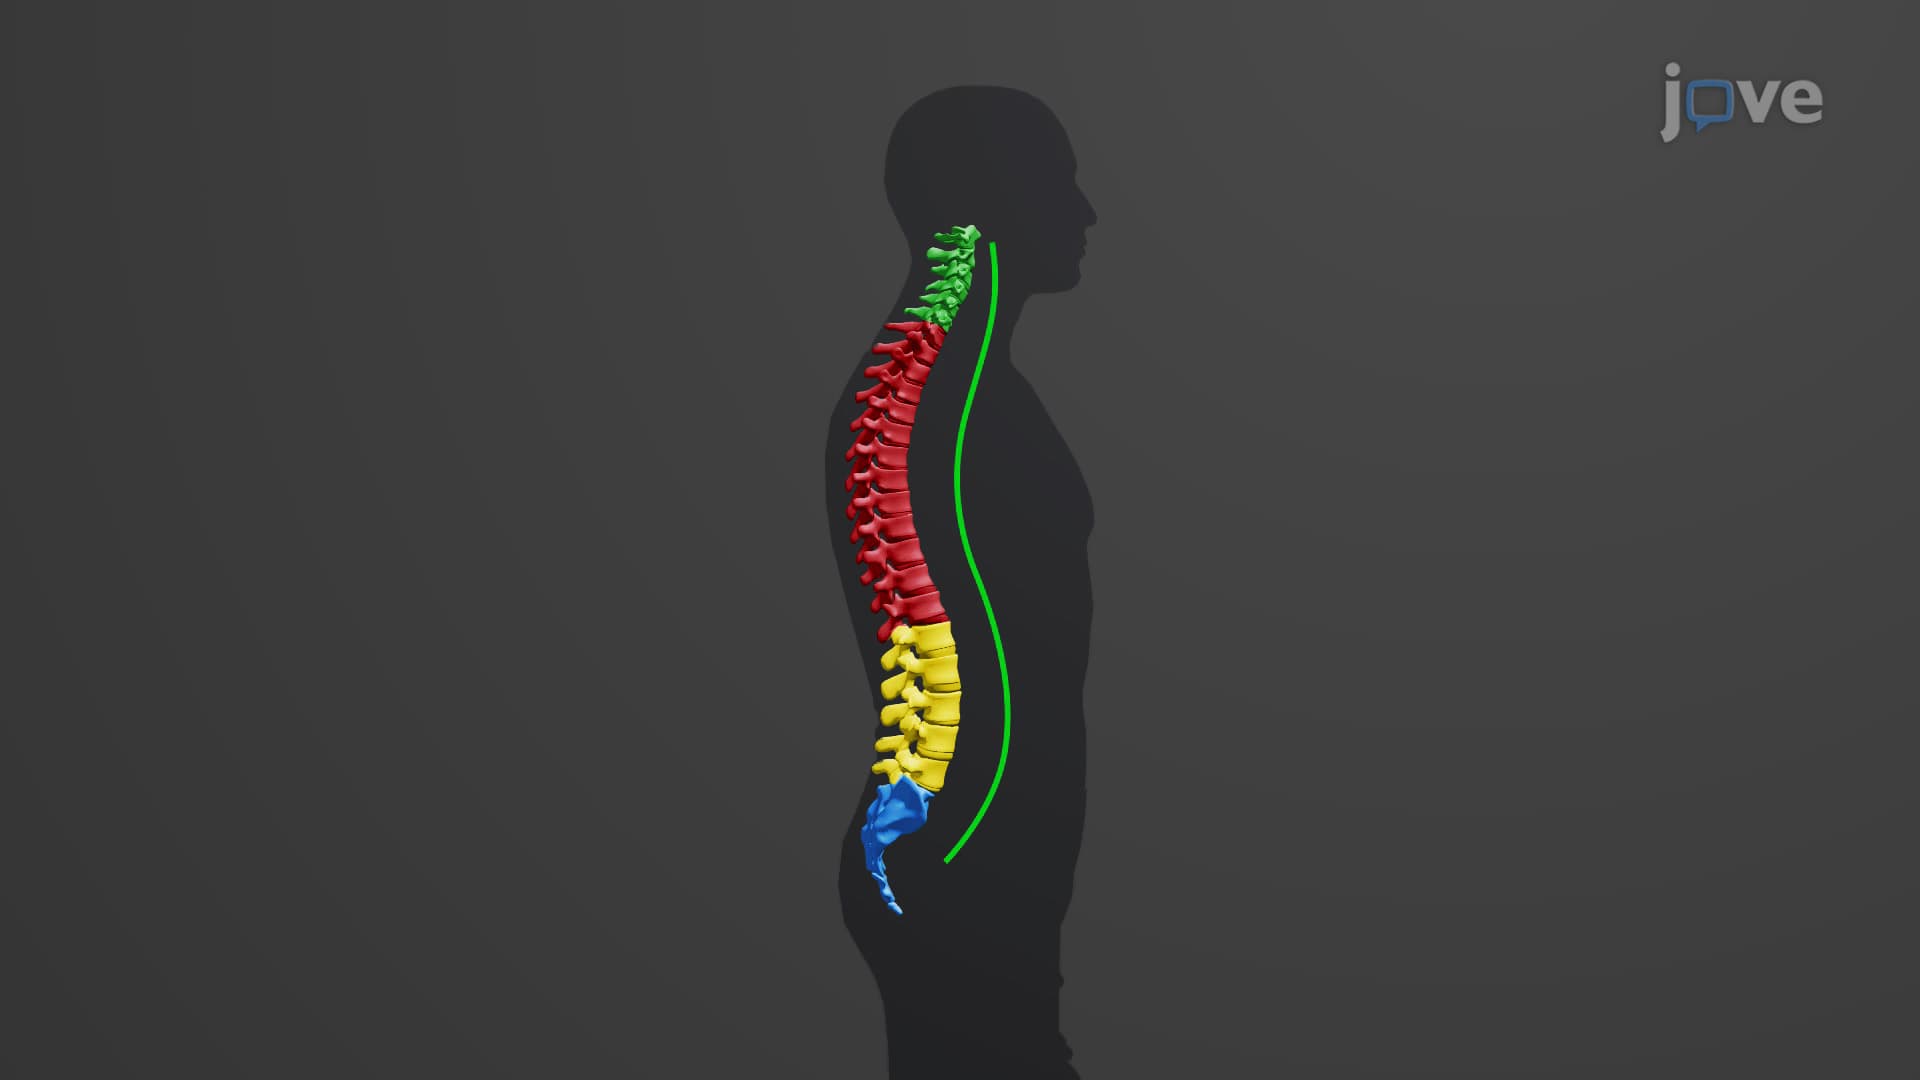
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:30
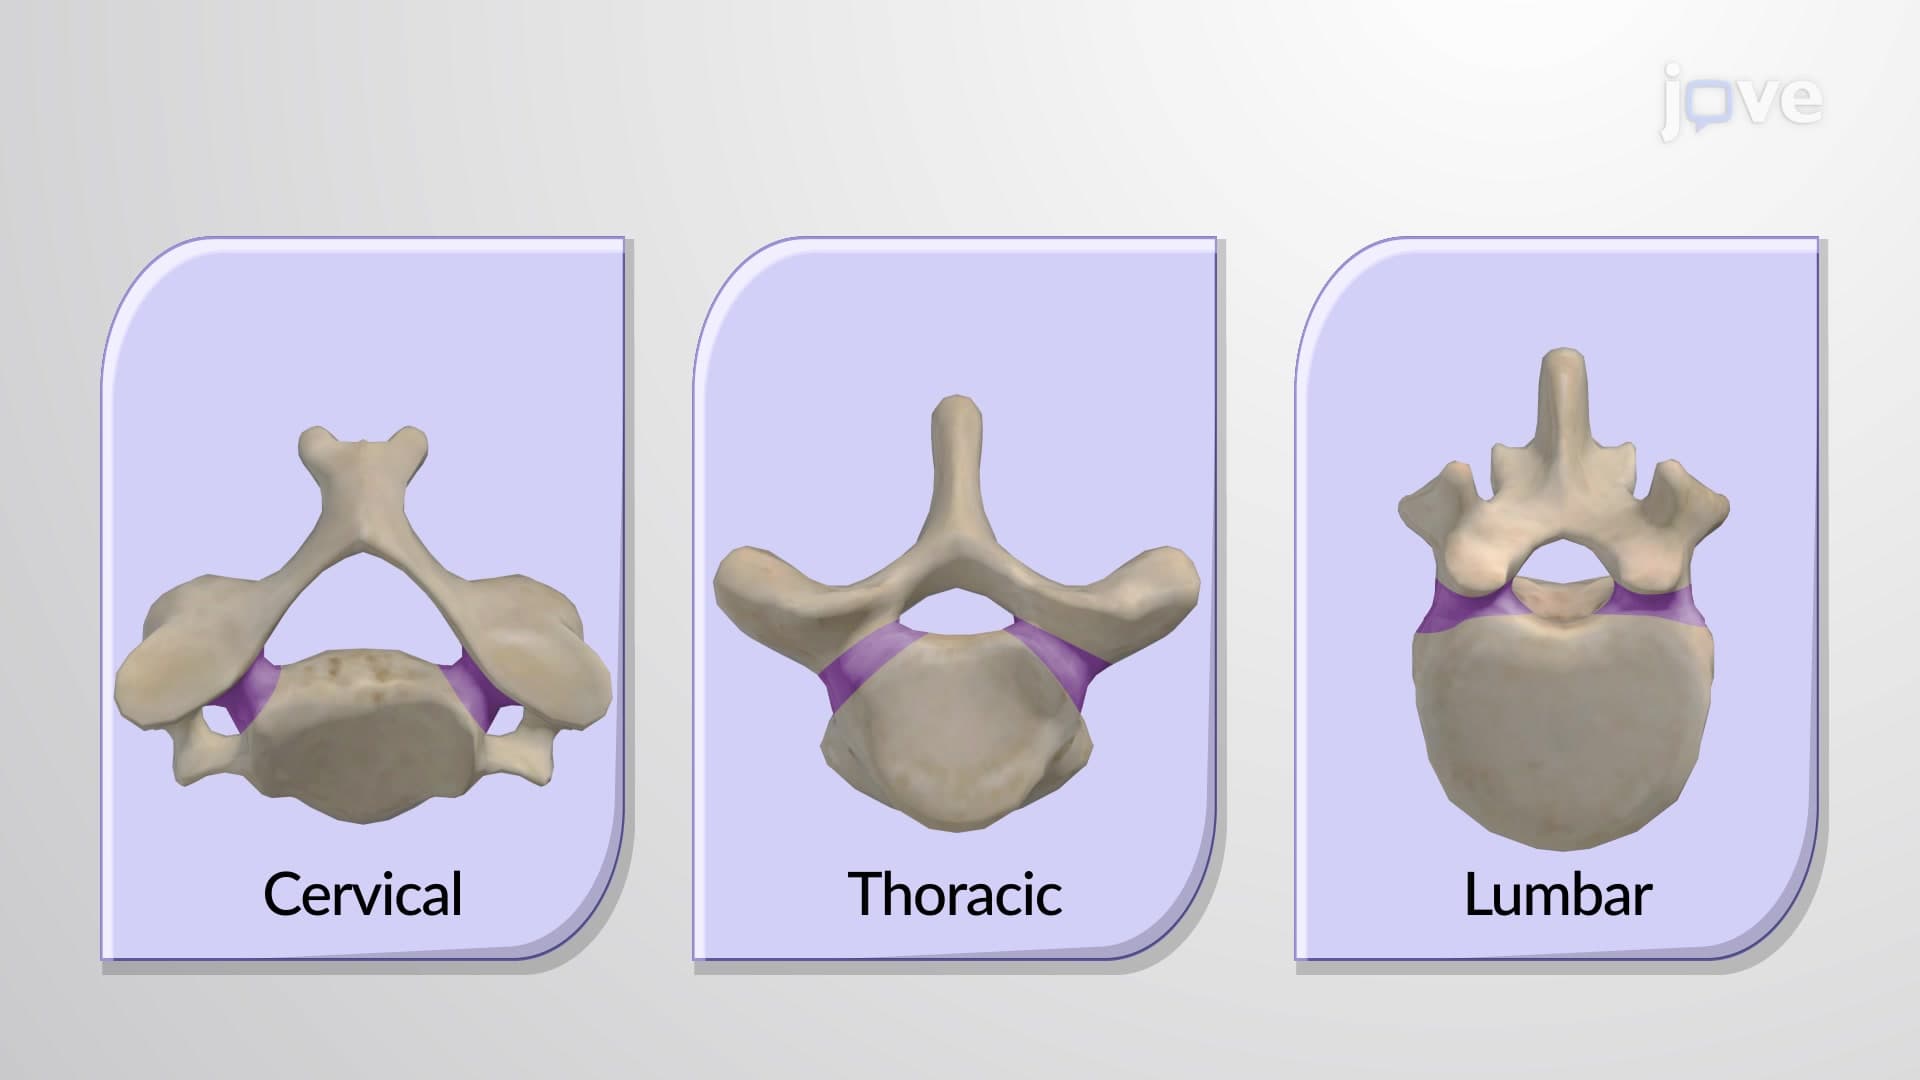
General Structure of a Vertebra
 01:23
Spinal Nerves: Anatomy
There are 31 bilateral pairs of spinal nerves, each emerging from the spinal cord through the intervertebral foramina—openings between adjacent vertebrae. These nerves are...
 01:54
The Spinal Cord
 01:18
Classification of Bones
Long and Short Bones
The appendicular skeleton, particularly the upper and lower limbs, is primarily made of long and short bones. The...
 01:09
Overview of the Axial Skeleton
The axial skeleton of the...