Related Experiment Video
Updated: May 23, 2025
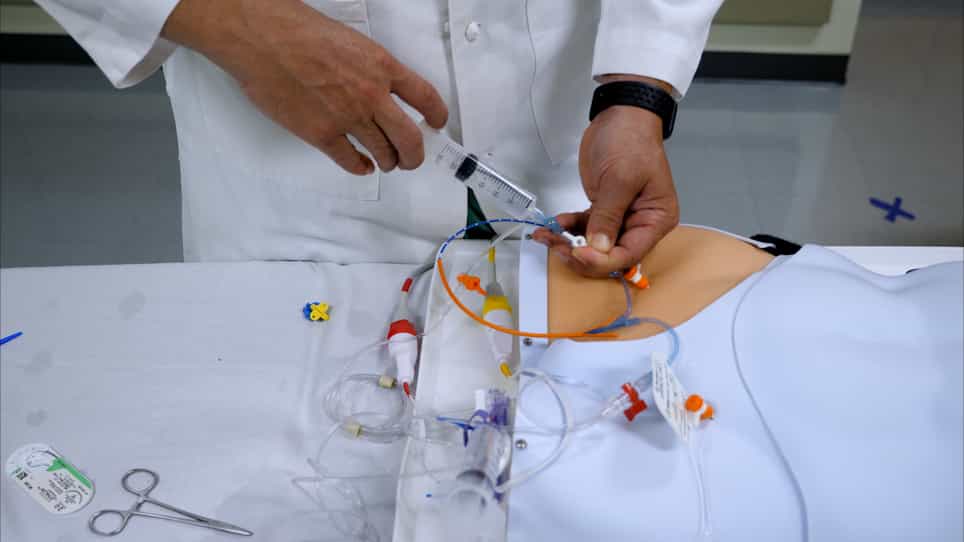

Complete and Partial Resuscitative Endovascular Balloon Occlusion of the Aorta for Hemorrhagic Shock
Published on: May 19, 2022
Partial REBOA Zone 1 is associated with lower mortality compared to complete REBOA Zone 1 and emergency department
Morgan G Dewey1, Ernest E Moore1,2, Lee Anne Ammons2
1School of Medicine, University of Colorado, Aurora, Colorado, USA.

Background:
Resuscitative endovascular balloon occlusion of the aorta (REBOA) and emergency department thoracotomy (EDT) are effective methods of aortic occlusion (AO) for life-threatening bleeding; however, complete AO can lead to visceral ischemia. Partial REBOA (P-REBOA) has been proposed as an alternative to the completely occlusive REBOA (C-REBOA) to balance hemorrhage control and perfusion. Using the Aortic Occlusion for Resuscitation in Trauma (AORTA) multicenter, observational registry, we tested the hypothesis that P-REBOA resulted in better outcomes compared to EDT and C-REBOA.
Study Design And Methods:
We queried the 2017-2023 AORTA registry for adults who underwent EDT, C-REBOA, or P-REBOA in the emergency department (ED). Patients with chest penetrating injuries were excluded. We compared mortality, ventilator-free-days (VFD), and ICU-free-days (ICUFD) using survival analysis or generalized linear models to adjust for confounders.
Results:
Overall, 921 patients underwent EDT (n = 613, 66.6%), C-REBOA (n = 224, 24.3%), or P-REBOA (n = 84, 9.1%); 83.1% died. After confounder adjustment, compared to P-REBOA, both C-REBOA and EDT were associated with a lower likelihood of attaining hemodynamic improvement and stability as well as with higher mortality (adjusted hazard ratio, aHR = 1.84; 95% CI: 1.01-1.60 and aHR = 3.32; 95% CI: 1.96-2.78, respectively). EDT patients had less VFD and ICUFD than those undergoing C-REBOA and P-REBOA, but there were no differences between the two endovascular procedures. Among patients who survived >48 h, EDT was more likely to be associated with complications compared to the other two procedures.
Discussion:
P-REBOA was more likely to be associated with improved hemodynamic stability and reduced mortality compared to C-REBOA and EDT, suggesting this modality may be a better AO procedure for patients with no penetrating thoracic injuries.
More Related Videos
 08:50
Technique and Patient Selection Criteria of Right Anterior Mini-Thoracotomy for Minimal Access Aortic Valve Replacement
Published on: March 26, 2018
 05:39
Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:30
Acute Respiratory Failure-III