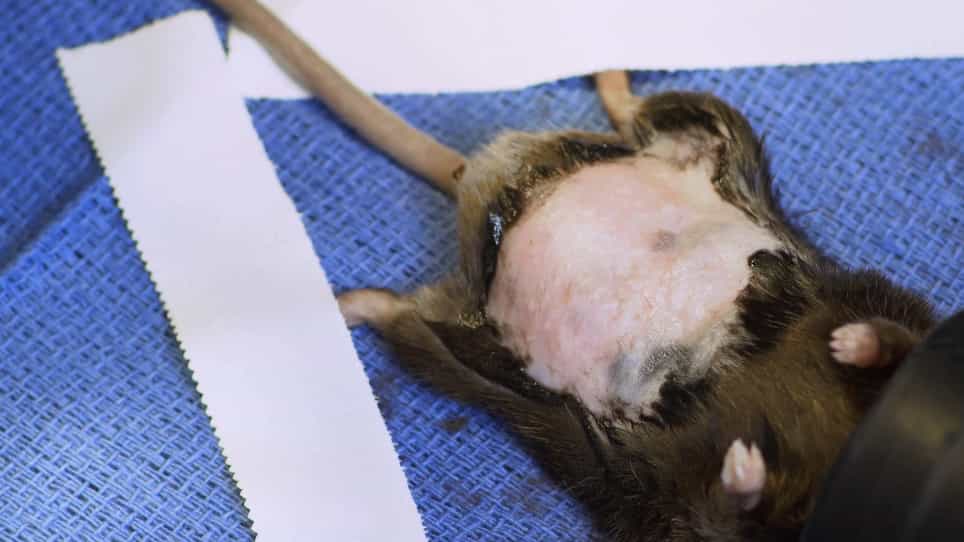
Related Experiment Video
Updated: May 23, 2025


The C-seal: A Biofragmentable Drain Protecting the Stapled Colorectal Anastomosis from Leakage
Published on: November 4, 2010
Anastomotic leakage in colorectal and ovarian cancer resections: A comparative cohort study
Radwa Hablase1, Jacqueline Steinke2, Aqsa Aslam3
1Academic Department of Gynaecological Oncology, Royal Surrey NHS Foundation Trust, Guildford GU2 7XX, UK; College of Health, Medicine and Life Sciences, Brunel University London, Uxbridge UB83PH, UK.

Objective:
To compare anastomotic leak (AL) rates after colorectal resections performed by colorectal surgeons in ovarian and colorectal cancer surgeries, examining predictive risk factors, short-term and survival outcomes, and early AL markers in ovarian cancer patients.
Methods:
Single-centre retrospective study comparing AL rates between 233 ovarian debulking surgeries from January 1, 2010, to December 31, 2022, and 408 gender-matched colorectal cancer patients from January 2014 to December 2022 at the Royal Surrey NHS Foundation Trust, UK. Predictive risk factors were assessed using logistic regression and the overall survival using log-rank tests and Cox proportional hazards model. Receiver operating characteristic (ROC) curves were plotted for C-reactive protein (CRP) values from postoperative days one to five.
Results:
19 % of ovarian cancer patients underwent colorectal resection, of which 90 % had primary anastomosis. AL rates were 4.7 % and 1.9 % (p = 0.08) for the ovarian and colorectal groups respectively. Covering stoma rates were 11.6 % in the ovarian and 15 % in the colorectal group. 80 % in the ovarian group had rectosigmoid resections. Delays in chemotherapy and residual disease were independent risk factors for increased risk of death in ovarian interval debulking surgery. HR 1.03 (95 % CI: 1.01-1.05, p = 0.008) and HR 2.02 (95 % CI: 1.11-3.68, p = 0.021). CRP on days three and four had a 98 % negative predictive value at a cut-off of 286 mg/L and 232 mg/L, respectively.
Conclusion:
Ovarian cancer patients are at high risk of AL. Preventative measures should be considered. Low CRP on post-operative days three and four may be used exclude AL.