Related Experiment Video
Updated: May 10, 2025
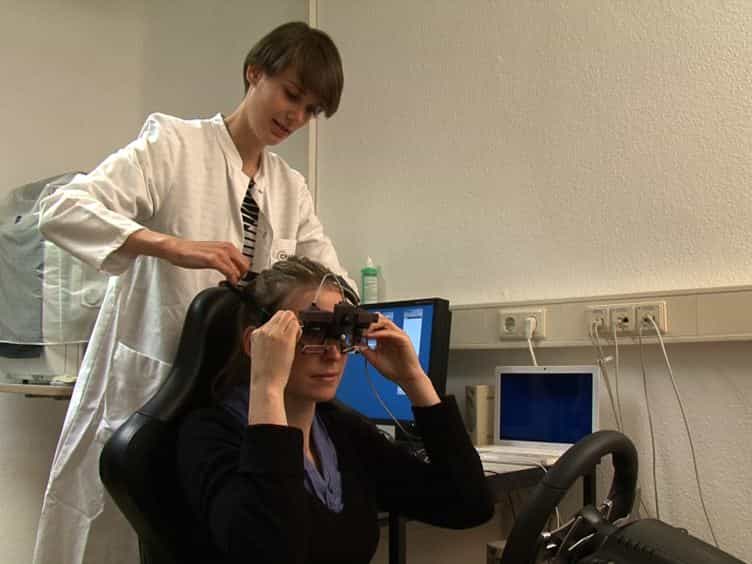

Driving Simulation in the Clinic: Testing Visual Exploratory Behavior in Daily Life Activities in Patients with Visual Field Defects
Published on: September 18, 2012
Exploring Factors Influencing Driving Simulator Performance in Patients With Acquired Brain Injury Using Hierarchical
Shuto Takehara1,2, Tasuku Sotokawa2,3, Yuta Tauchi1
1Department of Rehabilitation Medicine, Hyogo Medical University Sasayama Medical Center, Hyogo, JPN.

Abstract:
Background Driving simulator training is widely recognized as an effective tool for driving rehabilitation. However, the key factors influencing simulator performance and the extent of training-related improvements remain insufficiently explored. This study aimed to identify the demographic, motor, and cognitive factors associated with driving simulator performance and post-training improvements in patients with acquired brain injury (ABI) using clustering analysis. Methods A total of 64 patients with ABI (59% cerebral hemorrhage, 34% cerebral infarction, 7% traumatic brain injury; mean age 64±13 years; 81% male) underwent comprehensive neuropsychological assessments and driving simulator evaluations before and after training. Multiple factor analysis was applied to integrate pre- and post-training variables and reduce dimensionality. Hierarchical Clustering on Principal Components was then performed to classify patients based on training effect patterns. The Kruskal-Wallis test and post hoc multiple comparisons were used to assess differences in background factors among the clusters. Results Three distinct clusters were identified: Cluster 1 (n=32) exhibited consistently high performance in reaction and city-driving tasks, Cluster 2 (n=19) demonstrated prolonged reaction times but showed significant improvements in city-driving tasks after training, and Cluster 3 (n=13) demonstrated severe city-driving errors and limited post-training improvement. Neuropsychological assessments revealed significant differences among the clusters (p < 0.05), with Cluster 1 consistently outperforming Clusters 2 and 3 across multiple cognitive domains, including attention, cognitive flexibility, visuospatial abilities, memory, and executive function. Conclusion Neuropsychological assessments may serve as predictors of both baseline driving performance and post-training improvements. Tailoring interventions to individual cognitive profiles, particularly focusing on attention, visuospatial abilities, and executive function, may enhance the efficacy of simulator-based rehabilitation and support the safe resumption of driving. Future longitudinal studies should examine how targeted cognitive training might improve driving performance in patients with different cognitive profiles.

