Related Experiment Video
Updated: Apr 11, 2026
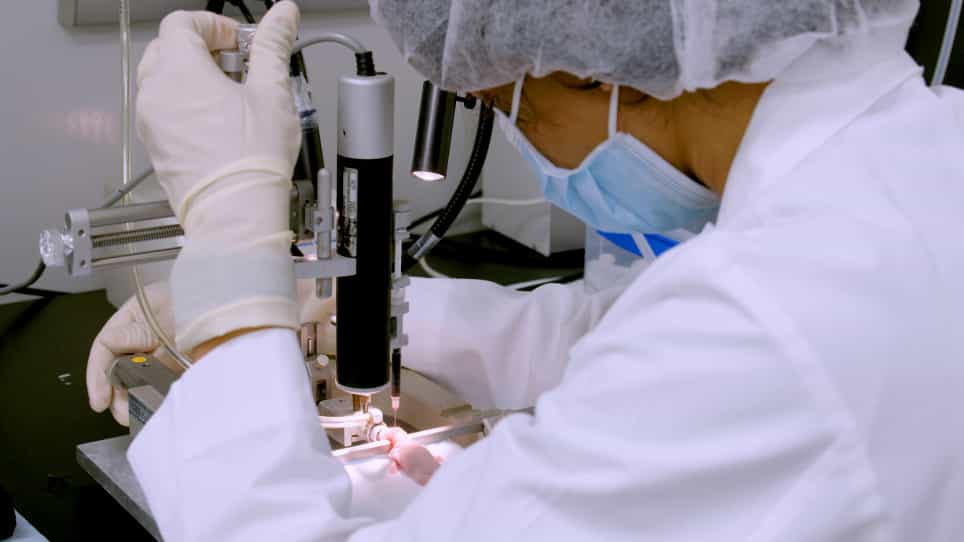
Modeling Neonatal Intraventricular Hemorrhage Through Intraventricular Injection of Hemoglobin
Published on: August 25, 2022
Secondary Postpregnancy Hemorrhage: Guide for Diagnosis and Management
Alyssa Kirsch1, Lori Strachowski1, Liina Poder1
1From the Departments of Radiology and Biomedical Imaging (A.K., L.S., L.P., S.B., V.F., J.H., E.L., D.S., H.C.), Pathology and Laboratory Medicine (J.R.), and Obstetrics, Gynecology, and Reproductive Sciences (S.W.), University of California San Francisco, 505 Parnassus Ave, San Francisco, CA 94143.

Secondary postpregnancy hemorrhage (PPH) is increasing in incidence, especially in developed countries such as the United States. PPH occurs after 24 hours and up to 12 weeks in the postpregnancy period and may be associated with significant maternal morbidity. Common causes of secondary PPH are subinvolution of the placental site (SIPS) and retained or residual products of conception (RPOC). Other less common and rare causes include bleeding diathesis, endo(myo)metritis, gestational trophoblastic disease, and vascular anomalies such as congenital arteriovenous malformation (AVM), iatrogenic arteriovenous fistula, or pseudoaneurysm. A common finding encountered during imaging evaluation of secondary PPH is increased vascularity in the myometrium deep to an implantation site, termed enhanced myometrial vascularity (EMV). EMV typically represents the physiologic reversion of the uterus back to its prepregnancy state. The appearance of EMV varies from mild to marked and is also associated with SIPS and RPOC. Interpretation or reporting of EMV as an AVM or other rare uterine vascular anomaly may lead to unnecessary testing and overtreatment. The authors review placental physiology, describe the causes of secondary PPH and their imaging appearances, and present an algorithm to assist the radiologist in diagnosis of this important condition and management options. ©RSNA, 2025 Supplemental material is available for this article. See the invited commentary by Gomez in this issue.
Secondary postpregnancy hemorrhage (PPH) is increasing in incidence, especially in developed countries such as the United States. PPH occurs after 24 hours and up to 12 weeks in the postpregnancy period and may be associated with significant maternal morbidity. Common causes of secondary PPH are subinvolution of the placental site (SIPS) and retained or residual products of conception (RPOC). Other less common and rare causes include bleeding diathesis, endo(myo)metritis, gestational trophoblastic disease, and vascular anomalies such as congenital arteriovenous malformation (AVM), iatrogenic arteriovenous fistula, or pseudoaneurysm. A common finding encountered during imaging evaluation of secondary PPH is increased vascularity in the myometrium deep to an implantation site, termed enhanced myometrial vascularity (EMV). EMV typically represents the physiologic reversion of the uterus back to its prepregnancy state. The appearance of EMV varies from mild to marked and is also associated with SIPS and RPOC. Interpretation or reporting of EMV as an AVM or other rare uterine vascular anomaly may lead to unnecessary testing and overtreatment. The authors review placental physiology, describe the causes of secondary PPH and their imaging appearances, and present an algorithm to assist the radiologist in diagnosis of this important condition and management options. ©RSNA, 2025 Supplemental material is available for this article. See the invited commentary by Gomez in this issue.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:22
Aneurysm IV: Nursing Management
 01:30
Venous Thrombosis IV: Nursing Management
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management