Related Experiment Video
Updated: Jun 20, 2026
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Ossification of Posterior Longitudinal Ligament Growth in the C1/2 Segment and its Clinical Significance: Is C2 Total
Dongkyu Kim1, Hyun Jun Jang, Bong Ju Moon
1Department of Neurosurgery, The Spine and Spinal Cord Institute, Gangnam Severance Hospital, Yonsei University College of Medicine, Seoul, Korea.

Study Design:
A retrospective analysis at a single institution.
Objective:
This study aimed to determine whether ossification of posterior longitudinal ligament (OPLL) growth in the C1/2 area remains clinically uneventful despite visible radiologic enlargement.
Background:
In cervical decompressive surgery for OPLL, preserving the C2 lamina is preferred for stability, and the larger spinal canal space above C2 tends to mitigate clinical issues caused by OPLL growth. However, the effects of OPLL progression in the C1/2 segment, which often remains untreated, on patients' clinical outcomes are unclear.
Patients And Methods:
We enrolled 144 patients with cervical OPLL who underwent decompression surgery between January 2011 and December 2018. The patients were categorized based on whether they underwent a C2 sparing procedure or C2 laminectomy. The primary outcome was radiologic progression of OPLL, defined as a 2 mm increase in sagittal thickness or longitudinal elongation, and its correlation with clinical symptoms.
Results:
Of the 144 patients, 35 were in the C2 sparing group, and 109 were in the C2 laminectomy group, with an average follow-up period of 5.2 to 5.6 years. The rate of radiologic progression of OPLL in the C1/2 segment was comparable between the two groups (54.3% vs. 51.4%, P = 0.916). However, diagnosis of C1/2 stenosis at the final follow-up was still lower in the C2 sparing group than in the C2 laminectomy group (2.9% vs. 10.1%, P = 0.294), and there were no new cases of symptoms caused by cord compression in the C1/2 segment in either group.
Conclusion:
OPLL in the C1/2 segment was clinically silent despite radiologic growth. For patients who do not present with significant canal stenosis or cord compression due to OPLL above the C2 upper lamina, C2 lamina-sparing decompressive surgery is preferred.
Level Of Evidence:
Level III.
Related Concept Videos
 01:40
Bone Remodeling
 01:27
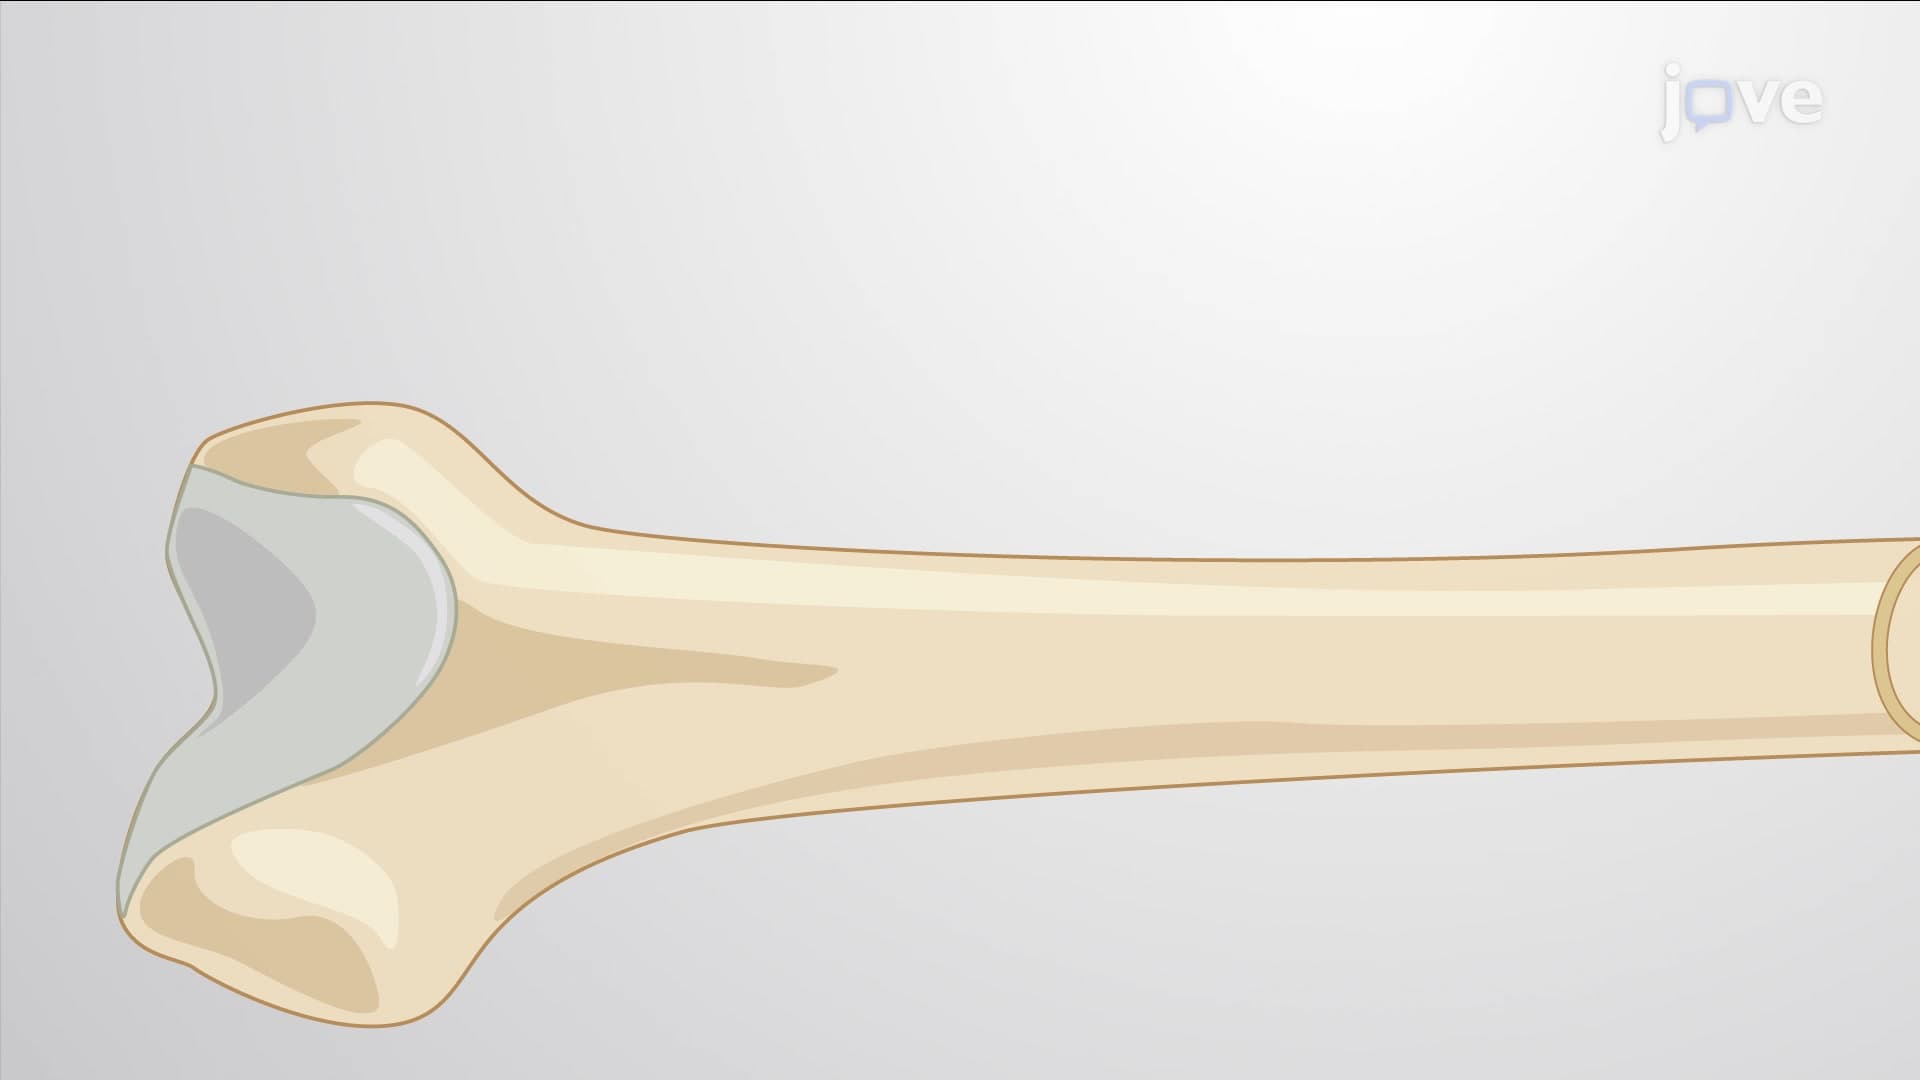
Growth of Cartilage and Bone Tissue
 01:27
Compact Bone
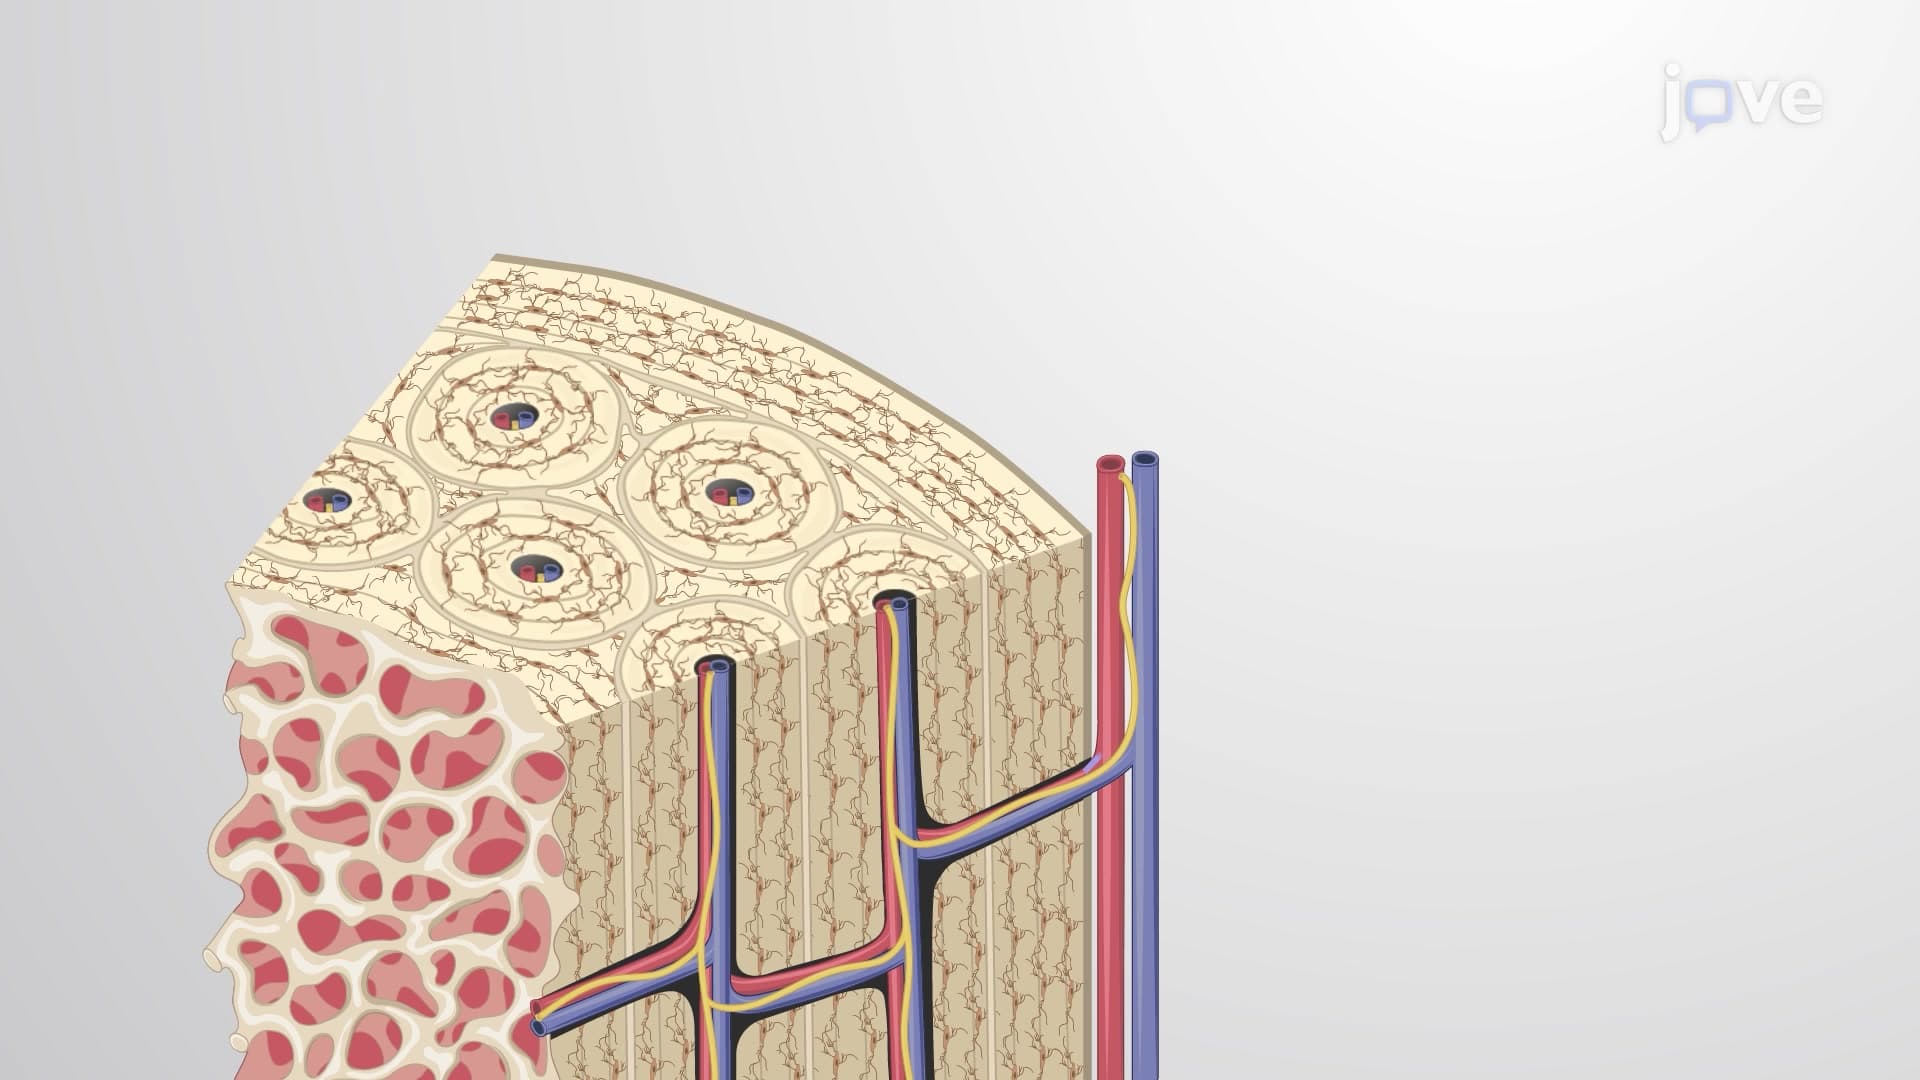
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:24
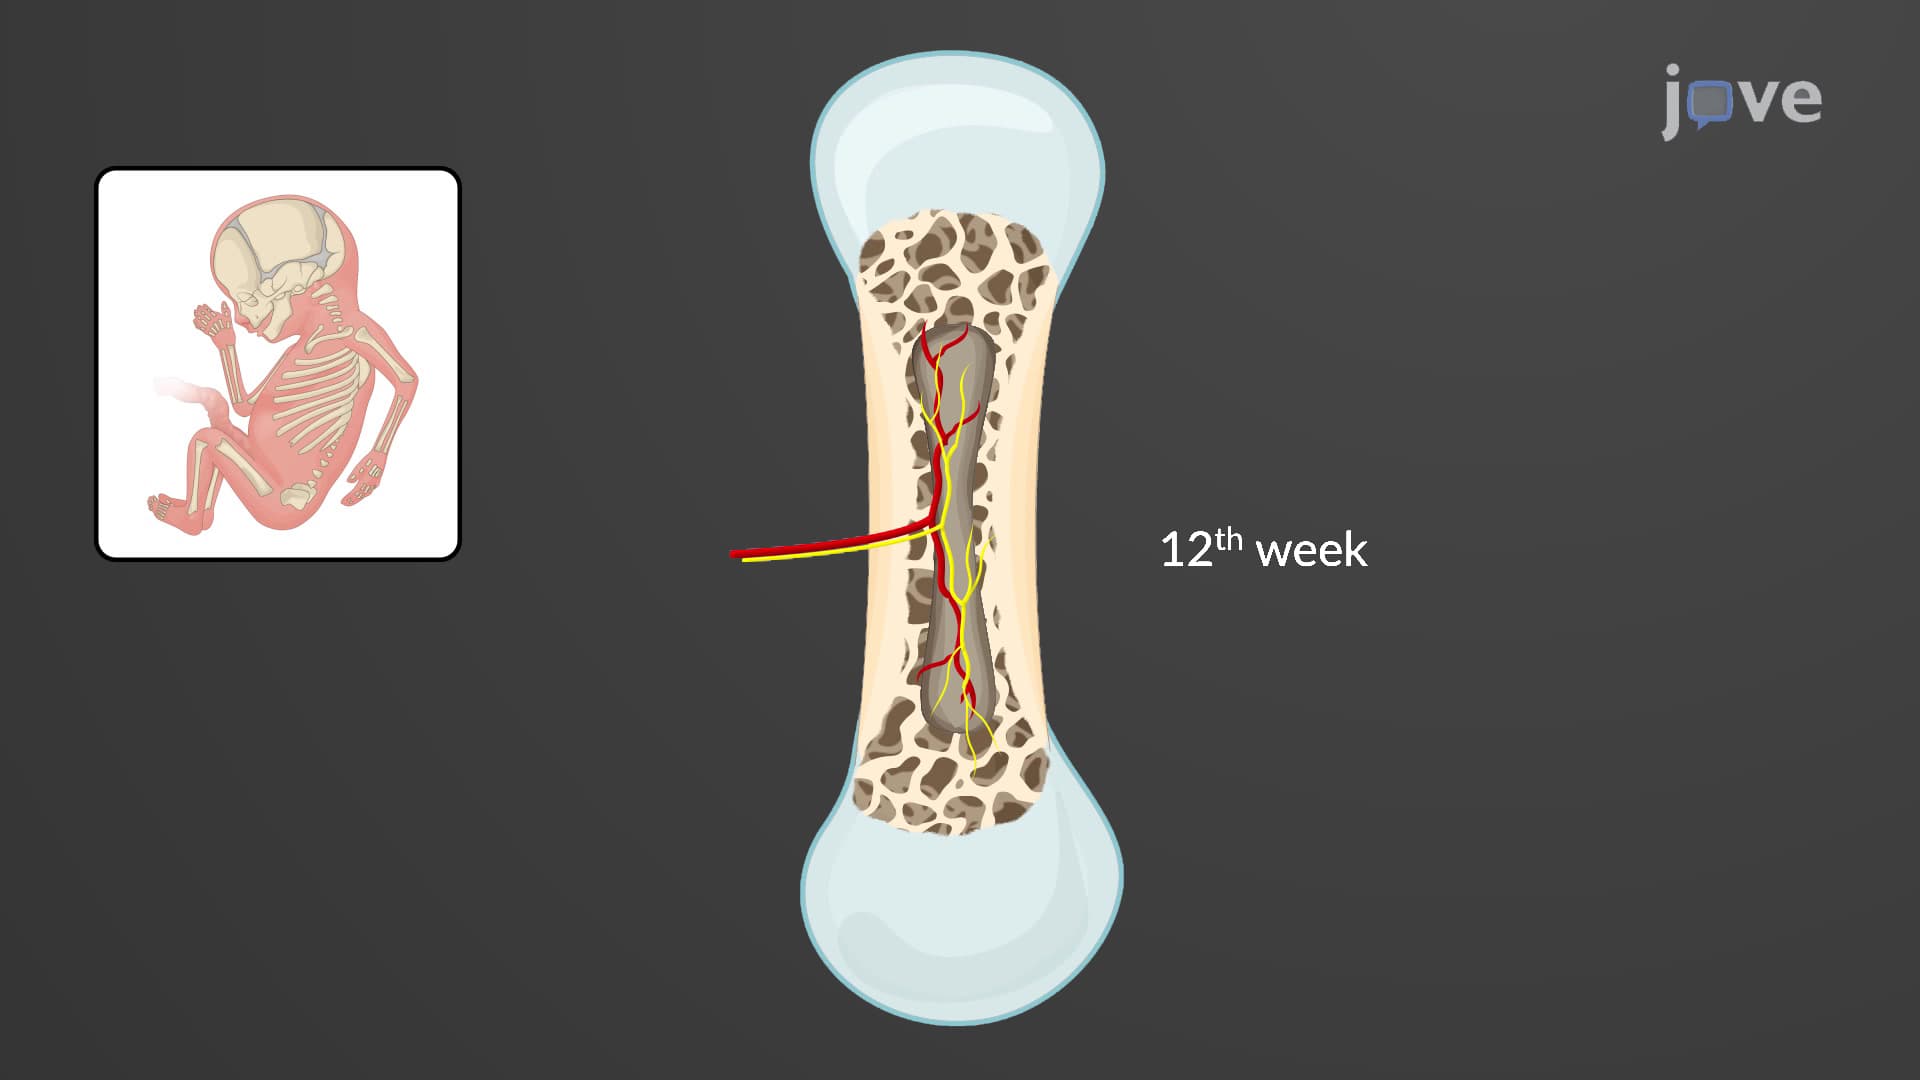
Bone Formation by Endochondral Ossification