Related Experiment Video
Updated: Jul 9, 2026
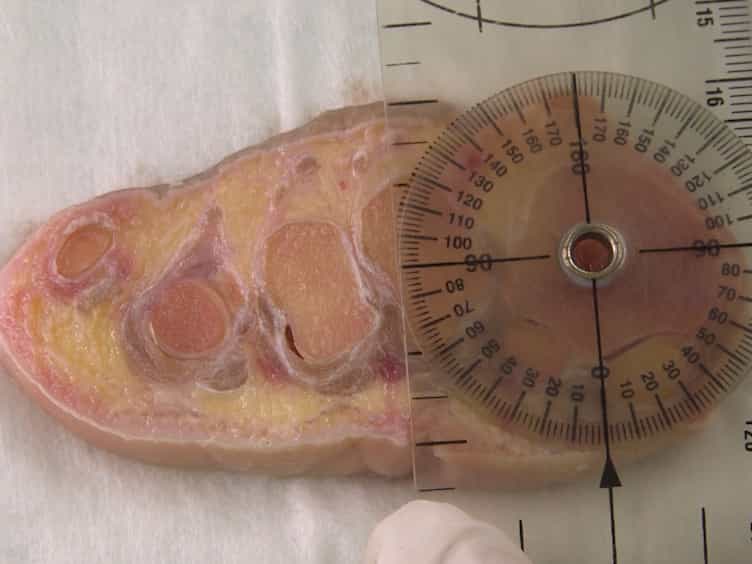

An Anatomical Study of Nerves at Risk During Minimally Invasive Hallux Valgus Surgery
Published on: February 17, 2018
Risk of anterior interosseous nerve injury during forearm surgery: a cadaveric study
Arnaud Walch1, Hugo Despert2, Clément Jubelin2
1Hopital Edouard Herriot, Lyon, France. arnaud.walch@chu-lyon.fr.

Purpose:
The anterior interosseous nerve (AIN) is susceptible to injury during forearm surgery, particularly open reduction and internal fixation (ORIF) of radius fractures. This study aimed to analyze the anatomical relationships between the AIN and the radius to identify regions most vulnerable to iatrogenic injury.
Methods:
A cadaveric study was conducted on ten fresh, non-embalmed forearms. Standardized dissections were performed to assess the course of the AIN, its motor branches, and their proximity to bony landmarks. Measurements were taken using a graduated ruler, with reference to the radius, the bi-epicondylar and bi-styloid lines.
Results:
The AIN originated, on average, 13 mm from the radius, initially separated from the bone by the flexor digitorum profundus and flexor pollicis longus. The first branch to the flexor pollicis longus emerged at an average of 8 mm from the radius, marking the start of the nerve's close contact with the bone. The highest risk zone for AIN injury was identified at the junction of the proximal and middle thirds of the forearm.
Conclusion:
The AIN and its motor branches exhibit significant anatomical variability but consistently demonstrate proximity to the radius at the proximal-middle third junction. To minimize iatrogenic injury, care should be taken when exposing the anterior radius, particularly by avoiding excessive traction or deep retractor placement in this region.