Related Experiment Video
Updated: May 17, 2025

Use of a Hanging-weight System for Isolated Renal Artery Occlusion
Published on: July 19, 2011
Manual Dilution of Continuous Renal Replacement Therapy Fluids in Anuric Patients with Severe Hyponatremia: A Case
Mark V Koning1, Lassima Reijnen1, Femy Kemperman1
1Department of Anesthesiology and Intensive Care, Rijnstate Hospital, Arnhem, The Netherlands.

Introduction:
When a patient with severe hyponatremia requires renal replacement therapy, a too rapid correction of sodium levels may occur. Manual dilution of the fluids during continuous renal replacement therapy (CRRT) is a method that can lead to a controlled correction of sodium. We present a case and add a systematic review to determine the feasibility of this method.
Case Presentation:
A female was admitted to the intensive care unit with acute kidney failure due to anti-glomerular basement membrane antibody glomerulonephritis, anuria, and an initial sodium level of 100 mmol/L. She received CRRT with manually diluted fluids for 6 days, in which sodium levels increased from 108 mmol/L to 130 mmol/L. A search in Medline, Web of Science, and Google Scholar was added for the systematic review. The search yielded 49 cases, including the current report, of which 47 were anuric or oliguric, in which the fluids were diluted to a median of 8 mmol/L (interquartile range 5-11) (range 0-17) above the serum sodium, the median CRRT dose was 27 mL/kg/h (22-30) (13-77.5). This led to an increase in serum sodium of 0.2 mmol/L/h (0.1-0.3) (0-0.7).
Conclusion:
CRRT with manually diluted fluids in patients with severe hyponatremia and anuria can lead to a controlled increase serum sodium, while allowing sufficient RRT dose and fluid removal. Still, errors in dilution may occur and we recommend 4 hourly monitoring of serum sodium levels to timely detect an inadvertent increase in sodium.
More Related Videos
 06:59
A Novel Approach for the Administration of Medications and Fluids in Emergency Scenarios and Settings
Published on: November 9, 2016
 08:44
Continuous IV Infusion is the Choice Treatment Route for Arginine-vasopressin Receptor Blocker Conivaptan in Mice to Study Stroke-evoked Brain Edema
Published on: September 1, 2016
Related Concept Videos
 01:20
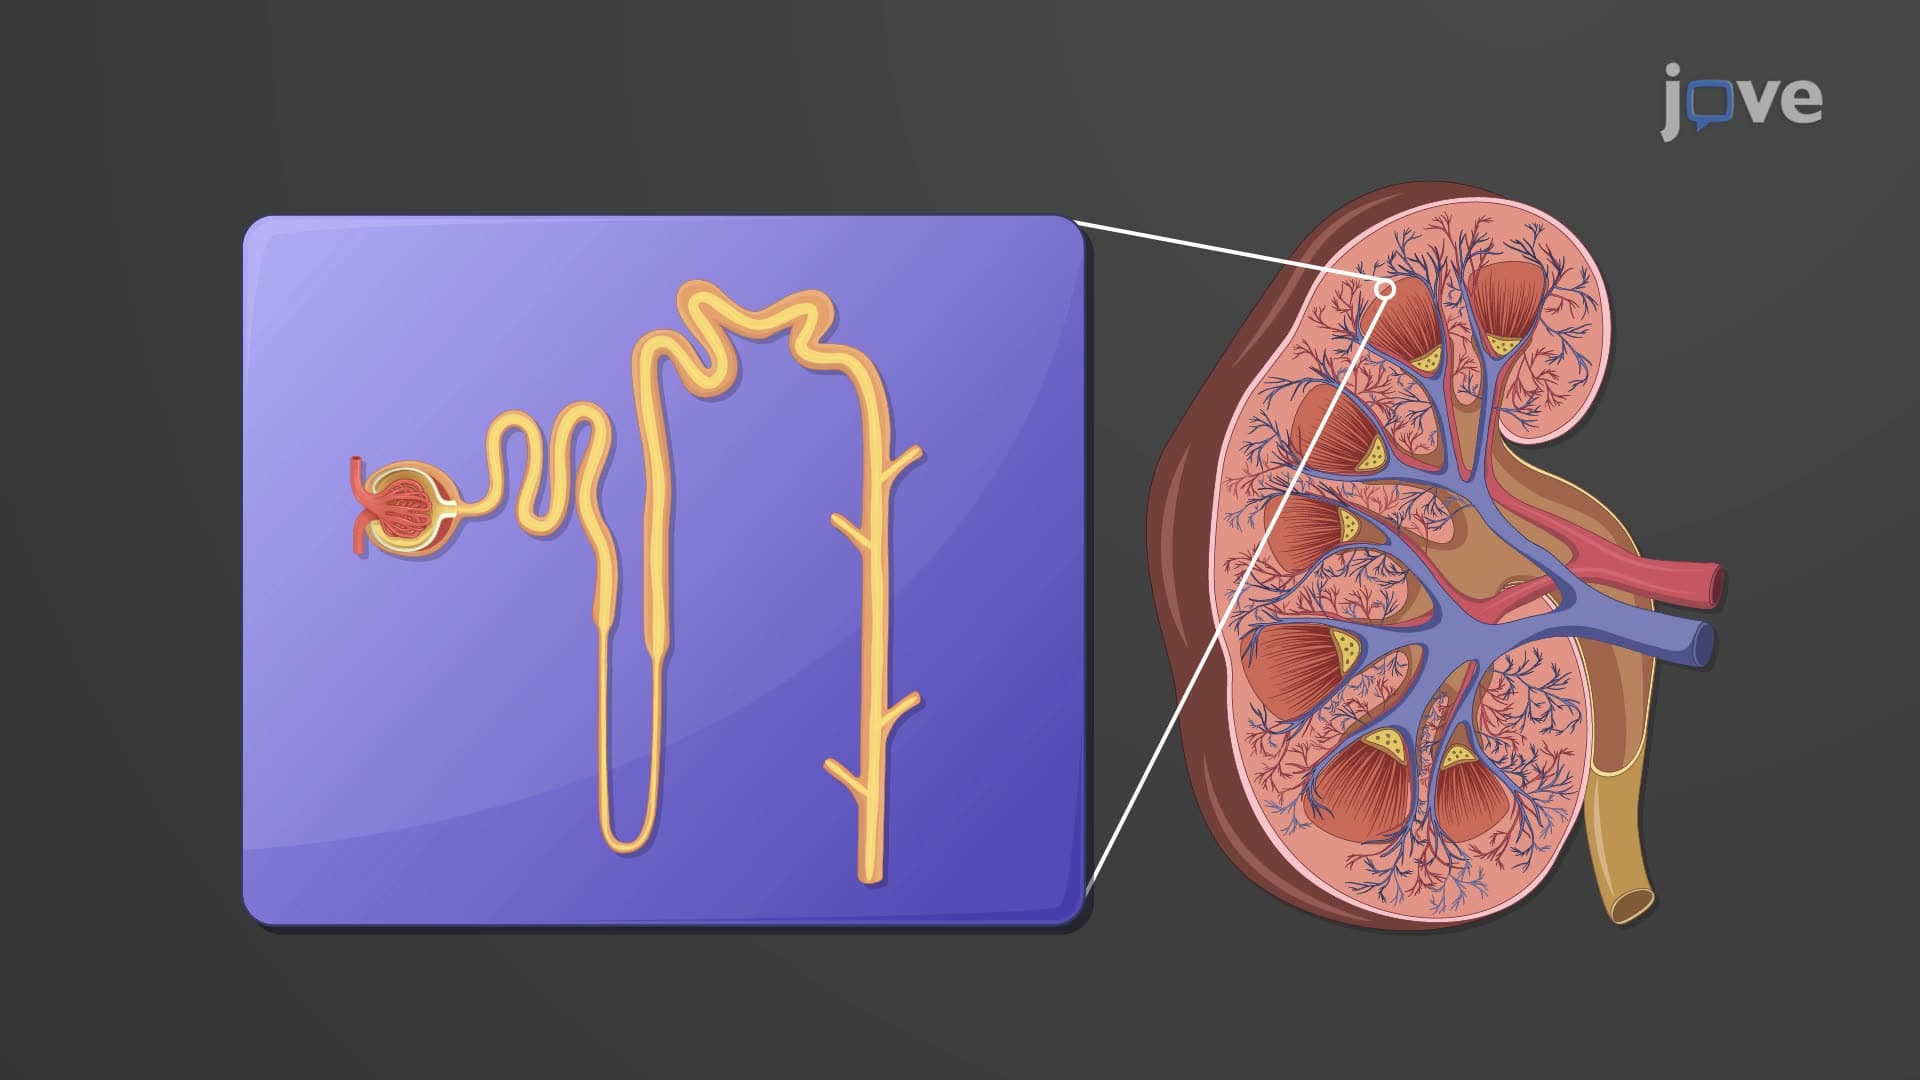
Formation of Dilute Urine
Filtrate Osmolarity in the PCT
Initially, as the filtrate passes through the proximal convoluted tubule (PCT), its...
 01:23
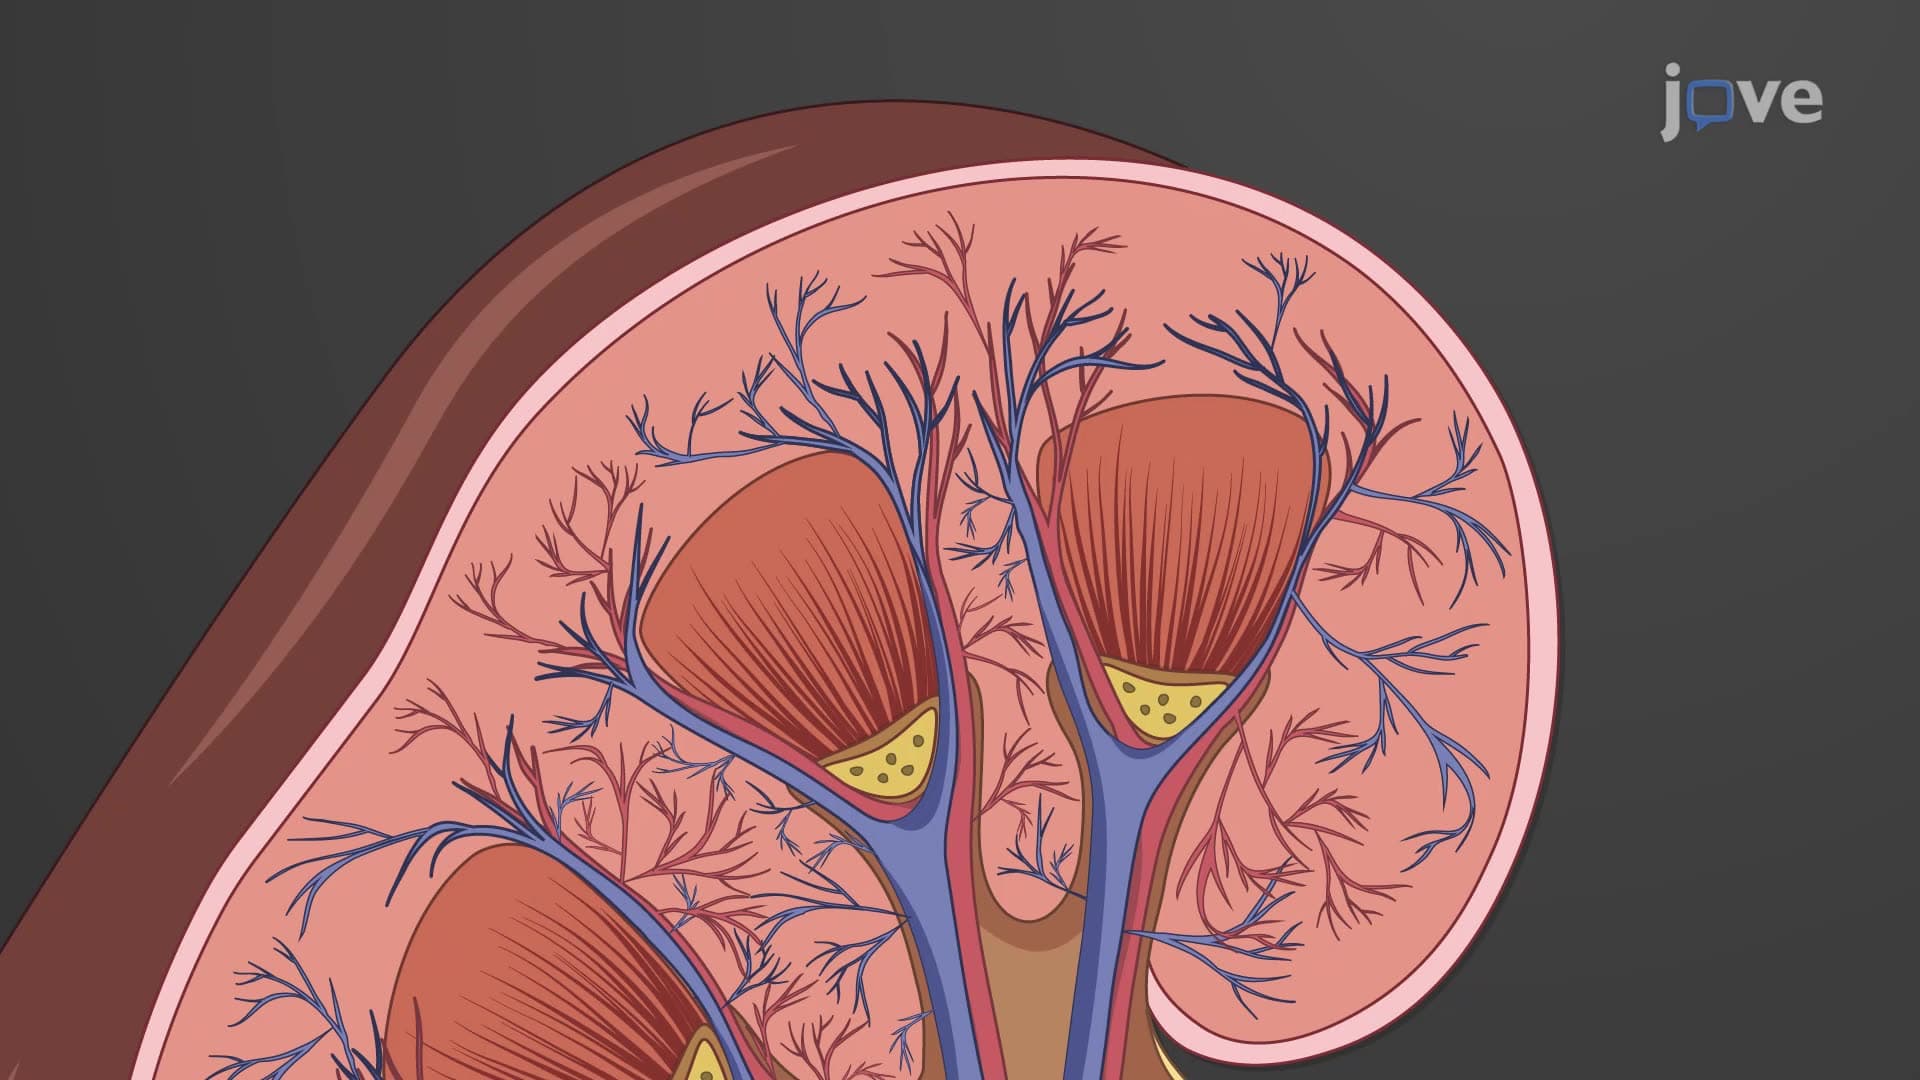
Formation of Concentrated Urine
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:27
Dialysis
Acute kidney injury develops suddenly and can be caused by pre-renal causes (e.g., hypovolemia, shock), intrinsic renal causes (e.g., acute tubular necrosis), or post-renal causes (e.g., urinary obstruction). In contrast, chronic renal failure progresses gradually over time and is often...
 01:25
Regulation of Water Intake
 01:22
Heart Failure Drugs: Diuretics