Related Experiment Video
Updated: May 12, 2026

A Familial Hypercholesterolemia Human Liver Chimeric Mouse Model Using Induced Pluripotent Stem Cell-derived Hepatocytes
Published on: September 15, 2018
Hepatic Form of Dihydrolipoamide Dehydrogenase Deficiency (DLDD): Phenotypic Spectrum, Laboratory Findings, and
Nicole Hammann1, Christian Staufner1, Lea Dewi Schlieben2,3
1Heidelberg University, Medical Faculty, University Hospital Heidelberg, Center for Child and Adolescent Medicine, Division of Pediatric Neurology and Metabolic Medicine, Heidelberg, Germany.

Abstract:
Dihydrolipoamide dehydrogenase deficiency (MIM 246900/DLDD) is an autosomal recessive mitochondrial disease with three clinical subgroups. The hepatic form leads to recurrent metabolic decompensations often accompanied by elevated levels of liver transaminases (ELT) in blood, sometimes progressing to acute liver failure (ALF). Genetically, it is linked to the p.G229C variant in the DLD gene, which has been reported in the Ashkenazi Jewish and Arabic population. In this study, we analyzed phenotypic diversity, therapeutic management, and outcome in novel symptomatic individuals with hepatic DLDD identified by whole exome sequencing (n = 7) in Central Europe as well as in previously reported cases (n = 45). Fifty-one of 52 DLDD patients carried the p.G229C variant (39 in a homozygous state). During decompensations, precipitated by febrile infectious disease or fasting, affected individuals presented with nausea, vomiting, abdominal pain, hepatomegaly, hypoglycemia, and lactic acidosis. In individuals homozygous for the p.G229C variant, neurologic manifestations were rare, whereas mild neurologic symptoms were found in individuals (n = 8) carrying a different DLD variant in trans. During decompensation, levels of specific plasma amino acids like citrulline or branched-chain amino acids, and urinary organic acids, like 2-oxoglutaric acid, were frequently elevated. However, known biomarkers-with the exception of lactate-were not consistently elevated during these episodes and typically normal in the interval, highlighting the usefulness of early genetic testing in all children with unexplained ELT or ALF to reduce the time to diagnosis. While there exists consensus for rescue therapy with intravenous glucose during decompensations and maintenance therapy with riboflavin, therapies with thiamine and antioxidants (e.g., N-acetylcysteine) were reported to be useful in single individuals with recurrent decompensations.


Related Concept Videos
 01:22
Lysosomal Hydrolases
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
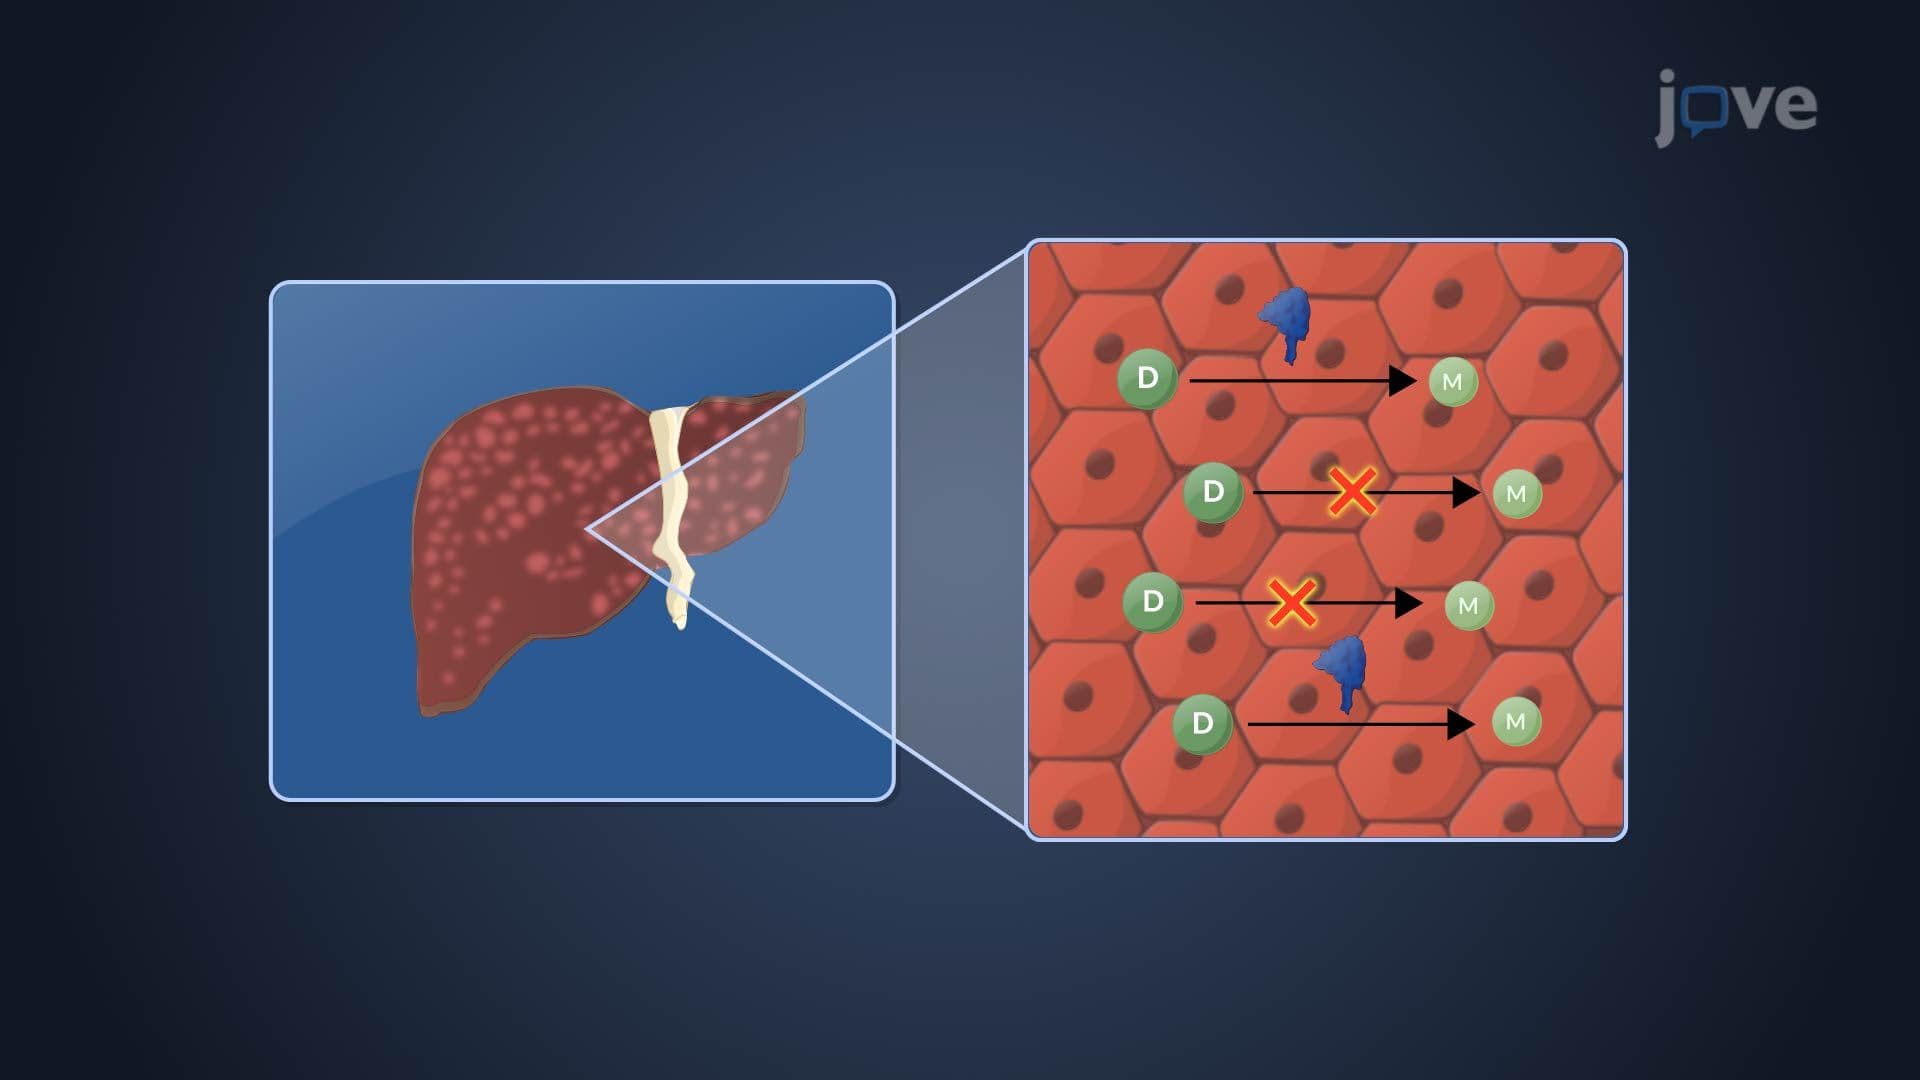 01:14
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:16
Drug toxicity: Idiosyncratic Reactions