Related Experiment Video
Updated: Jun 22, 2026
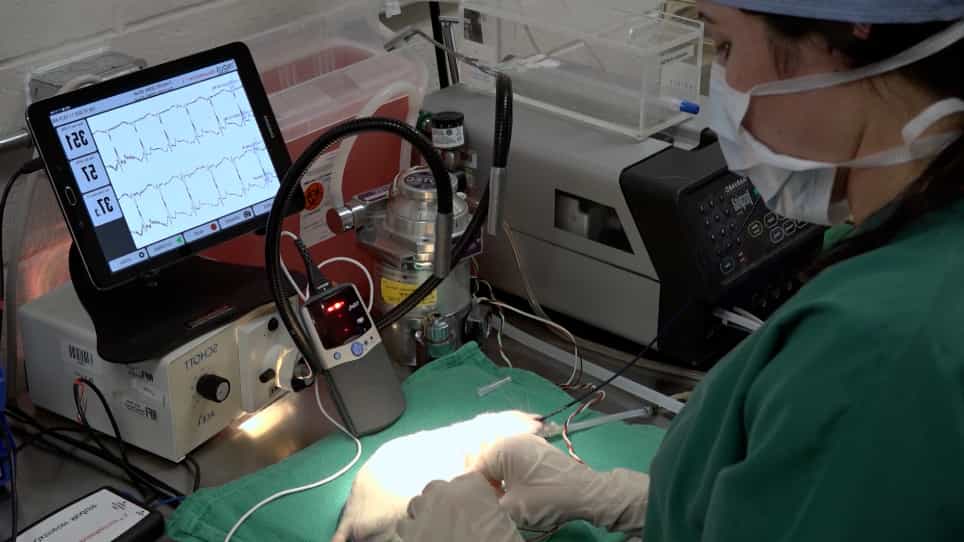

An Image Guided Transapical Mitral Valve Leaflet Puncture Model of Controlled Volume Overload from Mitral Regurgitation in the Rat
Published on: May 19, 2020
The MATTERHORN trial: Percutaneous MitraClip vs surgical repair in heart-failure-related secondary mitral
1Aswan Heart Centre (AHC), Aswan, Egypt.

Abstract:
Introduction: Functional mitral regurgitation (FMR) is a common complication of heart failure and is associated with poor prognosis and increased morbidity and mortality. Surgical mitral valve repair (MVRe) and MitraClip transcatheter edge-to-edge repair (M-TEER) are used to improve FMR, however, there has not been sufficient comparison between the benefits of both approaches. The MATTERHORN trial aimed to compare the efficacy and safety outcomes of percutaneous versus surgical repair in high-risk patients with heart failure and FMR, to determine the noninferiority of transcatheter edge-to-edge therapy in this population. Study and results: 208 patients were randomized in a 1:1 ratio to either M-TEER with MitraClip device or surgical mitral valve repair or replacement. The average age was 70.5 ± 7.9 years, 39.9% were female, mean LVEF was 43.0 ± 11.7%, 85.7% of patients had NYHA class III or IV, 96.0% had Mitral regurgitation grade ≥3, 38.2% had grade 4+, median effective regurgitant orifice area was 0.22cm2 and the mean regurgitant fraction was 57.0 ± 21.0%. Successful repair was seen in 96.1% in the M-TEER group and 98.6% in the surgery group. At 1 year, at least one primary endpoint event (death, hospitalization for heart failure, mitral valve re-intervention, implantation of an assist device, or stroke) occurred in 16.7% of the M-TEER group and 22.5% of the surgery group. All-cause death occurred in 8.3% and 10.3% of patients, respectively. Recurrence of MR grade ≥3 at 1 year and mitral valve reintervention was 8.9% and 5% in the M-TEER group and 1.5% and 2% in the surgical group, respectively. Overall, 41.0% of the patients in the intervention group and 77.3% in the surgery group had at least one adverse event, of which 35% and 66%, respectively, were serious. Lessons learned: Transcatheter edge-to-edge repair demonstrated noninferiority to surgery for a composite of death, rehospitalization for heart failure, stroke, reintervention, or assist device implantation at 1-year. M-TEER exhibited significantly fewer major adverse events within 30 days post-procedure, albeit with a slightly higher MR recurrence rate at one year. This study underscores the potential of M-TEER as a less-invasive, yet effective, alternative to surgery for FMR, mitigating surgical risks and offering a faster recovery path, especially for patients deemed unsuitable for surgery. However, long-term data is crucial for guiding policies.


Related Concept Videos
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:20
Mitral Regurgitation I: Introduction
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests
 01:25
Mitral Regurgitation III: Medical Management
 01:28
Mitral Regurgitation IV: Nursing Management
 01:26
Mitral Stenosis III: Medical Management