Related Experiment Video
Updated: Jan 18, 2026
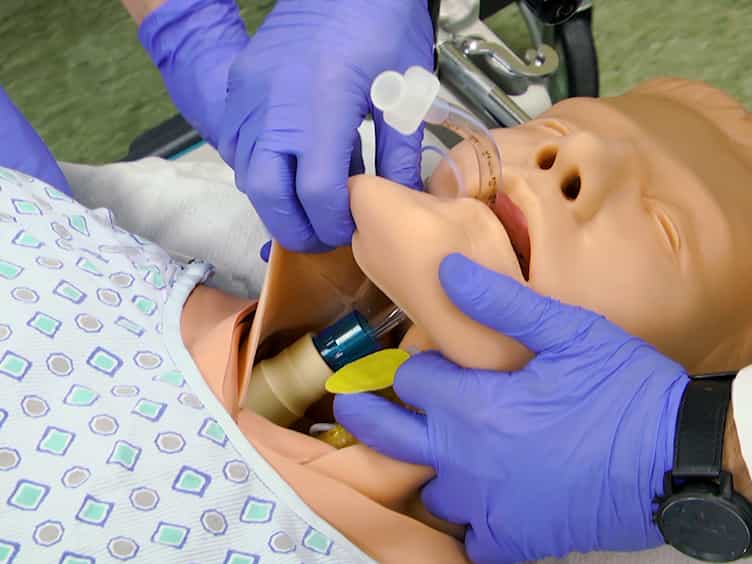

Mechanical Ventilation Boot Camp Curriculum
Published on: March 12, 2018
Medical Direction Needs Analysis: Codifying a Medical Directors Course to Meet the Demands of Modern Combat Care
Joshua Lowe1,2, Eric Kretz1, Emily Raetz1,2
1Department of Emergency Medicine, Brooke Army Medical Center, Fort Sam Houston, TX 78234, United States.

Introduction:
The role of Prehospital Medical Directors is pivotal in military medicine, integrating emergency medical services within the military's trauma system, particularly within the framework of Large-Scale Combat Operations (LSCO). This study aims to explore the impact of the current training variability among emergency medicine (EM) physicians, the only physicians required to receive any Emergency Medical Services (EMS) training in residency and thus the current gold standard, on their ability to effectively manage and direct medical operations in LSCO scenarios. The study focuses on understanding the training needs, leveraging technological advances, and adapting to high-intensity military medical operations.
Materials And Methods:
This cross-sectional study was approved by the Institutional Review Board of the Uniformed Services University of the Health Sciences. Data were collected using an online survey disseminated via Qualtrics XM Platform to active-duty EM physicians across U.S. military branches. The survey, which remained open from January 1, 2024 to September 30, 2024, evaluated the training, experience, and comfort levels of respondents in providing medical direction. Statistical analysis involved descriptive statistics, independent t-tests, and analysis of variance to identify significant disparities in training outcomes.
Results:
The survey yielded responses from 139 EM physicians, revealing significant variability in EMS training across residency programs. Results demonstrate that physicians who had received a crash course reported consistently higher comfort levels in performing critical medical direction tasks. Specifically, these physicians reported greater proficiency in teaching medics (74.7 ± 13.6 vs. 67.9 ± 25.0, P = .0326), establishing protocols (76.9 ± 17.3 vs. 63.4 ± 27.6, P = .0079), providing QA/QI feedback (74.2 ± 17.7 vs. 66.6 ± 27.8, P = .0549), and guiding complicated resuscitations (77.3 ± 15.3 vs. 65.3 ± 28.6, P = .0087) and procedures over the radio (74.3 ± 19.4 vs. 64.2 ± 27.6, P = .0373) compared to the respondents without training outside of residency. Conversely, physicians without supplementary training and no practical exposure reported the lowest self-perceived proficiency, particularly in high-stakes LSCO scenarios.
Conclusions:
The study confirms a critical gap in the preparedness of EM physicians to serve as Medical Directors in LSCO, largely because of inconsistent EMS training during residency. These findings underscore the "Walker Dip" phenomenon-an observed decline in casualty survival rates when transitioning from peacetime to initial conflict phases due to inadequate medical service adaptation. The results support the need for standardized, comprehensive training programs that incorporate Tactical Combat Casualty Care principles, advanced decision-making skills, and the use of modern technology for remote medical direction. Addressing these training disparities can enhance the operational readiness and effectiveness of military medical teams. Future research should focus on developing a centralized training curriculum that aligns with the evolving demands of modern military operations and tests its efficacy in improving prehospital and battlefield medical outcomes.
More Related Videos

Related Concept Videos
 01:15
Methods of Documentation VI: Case Management Model
For example, a patient with a chronic...
 01:23
Methods of Documentation V: CBE
In CBE, healthcare professionals establish predefined standards of practice that define what constitutes...
 01:19
Standards of Care II
 01:22
Standards of Care I
 01:26
Methods of Documentation II: POMR
 01:26
Guidelines for Nursing Documentation II
Timely documentation is crucial to ensure continuity of care for patients. Any delays in recording or reporting medical information can result in medical errors and even adverse patient outcomes. From medication administration to diagnostic test results, every detail must be accurately and promptly documented to provide the best possible care for patients.