Related Experiment Video
Updated: Sep 19, 2025
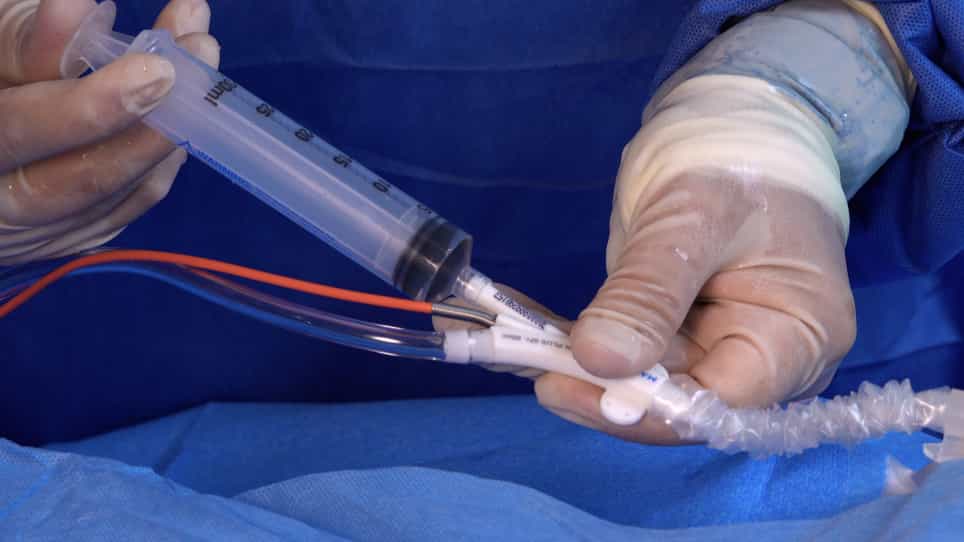

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Time to rethink the prioritization of IABP patients in heart allocation systems worldwide?
C Delmas1, C Vandenbriele2, G Baudry3
1Intensive Cardiac Care Unit, University Hospital of Toulouse, Toulouse, France; Université Paul Sabatier - Toulouse III, Toulouse, France; Recherche et Enseignement en Insuffisance Cardiaque Avancée, Transplantation et Assistance (REICATRA), Institut Saint Jacques, Toulouse, France.

The intra-aortic balloon pump (IABP) remains widely used in clinical practice despite increasing evidence questioning its efficacy and safety. Designed as a simple temporary mechanical circulatory support device, IABP might offer benefits such as afterload reduction, cardiac output enhancement, and coronary perfusion improvement. However, large randomized controlled trials such as IABP-SHOCK II and CRISP MI have failed to demonstrate a survival benefit in acute myocardial infarction related cardiogenic shock. The ALTSHOCK2 study recently failed to show a clinical advantage of IABP-therapy in patients with heart failure-related cardiogenic shock. The use of IABP as a bridge to transplantation is particularly common in countries where national allocation systems prioritize patients on IABP support. The results of the recent ALTSHOCK2-trial question the justification for its continued inclusion in prioritization models. Hence, we examine the physiological effects of IABP, its application in shock states and low cardiac-output syndrome, and its role in transplantation allocation policies worldwide. In line with the present data, we call for a reevaluation of its role in clinical practice and transplant allocation to align with strong clinical evidence.
The intra-aortic balloon pump (IABP) remains widely used in clinical practice despite increasing evidence questioning its efficacy and safety. Designed as a simple temporary mechanical circulatory support device, IABP might offer benefits such as afterload reduction, cardiac output enhancement, and coronary perfusion improvement. However, large randomized controlled trials such as IABP-SHOCK II and CRISP MI have failed to demonstrate a survival benefit in acute myocardial infarction related cardiogenic shock. The ALTSHOCK2 study recently failed to show a clinical advantage of IABP-therapy in patients with heart failure-related cardiogenic shock. The use of IABP as a bridge to transplantation is particularly common in countries where national allocation systems prioritize patients on IABP support. The results of the recent ALTSHOCK2-trial question the justification for its continued inclusion in prioritization models. Hence, we examine the physiological effects of IABP, its application in shock states and low cardiac-output syndrome, and its role in transplantation allocation policies worldwide. In line with the present data, we call for a reevaluation of its role in clinical practice and transplant allocation to align with strong clinical evidence.


