Related Experiment Video
Updated: Jun 16, 2025
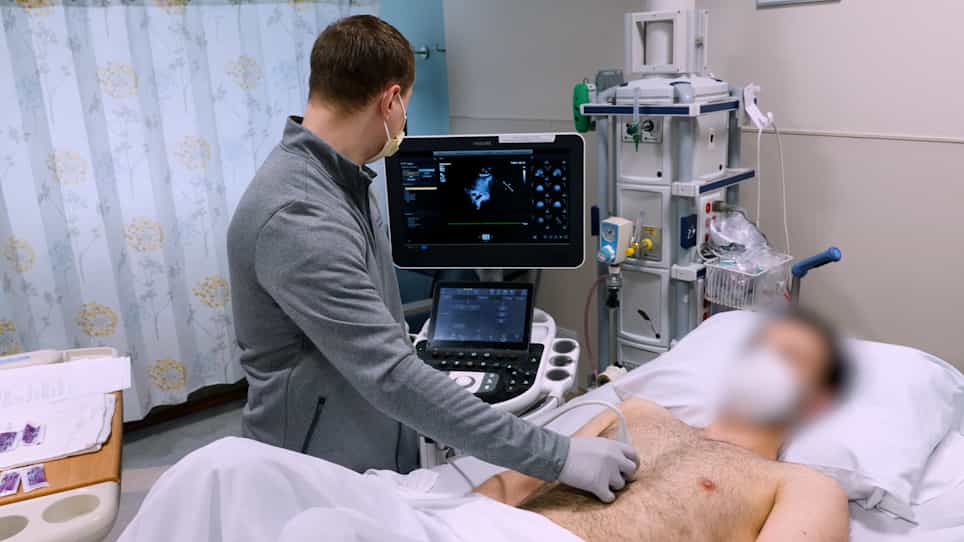

Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
Influence of Increased Intra-Abdominal Pressure on the Validity of Ultrasound-Derived Inferior Vena Cava Measurements
Mia Rora Bertović1,2, Vladimir Trkulja3, Ela Ćurčić Karabaić1,2
1Department of Intensive Care Unit, Division of Internal Medicine, University Hospital Center Zagreb, 10000 Zagreb, Croatia.

Abstract:
Background: Ultrasound-based assessment of the inferior vena cava (IVC) is a widely used, non-invasive tool for estimating volume status and central venous pressure (CVP) in critically ill patients. However, elevated intra-abdominal pressure (IAP) may distort IVC measurements, reducing the accuracy of CVP estimation. This study aimed to quantify the effect of varying IAP on IVC diameters and evaluate the accuracy of ultrasound-based CVP predictions under such conditions. Methods: A prospective study was conducted including two groups of adult critically ill patients: one with spontaneously elevated IAP due to ascites (n = 36), undergoing stepwise pressure reduction via paracentesis, and one with normal baseline IAP (n = 30), undergoing stepwise pressure elevation using an abdominal belt with an inflatable balloon. End-inspiratory and end-expiratory IVC diameters and CVP were repeatedly measured at different IAP levels. Agreement between predicted and measured CVP was assessed using Gwet's agreement coefficient, and a correction model for IVC diameters was developed based on IAP categories. Results: Increasing IAP led to a progressive reduction in both inspiratory and expiratory IVC diameters, while CVP showed no consistent trend. Predictive accuracy declined with rising IAP, with Gwet's agreement coefficient decreasing from 0.851 (95 percent confidence interval: 0.750-0.952) at normal pressure to 0.392 (95 percent confidence interval: 0.141-0.642) at IAP above 25 mmHg. Applying the correction model improved prediction accuracy, with Gwet's agreement coefficient increasing to 0.749 (95 percent confidence interval: 0.589-0.908) at the highest IAP category. Conclusions: Elevated IAP significantly alters IVC diameters and reduces the reliability of ultrasound-based CVP estimation. A correction model based on IAP improves predictive accuracy and may enhance volume assessment in critically ill patients. Further validation is warranted.