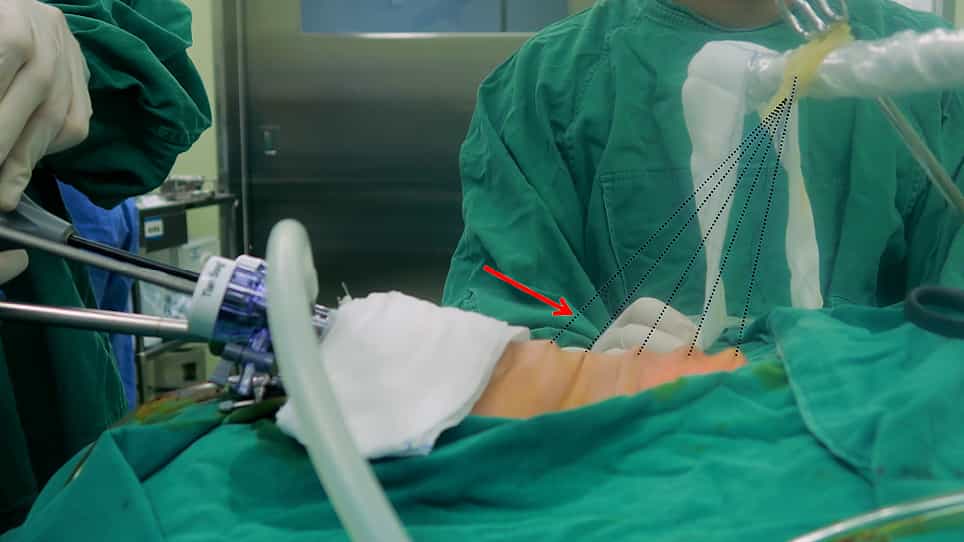
Related Experiment Video
Updated: Sep 19, 2025


Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Outcomes with Sublobar Resection vs Lobectomy in Patients With cT1N0M0 Large-cell Neuroendocrine Cancer
Yota Suzuki1, Ian G Christie1, Inderpal S Sarkaria2
1Department of Cardiothoracic Surgery, University of Pittsburgh Medical Center, Pittsburgh, Pennsylvania.

Background:
Large-cell neuroendocrine cancer (LCNEC) is a rare tumor histology associated with poor prognosis. This study aimed to analyze outcomes with sublobar resection in patients with clinical T1N0M0 LCNEC (<3 cm) compared with lobectomy.
Methods:
We performed a single-institution, retrospective study comparing patients undergoing lobectomy vs sublobar resection (segmentectomy or wedge resection) for clinical T1N0M0 LCNEC from 2002 2022. We performed unmatched and propensity-matched comparisons for overall survival and recurrence-free survival.
Results:
During the study period, 62 lobectomies and 34 sublobar resections (20 segmentectomies and 14 wedge resections) were performed for clinical T1N0M0 LCNEC. Correct pre-/intraoperative histologic diagnosis was made only for 21 patients receiving lobectomy (33.9%) and 10 patients receiving sublobar resection (29.4%). In the unmatched cohort, there was no difference in overall survival (median, 65.6 vs 65.4 months; P = .133) and recurrence-free survival (median, 36.9 vs 31.1 months; P = .210). Sublobar resection was associated with a higher locoregional recurrence rate (44.1% vs 14.5%; P = .003), while the overall recurrence rate was not significantly different (50.0% vs 37.1%; P = .280). In the matched cohort with 22 patients on each arm, there was no difference in overall survival (median, 65.6 vs 57.8 months; P = .308) and recurrence-free survival (median 27.1 vs 20.4 months; P = .290).
Conclusions:
LCNEC is a diagnostic challenge with pre-/intra-operative biopsy. For cT1N0M0 LCNEC, even though the survival was not inferior, sublobar resection could be inferior in long-term locoregional disease control. An individualized approach is warranted in case LCNEC is diagnosed after sublobar resection.