Related Experiment Video
Updated: Sep 19, 2025


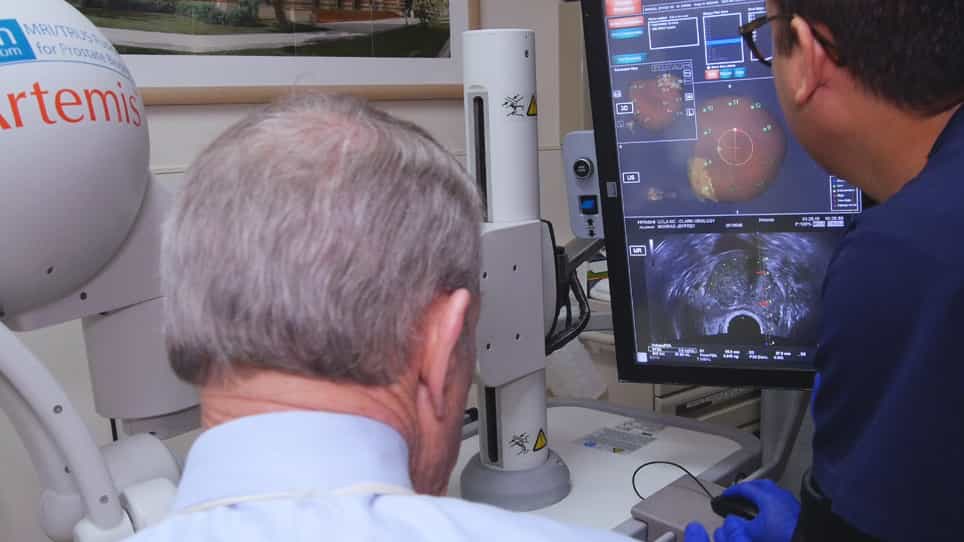
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
A comprehensive scoring system integrating clinical and radiological variables for the detection of clinically
Liqin Yang1, Zhenwei Ding2, Xu Wang3
1Hangzhou Traditional Chinese Medicine Hospital Affiliated to Zhejiang Chinese Medical University, Hangzhou, China.

Purpose:
To develop and validate a scoring system that combines clinical and radiological variables to predict the likelihood of clinically significant prostate cancer (csPCa, which is defined as Gleason Grade group ≥ 2) before biopsy and stratify patients by predicted risk.
Methods:
This retrospective study enrolled 788 patients. Data were stratified into a derivation cohort and two validation cohorts by institutions. Imaging evaluation included: Prostate Imaging Reporting and Data System v2.1 (PI-RADS v2.1), Simplified PI-RADS [S-PI-RADS, incorporating qualitative and quantitative assessment of diffusion restriction degree and lesion volume (LV) on DWI/ADC sequences], prostate volume (PV), LV, and the longest to shortest diameter ratio (LD/SD). %fPSA was the ratio of free prostate-specific antigen (PSA) to total PSA (tPSA). The adjusted PSA (aPSA) was derived as: aPSA = tPSA×(LV/PV). Independent csPCa predictors were determined through multivariate regression analysis and transformed into the scoring system. Diagnostic performance of PI-RADS, S-PI-RADS, and the scoring system were compared using ROC analysis. The scoring system was stratified into four risk categories based on total scores.
Results:
The scoring system-integrating %fPSA, S-PI-RADS, aPSA, and LD/SD-demonstrated robust predictive performance for csPCa across all derivation and validation cohorts (AUC: 0.891, 0.875, and 0.897, respectively), comparable to PI-RADS (AUC: 0.861, 0.880, and 0.865; all P > 0.05). It achieved the highest PPV among three systems in all cohorts (0.780, 0.832, and 0.722). Median predicted probabilities for the low (0-2 points), intermediate-low (3-7), intermediate-high (8-12), and high-risk groups (13-17) were 3.8%, 14.4%, 67.8%, and 90.3%, respectively, aligning with observed risks. While inter-reader agreement for PI-RADS was suboptimal between trained and untrained radiologists (κ = 0.643), the scoring system showed stronger consensus (κ = 0.808).
Conclusion:
This scoring system demonstrating comparable diagnostic performance to PI-RADS and improving PPV, highlighting its potential clinical practicability.

Related Concept Videos
 01:27
Imaging Studies IV: Magnetic Resonance Imaging
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:24
Magnetic Resonance Imaging