Related Experiment Video
Updated: Sep 18, 2025


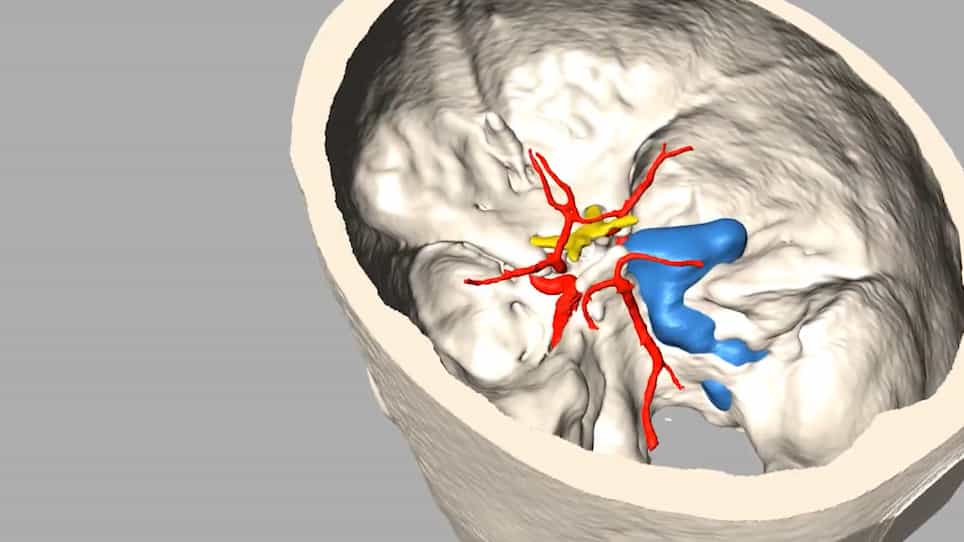
Role of Diffusion MRI Tractography in Endoscopic Endonasal Skull Base Surgery
Published on: July 5, 2021
Why 2D Matters: Comparative Evaluation of 2D and 3D T1-Weighted Imaging of the Skull Base and Neck
Amy F Juliano1, Nathan Huey2, Laura V Romo1
1From the Department of Radiology (A.F.J., L.V.R., M.P., Y.-S.C., S.F.J., K.L.R.), Massachusetts Eye and Ear, Harvard Medical School, Boston, Massachusetts.

Background And Purpose:
3D T1-weighted imaging (T1-WI) MR protocols have been proposed as time-efficient alternatives for skull base and neck imaging, but direct comparisons with conventional 2D T1-weighted TSE imaging are limited. This study aims to qualitatively and quantitatively compare 2D and 3D T1-WI of the head and neck.
Materials And Methods:
A retrospective review was conducted on 21 patients who underwent both 2D and 3D pre- and postcontrast T1-WI during the same scan session at (3T Philips 7700). Seven independent radiologists (4.5-35-years' experience) evaluated image quality using Likert scales, categoric ratings (2D better, 3D better, equivalent), and yes/no questions. Quantitative measures included region of interest intensity values in buccal fat, masseter muscle, and tumors (if present), as well as percentage delineation of 2 small-but-relevant muscles, tensor veli palatini and superior pharyngeal constrictor muscles on skull base and neck MR, respectively.
Results:
Of the 21 MRIs (10 skull base, 11 neck), contrast timing was balanced across sequences. Raters significantly favored 2D T1-weighted TSE for improved fat visualization at the skull base foramina, homogeneity of fat signal, and parotid architecture (P < .001). Tumor margins were more clearly defined on 2D neck MRI (pre- and postcontrast: P < .001, P = .04), though this was not significantly different at the skull base. 3D sequences showed less pulsation artifacts, particularly precontrast (both P < .001), but more susceptibility artifacts (both, P < .001). Quantitatively, 2D images had higher fat-to-muscle (both, P < .001) and tumor-to-muscle relative signal intensity ratios (neck: P < .001, skull base: P = .04). Delineation of the tensor veli palatini and superior pharyngeal constrictor muscles was significantly better with 2D imaging (both, P < .001). Multiplanar reformat capability from 3D imaging did not add diagnostic value in either the neck or skull base (all, P < .05).
Conclusions:
Despite advances in 3D imaging, 2D T1-WI TSE sequences continue to offer superior soft-tissue contrast and delineation in the complex anatomy of the skull base and neck. While 3D sequences reduce pulsation artifacts and provide thinner slices, their overall diagnostic utility remains less favorable due to poorer tissue contrast and increased susceptibility artifacts, particularly at tissue interfaces, especially relevant in the head and neck.