Related Experiment Video
Updated: Sep 18, 2025
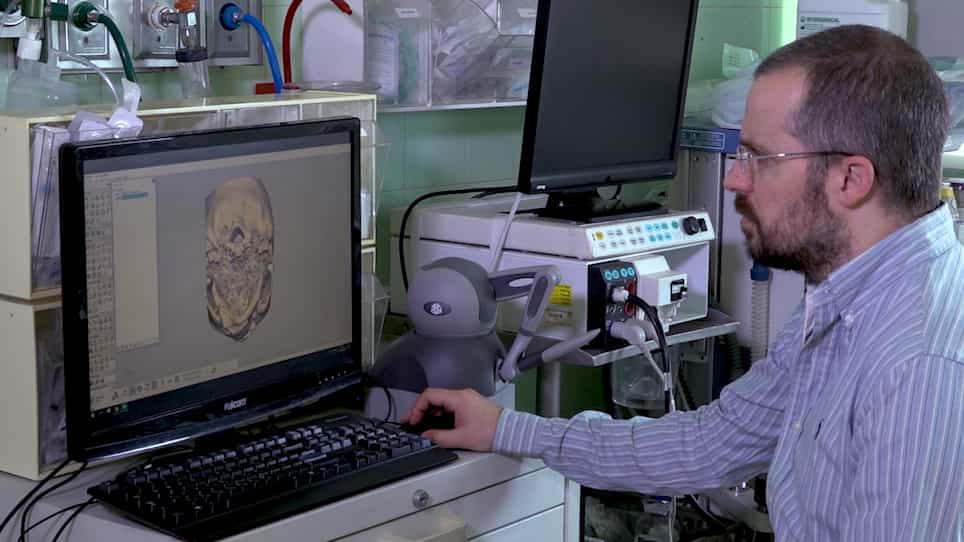

3D Planning and Printing of Patient Specific Implants for Reconstruction of Bony Defects
Published on: August 4, 2020
What Factors Influence Success of Mandibular Reconstructions With Patient-Specific Selective Laser Melted
Jeffrey S Marschall1, Mitchell Frerichs2, Thomas Keith2
1Assistant Professor, Department of Oral and Maxillofacial Surgery, University of Iowa Hospital and Clinics, Iowa City, IA.

Background:
Patient-specific reconstruction is becoming more ubiquitous in craniomaxillofacial surgery. There is a paucity of information on what factors may influence case success.
Purpose:
The purpose of the study was to estimate patient-specific hardware failure rate and to identify risk factors associated with hardware failure.
Study Design, Setting, Sample:
A retrospective cohort study was implemented using data from subjects treated with selectively laser melted (SLM) reconstruction plates at the University of Iowa. Subjects were excluded if follow-up was less than 3 months, data were not complete, or the subjects were not treated with an SLM plate.
Predictor Variables:
The predictor variables were composed of heterogenous variables grouped into the following categories: demographics, etiology, mandibular characteristics, and reconstruction plate characteristics, such as number of screws proximal and distal to fracture/defect.
Main Outcome Variable:
The primary outcome variable was time to screw failure (yes/no), which was determined by examining subject radiographic data and if it was clinical reason for the removal of the reconstruction plate.
Covariates:
The only covariate is sex.
Analyses:
Descriptive statistics were calculated for each variable. Bivariate Cox regression analyses were performed to assess the association between each variable and the hazard of screw failure. Alpha = 0.05 was considered significant.
Results:
The sample included 131 subjects. The median follow-up time was 11.0 (interquartile range 14.0) months. There was 1 (0.8%) plate fracture and 10 (7.6%) screw failures. Subjects with 1 additional screw proximal to the fracture/defect (eg, from 3 to 4, or 4 to 5, or 5 to 6) had a 63% higher hazard of screw failure at any given time over the follow-up period (hazard ratio [HR] = 1.63; P = .04; 95% CI, 1.02 to 2.63). Subjects with 1 additional screw distal to the fracture/defect had a 58% higher hazard of screw failure (HR = 1.58; P = .01; 95% CI, 1.10 to 2.26). Among patients with continuity defects (n = 49), those who received a bone graft had an 85% lower hazard of screw failure compared to those who did not receive a graft (HR = 0.15; P = .03; 95% CI, 0.03 to 0.851).
Conclusion And Relevance:
SLM reconstruction plate fracture is rare. Adding additional screws proximal and distal to a fracture/defect may lead to a higher hazard of hardware failure. Using a bone graft for continuity defects may lead to a lower hazard of hardware failure.

