Related Experiment Video
Updated: Jul 30, 2026
Dynamic Lung Tumor Tracking for Stereotactic Ablative Body Radiation Therapy
Published on: June 7, 2015
Clinically tenable lung dose estimates in 90 Y radioembolization from truncated macro-aggregated albumin-single
M Allan Thomas1, Sam Meiselman, J Daniel Giardina
1Mallinckrodt Institute of Radiology, Washington University School of Medicine, St. Louis, Missouri, USA.

Objective:
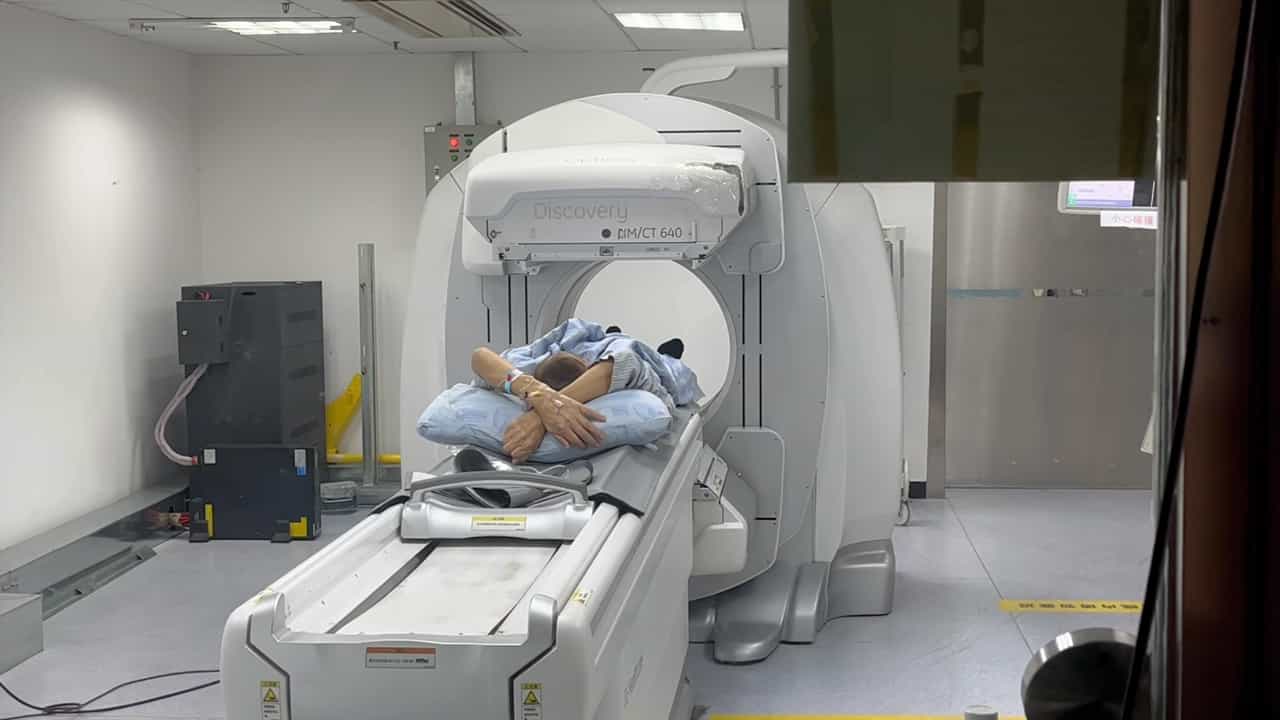
Relative to planar imaging, macro-aggregated albumin-single photon emission tomography/computed tomography (MAA-SPECT/CT) offers more reliable lung shunt fraction (LSF) and lung mean dose (LMD) estimates in 90 Y radioembolization. But lung truncation in SPECT/CT can limit its utility, yielding uncertain LSF and LMD estimates. Here, the effects of lung mass on LSF and LMD corrections for lung truncation in SPECT/CT were analyzed.
Methods:
106 cases with planar LSF > 8% were analyzed. Lung truncation was simulated in 30 cases with full lung coverage, while 50 cases with clinical truncation were also assessed. Five LMD estimates were computed: (1) planar-imaging, 1-kg lung-mass (Planar 1-kg ), (2) planar-imaging, patient-specific lung-mass (Planar), (3) uncorrected-truncated SPECT and lung-mass (SPECT Trunc ), (4) truncation-corrected SPECT, 1-kg lung-mass (SPECT 1-kg ), (5) truncation-corrected SPECT, patient-specific lung-mass (SPECT Fit ). Bland-Altman analysis (mean difference ± 95% prediction interval; PI = 1.96σ) was used to compare the LMD estimates.
Results:
Planar 1-kg and Planar LMD were comparable on average, but variability was high (mean ± 95% PI: 0.1 ± 7.8 Gy). The mean ± 95% PI in LMD for Planar 1-kg relative to nontruncated-SPECT (SPECT True ) was 10.4 ± 11.4 Gy. LMD differences relative to SPECT True were 0.3 ± 1.0 Gy for SPECT Trunc , 0.1 ± 1.0 Gy for SPECT 1-kg , and 0.1 ± 1.1 Gy for SPECT Fit . In clinically truncated cases, differences between Planar 1-kg and SPECT Trunc were again high (11.2 ± 10.3 Gy), with differences between SPECT Trunc , SPECT 1-kg , and SPECT Fit much smaller (mean <0.2 Gy, 95% PI < 2.0 Gy).
Conclusion:
The most impactful difference in estimating LMD is using SPECT/CT data in place of planar imaging. Even when lung mass is unknown or a reference value (1-kg) is used, truncated MAA-SPECT/CT offers more robust LMD estimates than planar imaging.