Related Experiment Video
Updated: Jun 19, 2026

Robotic Left Hepatectomy using Indocyanine Green Fluorescence Imaging for an Intrahepatic Complex Biliary Cyst
Published on: June 24, 2022
Step-by-step bottom-up laparoscopic right hemicolectomy with complete mesocolic excision: a technical video
Arcangelo Picciariello1,2, Francesco Corcione3, Paolo Delrio4
1Department of Experimental Medicine, University of Salento, Lecce, Italy. arcangelo.picciariello@unisalento.it.

Background:
Laparoscopic right hemicolectomy with complete mesocolic excision (CME) ensures an oncologically sound resection and aims to optimize long-term outcomes. The D2 and D3 lymphadenectomy techniques remain controversial, with unclear additional benefits from extended lymphadenectomy. This procedure's complexity is heightened by significant vascular variability. We describe the bottom-up approach for laparoscopic right hemicolectomy with CME.
Technique:
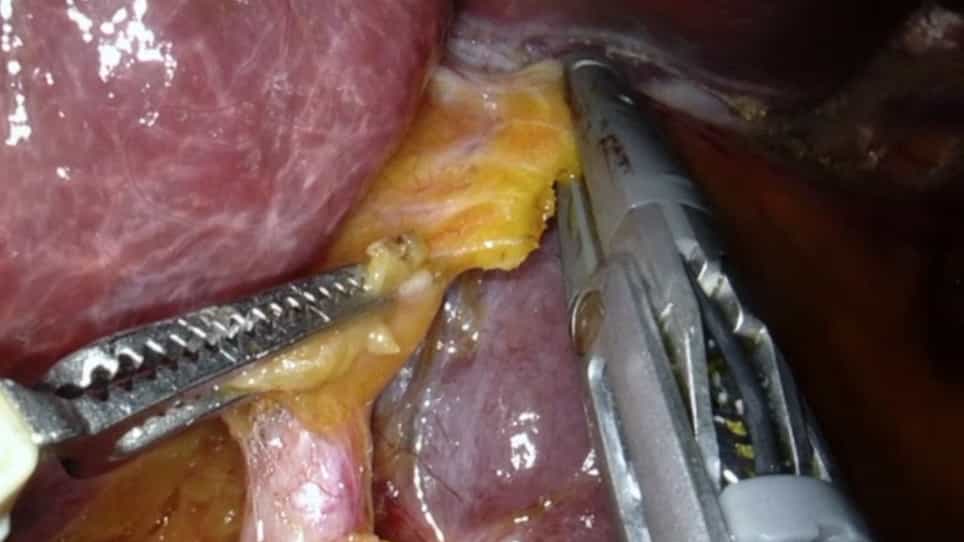
The patient is positioned in lithotomy, and trocars are placed in the suprapubic region. The peritoneum is incised near the ileocaecal junction, and the terminal ileum is lifted following the avascular plane. The mesocolon is separated from the duodenum, and vascular structures such as the ileocolic artery and vein are identified and ligated. The dissection continues around the superior mesenteric vein, the Henle's trunk, the middle colic vein, and transverse mesocolon. The transverse colon is transected distally. An intracorporeal side-to-side anastomosis is performed. The specimen is extracted via a mini-Pfannenstiel incision.
Conclusion:
The bottom-up approach could allow precise dissection and oncologically sound resection while potentially minimizing the risk of vascular injury. The mesocolon is preserved intact, and the "en bloc" resection of the tumor and mesentery is performed safely.