Related Experiment Video
Updated: Sep 19, 2026

Robotics in Surgery: A Modular Robotic Platform Driven Gastric Wedge Resection
Published on: February 7, 2025
Early implementation and feasibility of Hugo RAS system-assisted right colectomy for right-sided colon cancer: an
Kosuke Hiramatsu1, Shigeo Toda1,2, Shuichiro Matoba3,4
1Colorectal Surgery Division, Department of Gastroenterological Surgery, Toranomon Hospital, 2-2-2 Torano-Mon, Minato-Ku, Tokyo, 105-8470, Japan.

Background:
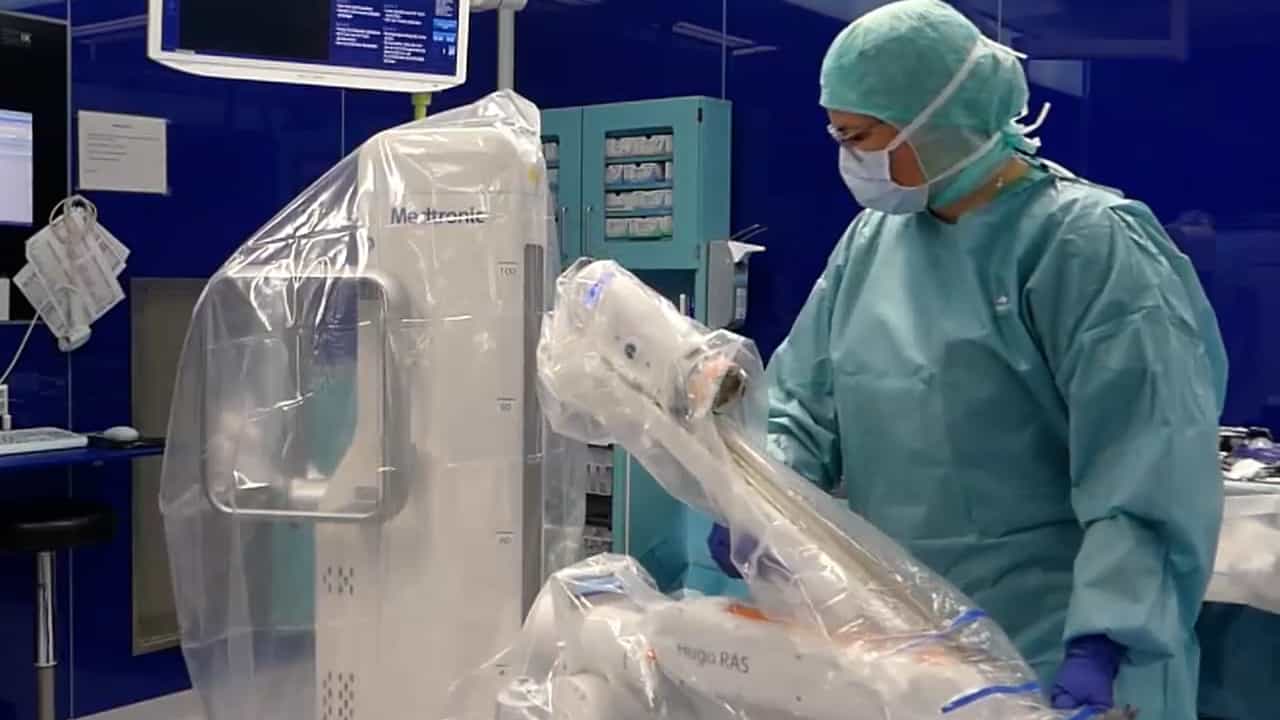
Clinical evidence for robot-assisted right colectomy (RARC) using the Hugo RAS system remains limited. We aimed to describe the early implementation experience of Hugo-assisted RARC and to preliminarily compare short-term outcomes with those of the da Vinci system.
Methods:
This dual-center retrospective cohort study included 74 patients who underwent RARC with complete mesocolic excision for right-sided colon cancer between September 2019 and April 2025. Patients who underwent multivisceral resections for non-colorectal disease or had multiple colorectal cancers were excluded. Propensity score matching (PSM) was applied at a 1:1 ratio, and the perioperative, postoperative, and pathological outcomes of 22 patients in each group treated using Hugo or da Vinci system were compared.
Results:
The baseline characteristics were more balanced after matching, although a slight imbalance remained. The console time (146 vs. 132 min; P = 0.549) and estimated blood loss (5 vs. 0 mL; P = 0.299) were comparable, but the total surgical duration was significantly longer for the Hugo group (286 vs. 246 min; P = 0.015). The pathological outcomes, including resection margins and harvested lymph nodes, were similar between groups. No conversion to open surgery, anastomotic leakage, reoperation, 30-day readmission, or mortality occurred in either group. One Clavien-Dindo grade IIIa complication unrelated to the surgery occurred in the da Vinci group. The postoperative hospital stay was comparable between the groups.
Conclusions:
The early implementation of RARC using Hugo appeared feasible and yielded acceptable short-term perioperative and pathological outcomes in a limited matched cohort. Although the total surgical duration was longer with the Hugo RAS system than with the da Vinci system, other short-term outcomes were broadly similar between the groups and should be interpreted as preliminary. Further multicenter prospective studies are needed to validate these findings and evaluate long-term oncological outcomes.