Related Experiment Video
Updated: Sep 16, 2025
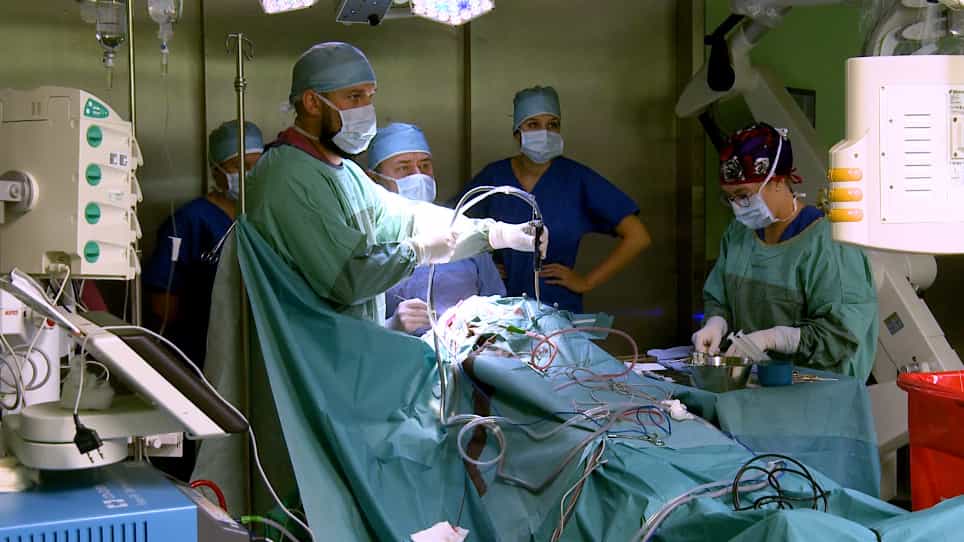

On-Site Sampling and Extraction of Brain Tumors for Metabolomics and Lipidomics Analysis
Published on: May 31, 2020
Stratification of glioblastoma patient survival based on tumor core and edge metabolomic data
Dylan A Goodin1, Hunter A Miller1, Xinmin Yin2
11Departments of Bioengineering.

Objective:
Spatial metabolic differences recently found in glioblastoma (GBM) have been linked to the infiltrating nature of the tumor edge tissue, which is mostly unresectable, and to the tumor core tissue, which resists therapy. The impact of metabolic dysregulation in core and edge GBM tissues on patient survival remains unclear. This study evaluated metabolites obtained from core and edge GBM tissues at the time of resection as biomarkers to risk stratify patients in terms of overall survival (OS).
Methods:
Paired core and edge tumor samples from 27 patients with glioma obtained after craniotomy were evaluated postsurgery with high-resolution 2D liquid chromatography-mass spectrometry/mass spectrometry, and metabolomic data for grade IV samples (n = 21) were analyzed by Kaplan-Meier survival analysis and univariable and multivariable Cox proportional hazard regression models. GBM patients were stratified into low- and high-risk groups via a linear equation based on log-transformed signal intensities of key metabolites. Risk scores were generated by summing the product of weights and metabolite signal intensities for each patient's tumor. Weights for significant metabolites were calculated by scaling the univariable Cox proportional hazard ratio for each metabolite by the standard error. For risk score validation, OS events were predicted using an Extreme Gradient Boosting model with Linear Booster (XGBL).
Results:
Kaplan-Meier survival analysis identified 6 significant metabolites in core tissue and 5 in edge tissue, respectively. Key metabolites in core and edge tissue identified through univariable Cox regression analyses combined with covariates were used to generate multivariable Cox regression models, with edge metabolites remaining significant after correction by patient sex and age at resection. Risk scores based on either 4 core or 11 edge metabolites, or the combination of both, with covariates, generated multivariable Cox regression models significantly associated with OS. Risk score derived from core metabolites remained significant after correction by covariates and was validated with XGBL classification model (area under the receiver operating characteristic curve = 0.876).
Conclusions:
OS of patients with GBM can be stratified based on metabolomic differences between core and edge tumor tissues.
More Related Videos
 05:45
Quantitative Immunohistochemistry of the Cellular Microenvironment in Patient Glioblastoma Resections
Published on: July 31, 2017
 09:09
Laser Capture Microdissection of Glioma Subregions for Spatial and Molecular Characterization of Intratumoral Heterogeneity, Oncostreams, and Invasion
Published on: April 12, 2020
Related Concept Videos
 01:21
Cancer Survival Analysis
 02:07
Tumor Progression
Colon cancer is one of the best-documented examples of tumor progression. Early mutation in the APC gene in colon cells causes a small growth on the colon wall called a polyp. With time, this polyp grows into a benign, pre-cancerous tumor. Further...