Related Experiment Video
Updated: Sep 15, 2025
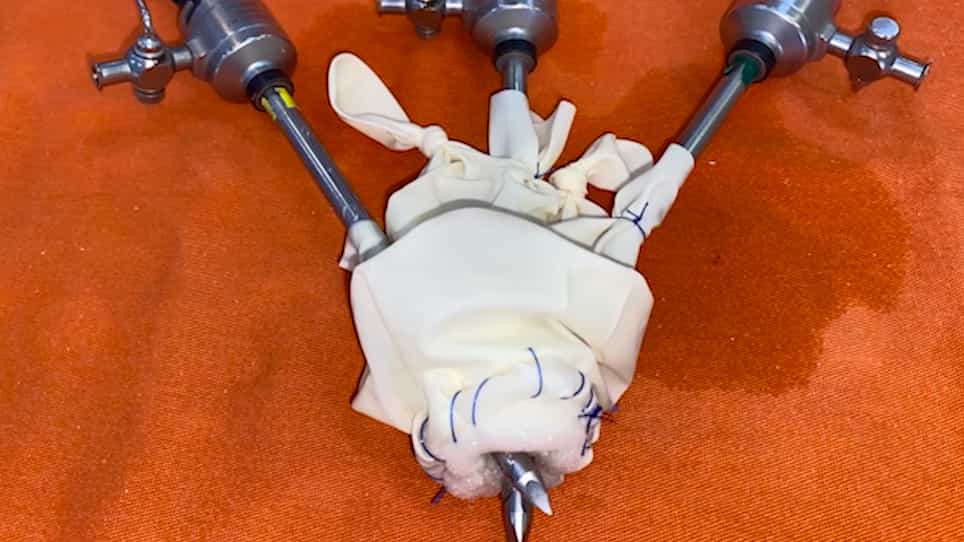

Low-Cost Single-Port LoCoSP Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
Short-term outcomes of robot-assisted transcervical esophagectomy for thoracic esophageal carcinoma
Takeo Fujita1, Kazuma Sato2, Yuto Kubo2
1Division of Esophageal Surgery, National Cancer Center Hospital East, 6-5-1 Kashiwanoha, Kashiwa, Chiba, 277-8577, Japan. takfujit@east.ncc.go.jp.

Background:
Minimally invasive robot-assisted transcervical esophagectomy (TCE) has emerged as a novel technique for thoracic esophagectomy in patients with thoracic esophageal carcinoma, with sporadic reports highlighting its feasibility. However, its short-term surgical outcomes and safety profile in a well-defined series with a substantial number of cases remain unclear. This study aims to address this knowledge gap by systematically evaluating the feasibility and safety of this approach.
Methods:
Fifty patients undergoing robot-assisted TCE between 2023 and 2024 were included. At our institution, robot-assisted TCE is reserved for patients with previous thoracic surgery, poor performance status, or other conditions contraindicating thoracic approaches. This procedure employed bilateral cervical approaches with continuous nerve-integrated monitoring in all cases. Robot-assisted TCE was performed using the da Vinci Xi system, with dissection and lymphadenectomy of the thoracic esophageal regions, including the bilateral recurrent laryngeal nerve lymph nodes.
Results:
All patients successfully underwent robot-assisted TCE with no intraoperative adverse events. The mean patient age was 73.8 years, and the male-to-female ratio was 43:7. Clinical staging was I/II/III/IV: 19/6/20/5, with 58% of patients receiving neoadjuvant chemotherapy. More than 80% had significant systemic or pulmonary comorbidities. All robot-assisted TCE procedures, including bilateral cervical dissection, were performed without intraoperative complications. Postoperative complications included recurrent laryngeal nerve paralysis (12.0%, Clavien-Dindo Grade ≥ 1) and pneumonia (6.0%, Grade ≥ 2).
Conclusions:
Robot-assisted TCE is a relatively safe and feasible technique. The transhiatal robotic approach allows for precise mediastinal lymphadenectomy. Short-term outcomes suggest acceptable rates of recurrent laryngeal nerve paralysis and pulmonary complications. Further research will focus on improving reproducibility in challenging cases and evaluating mid-term outcomes.

