Related Experiment Video
Updated: Sep 14, 2025

Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
Evaluating the generalisability of formulas used to set tidal volumes in mechanically ventilated patients: an
Aartik Sarma1, Kathryn M Sullivan2, Aaron D Baugh2
1Division of Pulmonology, Critical Care, Allergy, and Sleep Medicine, Department of Medicine, University of California, San Francisco, CA, USA; Joint Program in Computational Precision Health, University of California, San Francisco and University of California, Berkeley, CA, USA.

Background:
Lung-protective mechanical ventilation with low tidal volume (VT) decreased mortality in the ARMA trial. VT in that trial was adjusted to predicted bodyweight (PBW) as a proxy for preinjury lung volumes, an approach that is now commonly used to set target VT in patients who are mechanically ventilated. In other clinical contexts, PBW is not used to estimate lung volumes and spirometric reference equations are used instead. We aimed to compare predicted forced vital capacity (PFVC), calculated using the Global Lung Initiative 2012 spirometric reference equations, with PBW as a proxy for preinjury lung volume.
Methods:
In this observational, multicohort, retrospective study we compared ARMA PBW with PFVC estimated with the Global Lung Initiative 2012 reference equations for two cohorts: Medical Information Mart for Intensive Care-IV (MIMIC-IV), a cohort of patients from a single academic medical centre in Boston, MA, USA, and electronic Intensive Care Unit Collaborative Research Database (eICU-CRD), a cohort of patients from 208 hospitals in the USA. Patients who had lung-protective ventilation, hypoxaemia, and height in the range 150-210 cm were included. The data were collected from publicly available, deidentified datasets. We then studied the association between normalised VT (VT per PBW or VT per PFVC) and the ratio of lung volume estimates (PBW:PFVC) and mortality, driving pressure, and normalised elastance in patients receiving lung-protective ventilation with VT per PBW of 6-8 mL/kg.
Findings:
9152 patients were included from MIMIC-IV (3064 [33·5%] female and 6088 [66·5%] male; 645 [7·0%] Black, 5885 [64·3%] White, and 2622 [28·6%] other race; mean age 63 years [SD 16]) and 12 420 patients were included from eICU-CRD (4262 [34·3%] female and 8158 [65·7%] male; 1023 [8·2%] Black, 10 093 [81·3%] White, and 1304 [10·5%] other race; mean age 62 years [SD 16]). Patients who were younger, male, and White had greater PFVCs than patients who were older, female, and non-White with the same PBW. A 1 SD increase in PBW:PFVC ratio was associated with 1·43-fold (95% CI 1·17-1·76) higher odds of death in MIMIC-IV and similar results were observed in the eICU-CRD cohort.
Interpretation:
Adjusting VT using PBW formulas leads to overestimation of preinjury tidal lung volumes in patients who are older, shorter, female, and non-White compared with other patients. This algorithmic bias could contribute to mortality disparities in patients who are ventilated. Further research is required to establish the optimal tidal volumes for patients who are mechanically ventilated.
Funding:
National Heart, Lung, and Blood Institute.

Related Concept Videos
 01:22
Respiratory Volumes and Capacities
 01:29
Mechanical Ventilation I: Indication and Settings
 01:15
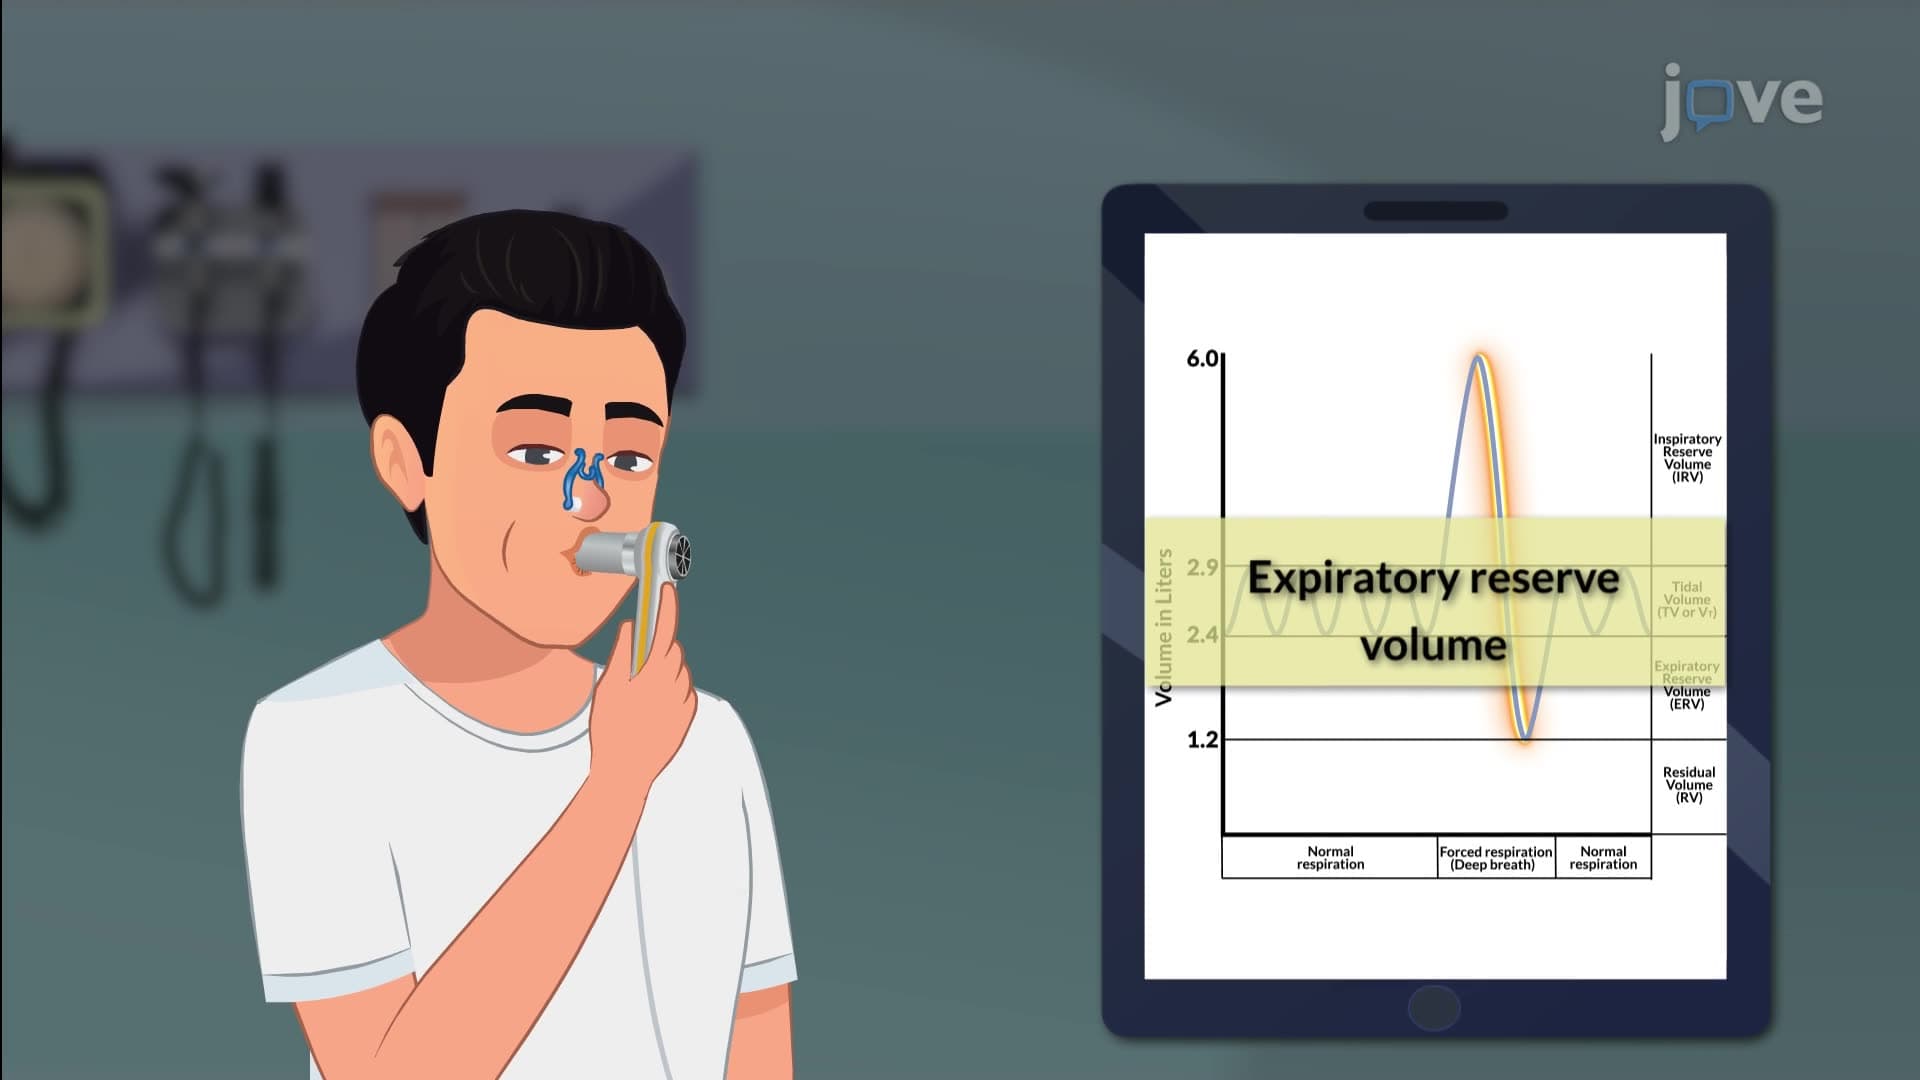
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:47
Lung Capacity