Expiratory flow limitation in highly trained endurance athletes: The role of FEF25-75% and ventilatory capacity during treadmill running
Related Experiment Video
Updated: Sep 14, 2025
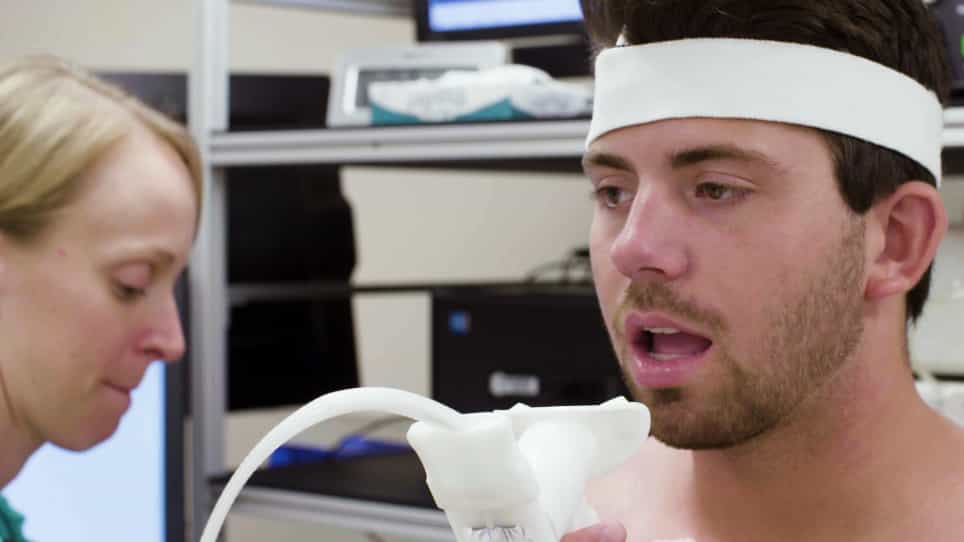
Conducting Maximal and Submaximal Endurance Exercise Testing to Measure Physiological and Biological Responses to Acute Exercise in Humans
Published on: October 17, 2018
A S Hind1, R A Mitchell1, J R Dunsford1
1Centre for Heart Lung Innovation, The University of British Columbia (UBC) and St. Paul's Hospital (SPH), Vancouver, BC V6Z 1Y6, Canada; Department of Physical Therapy, UBC, Vancouver, BC V6T 1Z4, Canada.

Background:
Expiratory flow limitation (EFL) during exercise in highly trained individuals is thought to result from increased ventilatory demands that exceed the capacity of the respiratory system, which does not fully adapt to exercise training. Reduced forced expiratory flow between 25 % and 75 % of forced vital capacity (FEF25-75 %), a marker of small airway function, may contribute to EFL by limiting the maximum expiratory flows available during the hyperpnea of exercise. This study investigated whether FEF25-75 %, peak minute ventilation (V̇E), and breathing patterns differ between highly trained endurance athletes with and without EFL.
Methods:
Forty highly trained endurance athletes (20 males and 20 females; V̇O2max: 59.6 ± 9.2 mL∙kg-1∙min-1) completed spirometry and a maximal incremental cardiopulmonary treadmill exercise test. EFL was assessed by superimposing tidal flow-volume loops within the maximum flow-volume loop according to end-expiratory lung volume.
Results:
During maximal exercise, 40 % of participants (n = 16: 7 males, 9 females) developed EFL, with no significant sex differences (P > 0.05). Athletes with EFL had significantly lower FEF25-75 % (3.45 ± 0.78 vs. 4.16 ± 0.98 L·s-1, P = 0.020, d = 0.802) and a higher ventilatory demand-to-capacity ratio (V̇E/V̇Ecap) (0.86 ± 0.14 vs. 0.66 ± 0.11, P = 0.002, d = 1.589) compared to those without EFL. There were no significant differences in absolute tidal volume, breathing frequency or V̇E between groups (P > 0.05).
Conclusion:
In a homogeneous cohort of highly trained endurance athletes, EFL during maximal treadmill exercise appears to be primarily driven by a reduced capacity to generate expiratory flow, as evidenced by lower FEF25-75 %, rather than differences in ventilatory demand.
More Related Videos
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
 07:09
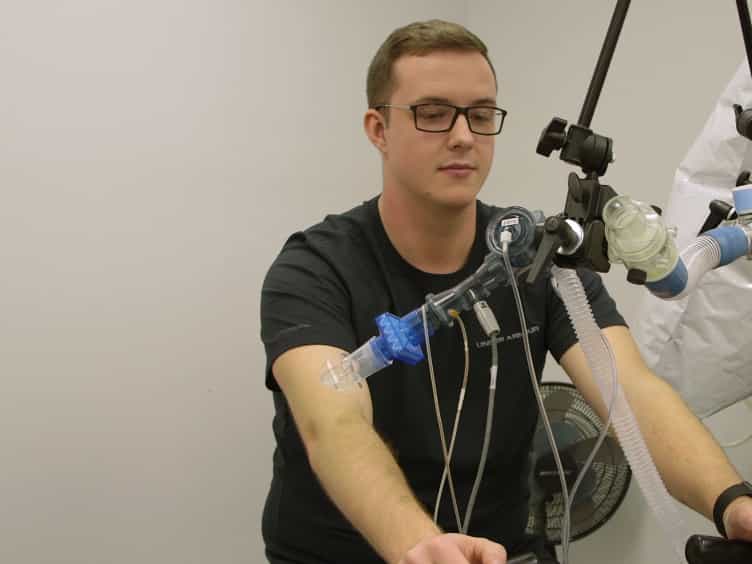
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:26
Respiratory Volumes and Capacities I
 01:22
Respiratory Volumes and Capacities
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:47
Lung Capacity