Effect of Scaling Peak Oxygen Uptake for Body Size and Composition to Assess Cardiometabolic Risk in Children
Related Experiment Video
Updated: Sep 14, 2025

Assessment of Child Anthropometry in a Large Epidemiologic Study
Published on: February 2, 2017
Laura Emily Macro1, Dimitris Vlachopoulos1, Eero A Haapala
1Children's Health and Exercise Research Centre, Public Health and Sport Sciences, University of Exeter, Exeter, UNITED KINGDOM.

Purpose:
This study measured associations of peak oxygen uptake (V̇O 2peak ) with cardiometabolic risk factors and quantified cardiometabolic risk misclassification when scaling V̇O 2peak for body size and composition, comparing population-specific and universal V̇O 2peak cut points.
Methods:
In a population sample of 332 Finnish children (164 girls, 9-11 yr), V̇O 2peak was determined using a maximal cycle ergometer test and scaled for body mass (BM) and lean mass (LM) using ratio and allometric methods. A continuous cardiometabolic risk score was calculated from age- and sex-specific z -scores of traditional risk factors, with "increased risk" defined as ≥1 SD above the mean. Receiver operating characteristic curves assessed the ability of V̇O 2peak to classify children at increased risk. Associations between V̇O 2peak and cardiometabolic risk factors were measured using linear regression analyses. The type and the extent of misclassification were calculated by comparing rank differences between allometric and ratio-scaled V̇O 2peak , using directly measured cardiometabolic risk versus V̇O 2peak cut points. Population-specific cut points based on previously reported cut points in this sample were compared with universal cut points from existing meta-analyses.
Results:
Scaling using LM, or allometric methods, attenuated associations between V̇O 2peak and cardiometabolic risk factors. V̇O 2peak scaled by LM -1 , BM -0.49 , or LM -1.04 demonstrated poor ability to classify increased cardiometabolic risk, whereas V̇O 2peak scaled by BM -1 had the highest classification ability in girls and boys (AUC = 0.875 and 0.690, respectively, P < 0.01). Universal cut points produced fewer false-positive classifications than population-specific cut points.
Conclusions:
V̇O 2peak appropriately scaled for body size and composition may have limited ability to distinguish cardiometabolic risk in children, with diminished associations with cardiometabolic risk factors. Screening for cardiometabolic risk in children using V̇O 2peak ratio scaled by BM may reflect body size rather than fitness.


Related Concept Videos
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:29
Oxygen Requirements and Growth Patterns
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:24
Factors Affecting Respiration
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is...
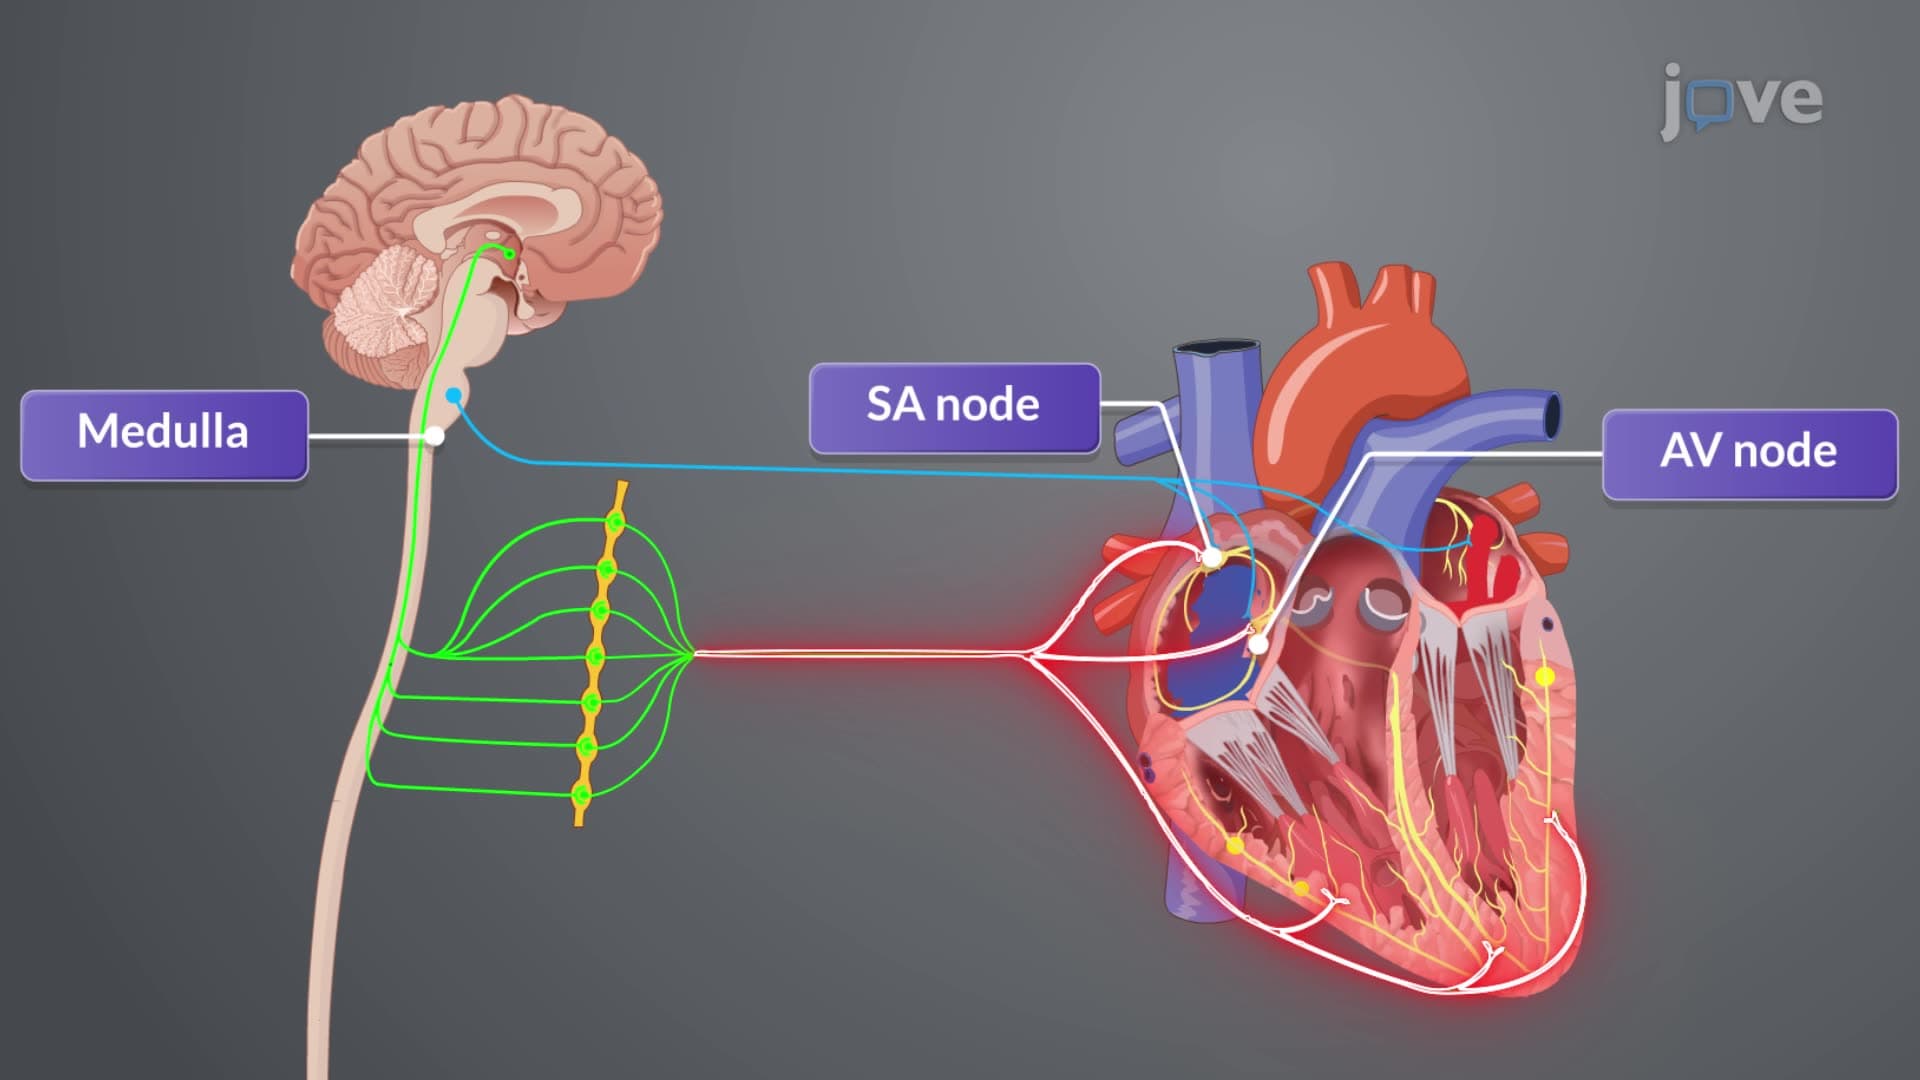 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...