Related Experiment Video
Updated: Jun 25, 2026
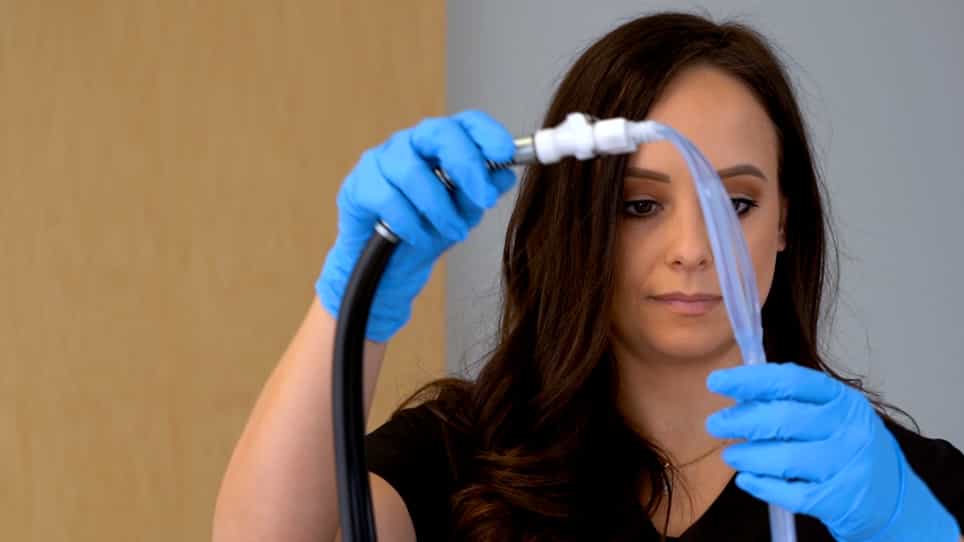

Cooling or Warming the Esophagus to Reduce Esophageal Injury During Left Atrial Ablation in the Treatment of Atrial Fibrillation
Published on: March 15, 2020
Safety of Same-Day Discharge Following Pulsed-Field Ablation Versus Radiofrequency Ablation: A Comparative Analysis
Adele Watfa1, Arwa Younis1, Mohamad Mdaihly1
1Cardiac Electrophysiology and Pacing Section, Department of Cardiovascular Medicine, Cleveland Clinic, Cleveland, Ohio, USA.

Background:
Same-day discharge (SDD) after catheter ablation is increasingly adopted to improve patient convenience and reduce healthcare costs. While SDD following radiofrequency ablation (RFA) is well-documented, no data exist on SDD in patients undergoing pulsed-field ablation (PFA) for atrial fibrillation (AF).
Objective:
To evaluate the safety of SDD in patients undergoing PFA and RFA for AF, with an exploratory comparison of practice patterns and outcomes.
Methods:
From a prospectively maintained registry, we included all consecutive patients undergoing PFA for AF (FARAWAVE catheter) since its FDA approval and patients undergoing AF RFA between March and October 2023 (comparison group). Outcomes included rates of major complications (vascular complications, cerebrovascular accidents, transient ischemic attacks (TIA), phrenic nerve injury, and pericardial effusion requiring intervention), minor complications, readmissions within 30 days, and all-cause mortality.
Results:
The study included 955 PFA patients, of whom 207 (21.7%) were discharged the same day, and 1072 RFA patients, of whom 127 (11.8%) were discharged the same day. Vascular closure modalities differed significantly across groups (p < 0.001). Major complications, including stroke and TIA, occurred in 0.5% of PFA non-SDD and 1.1% of RFA non-SDD patients (p = 0.29, p = 0.24), with no major complications in SDD groups and no deaths across all groups. Minor complications were 0.5% for PFA SDD versus 1.1% for PFA non-SDD (p = 0.44) and 1.6% for both RFA SDD and RFA non-SDD (p = 0.99), and not significantly different between PFA SDD and RFA SDD (p = 0.31). Readmission rates (UTI, AF, aspiration pneumonia) were similar between SDD patients at 1.4% for PFA and 2.4% for RFA (p = 0.54). A lower CHA2DS2-VASc score predicted the practice pattern of SDD in the PFA cohort (OR = 0.754, 95% CI: 0.663-0.858, p < 0.001), while being octogenarian reduced the likelihood of SDD (OR = 0.265, 95% CI: 0.105-0.666, p = 0.005).
Conclusion:
In this cohort, SDD was found to be a safe and viable option for both PFA and RFA. In this practice, the rates of same-day discharge were higher in the PFA group versus the RFA group and is being increasingly adopted.
More Related Videos
 04:58
Reduced Procedure Time and Variability with Active Esophageal Cooling During Radiofrequency Ablation for Atrial Fibrillation
Published on: August 25, 2022
 05:43
Author Spotlight: Improving Lesion Contiguity in Pulmonary Vein Isolation via Proactive Esophageal Cooling
Published on: April 19, 2024
