Related Experiment Video
Updated: Sep 12, 2025
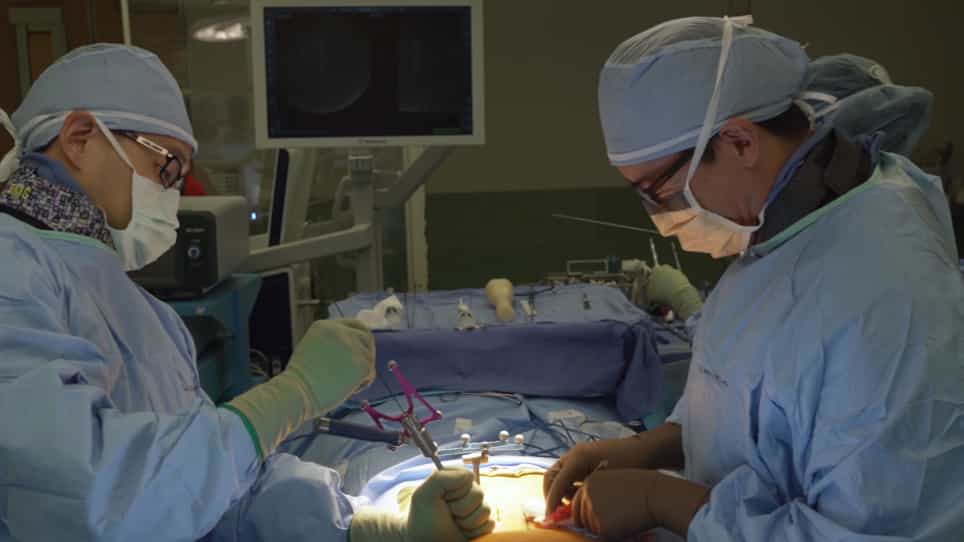

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Can intraoperative impedance planimetry (EndoFLIP™) during anti-reflux surgery replace preoperative manometry with no
Jean-Christophe N Rwigema1,2, Derrius Anderson3, Sullivan A Ayuso3
1Division of Gastrointestinal and General Surgery, Department of Surgery, Endeavor Health, Evanston, IL, USA. jchrisrwigema@gmail.com.

Introduction:
The advent of functional lumen imaging probe (FLIP) and panometry provides an additional means of evaluating esophageal motility in addition to conventional manometry. Beginning in 2022, our group began preferentially utilizing intraoperative panometry for anti-reflux operations to improve patient comfort and efficiency of access. This study aims to explore the changes in peri-operative and postoperative outcomes since implementing intraoperative FLIP panometry to evaluate esophageal motility.
Objective:
The purpose of this project is to determine the changes in perioperative and postoperative outcomes since the implementation of intraoperative impedance panometry in place of preoperative manometry prior to patients undergoing anti-reflux procedures.
Methods:
A retrospective review of a prospectively maintained gastroesophageal database was performed. Outcomes were analyzed of those patients from 2019 to 2024 undergoing Nissen fundoplication, Toupet fundoplication, magnetic sphincter augmentation, and anti-reflux mucosectomy. Our intraoperative panometry protocol was instituted in January of 2022. The groups were analyzed and compared using chi-square and Wilcoxon rank-sum tests.
Results:
Between 2019 and 2024, 565 patients underwent anti-reflux interventions. Median follow-up after implementation of intraoperative panometry was three months, compared to 23 months in the manometry group. In the manometry group, 71.6% of patients had normal esophageal motility compared to 93.2% of patients in the panometry group (p < 0.0001). At 3 weeks, the panometry group had worse GERD-HRQL (p = 0.03) and worse gas bloat (p < 0.004) compared to the manometry group. At 6 months, 1 and 2 years, there were no differences in RSI, GERD-HRQL, gas bloat or dysphagia scores between the groups.
Conclusions:
It is reasonable to forego preoperative manometry in favor of intraoperative FLIP panometry for anti-reflux procedures. There is no difference in patient quality of life outcomes at 6 months and 1 year post-operatively.


Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to: