Related Experiment Video
Updated: Sep 8, 2025
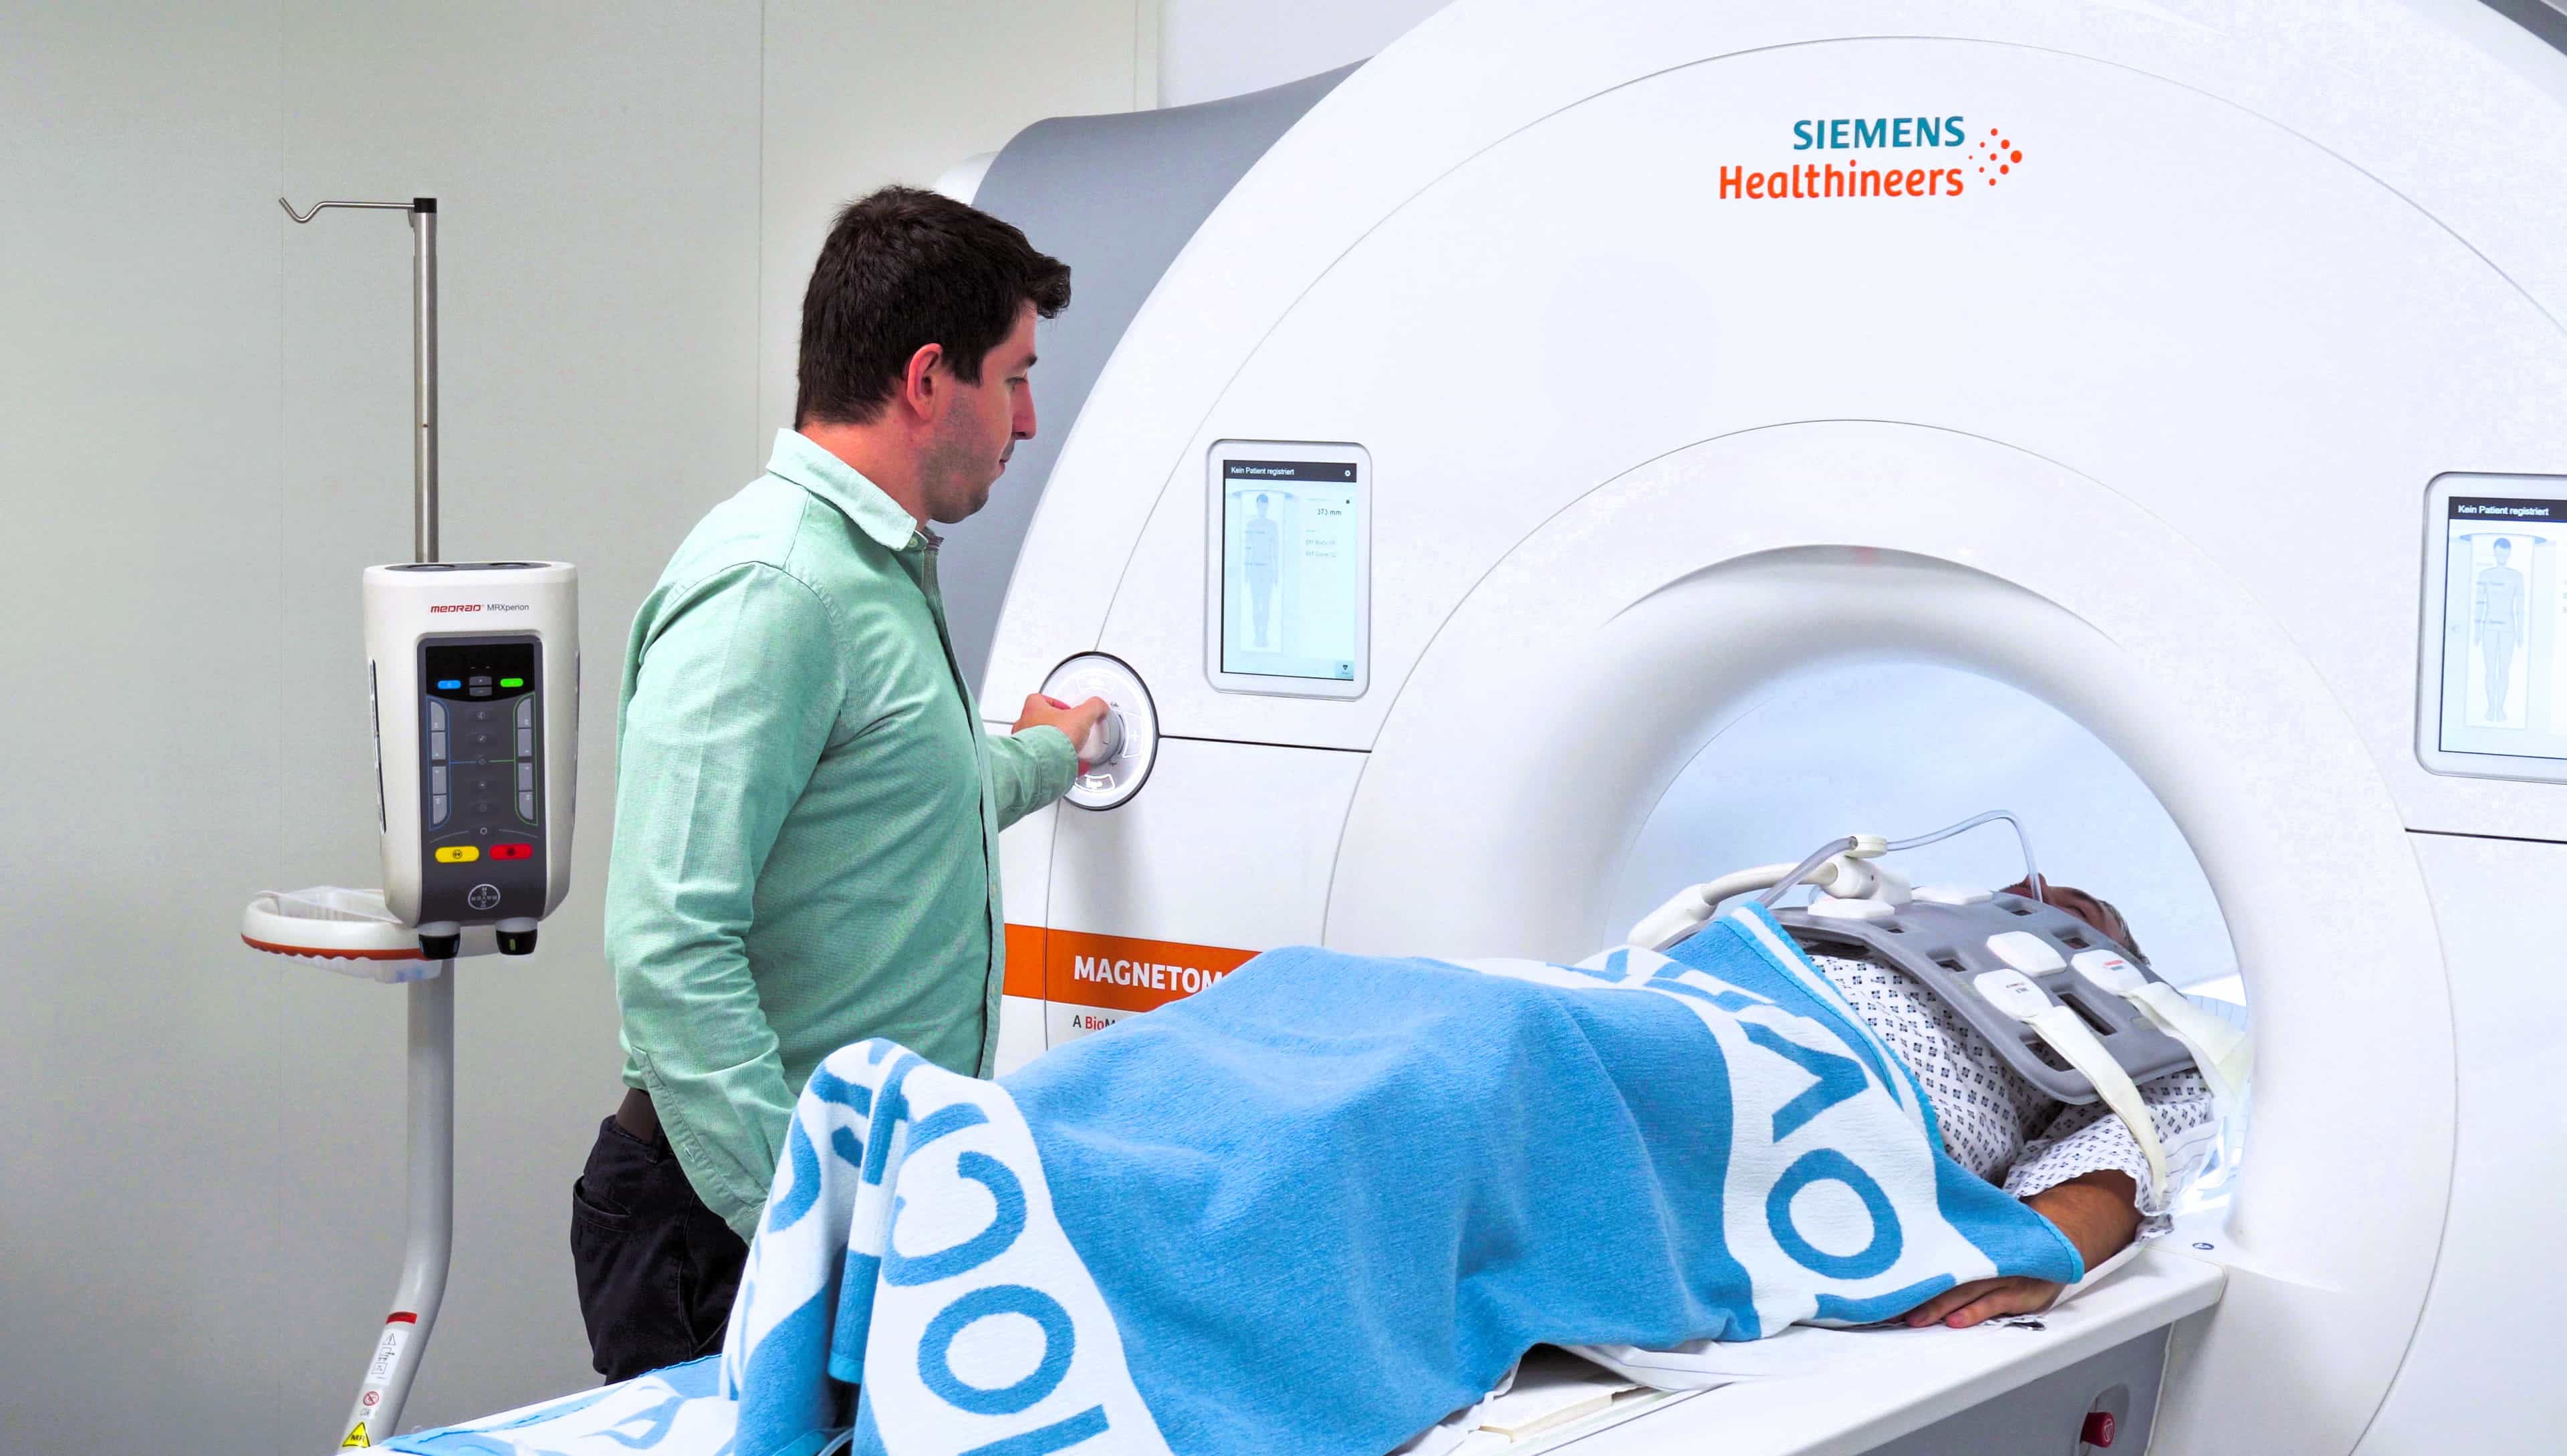

Three-Dimensional Phase Resolved Functional Lung Magnetic Resonance Imaging
Published on: June 21, 2024
Ventilation defect burden predicts lung cancer resection outcomes
Nisarg Radadia1, Eldar Priel2,3, Yonni Friedlander4
1Department of Medicine, Division of Respirology, McMaster University, Hamilton, ON, Canada.

Background:
Abnormal ventilation prior to lung cancer resection has not been investigated using modern ventilation imaging modalities and may better predict postoperative outcomes than guideline-recommended lung function tests. Our objective was to quantify the burden of ventilation defects observed using Technegas single-photon emission computed tomography (SPECT) and 129Xe magnetic resonance imaging (MRI) before lung cancer resection, and to evaluate their association with postoperative pulmonary complications and length of hospital stay.
Methods:
This was a prospective, 6-week, observational study of adults undergoing lung cancer resection at a single centre. Before lung resection, participants underwent Technegas-SPECT, 129Xe-MRI, spirometry and measurement of diffusing capacity of the lung for carbon monoxide. Preoperative ventilation defect burden was quantified by the Technegas-SPECT and 129Xe-MRI ventilation defect percent (VDP). Predictors of complications during the 4-week postoperative period and length of hospital stay were evaluated by logistic and linear regression.
Results:
Abnormal ventilation was observed preoperatively by Technegas-SPECT and 129Xe-MRI for 58% (60 of 103) and 73% (74 of 102) of participants, respectively. Preoperative VDPs were higher for participants with postoperative complications compared with those without (SPECT: p=0.01; MRI: p=0.0006) and correlated with length of hospital stay (SPECT: r=0.44, p<0.0001; MRI: r=0.51, p<0.0001). Multivariable models revealed preoperative VDP to be the strongest predictor of postoperative complications (SPECT: OR 1.06, 95% CI 1.01-1.11, p=0.02; MRI: OR 1.11, 95% CI 1.02-1.21, p=0.02) and length of hospital stay (SPECT: β=0.16, p<0.001; MRI: β=0.23, p<0.001).
Conclusion:
Abnormal ventilation is prevalent prior to lung cancer resection and may be a stronger predictor of postoperative complications and length of hospital stay than standard clinical lung function measures.
More Related Videos


Related Concept Videos
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:30
Radiological Investigation II: MRI and Ventilation Perfusion Scan
Magnetic Resonance Imaging (MRI) and Ventilation Perfusion Scans are two radiological investigations that offer detailed diagnostic images of the body, particularly lung structures.
MRI
MRI uses magnetic fields and radiofrequency signals to distinguish between normal and abnormal tissues. This technology provides a more detailed diagnostic image than CT scans, enabling it to characterize pulmonary nodules, stage bronchogenic carcinoma, and evaluate inflammatory activity in...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:15
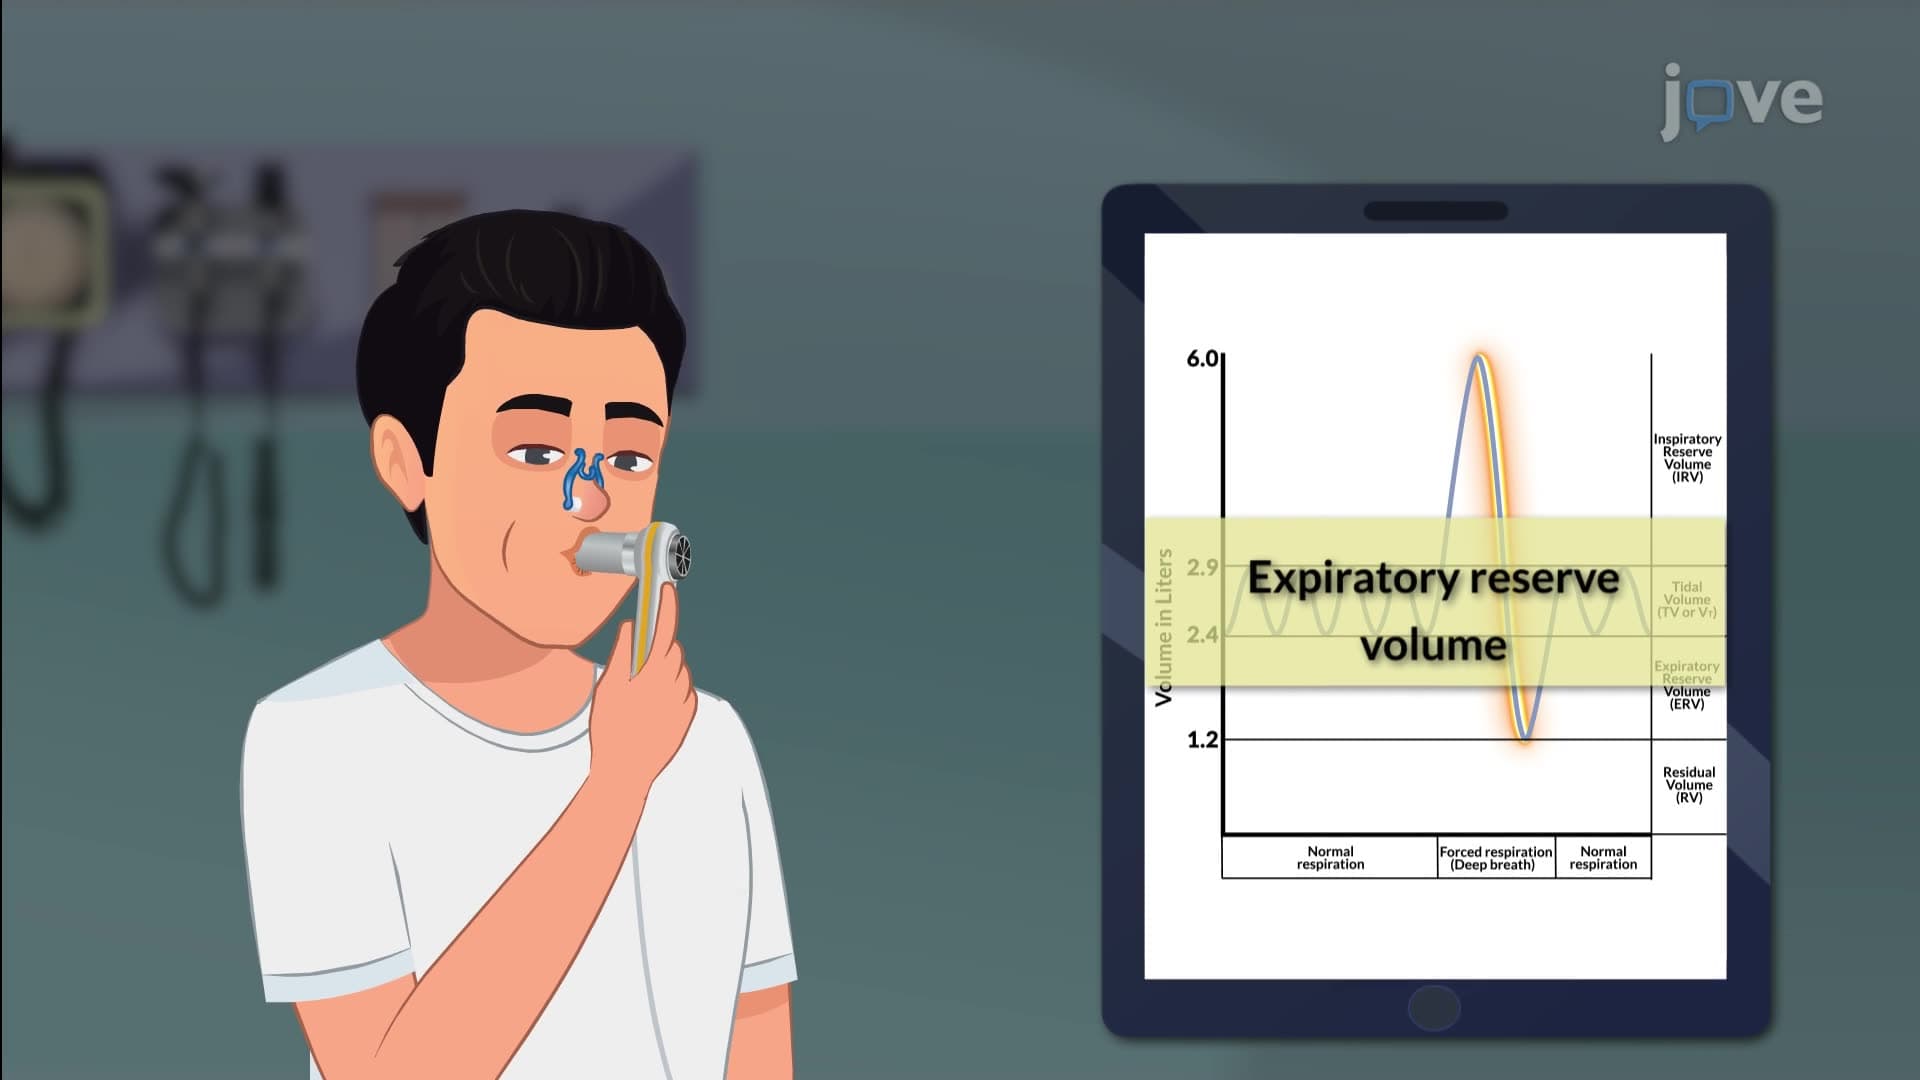
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: