Related Experiment Video
Updated: May 2, 2026
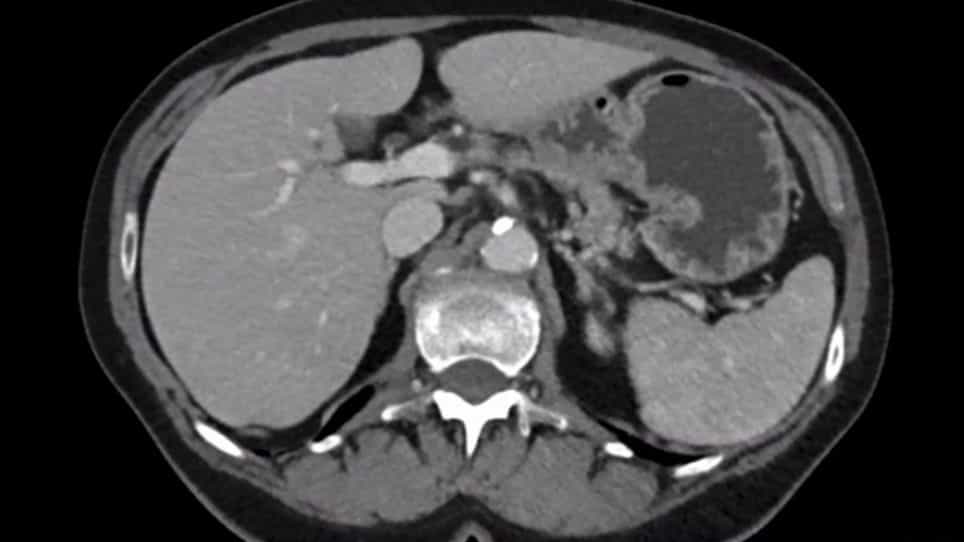

Laparoscopic Radical Left Pancreatectomy for Pancreatic Cancer: Surgical Strategy and Technique Video
Published on: June 6, 2020
A standardized surgical approach to multifocal locoregionally recurrent left-sided adrenocortical carcinoma
Shruthi R Perati1, Alyssa V Eade1, Aaron Dinerman1
1Surgical Oncology Program, Center for Cancer Research, National Cancer Institute, National Institutes of Health, Bethesda, MD, USA.

Introduction:
Society guidelines recommend surgery for recurrent adrenocortical carcinoma (ACC) in selected patients; however, no standards exist to guide surgeons, and this may be particularly problematic in the management of multifocal locoregional recurrence.
Materials And Methods:
A standardized approach was developed for patients with multifocal locoregionally recurrent left-sided ACC as part of an NCI study (NCT05237934). En bloc resection included the distal pancreas, spleen, left kidney, portion of left diaphragm, and possibly a portion of the left lateral liver, greater curve of the stomach, and/or descending colon. Morbidity, survival, and quality of life (QoL) were assessed.
Results:
From 2018 to 2024, ten patients (median age 59 years) underwent multi-visceral en bloc resections for multifocal locoregionally recurrent left-sided ACC. Prior to surgery, 90 % of patients had undergone systemic therapy and a median of one prior operation (range 1-4). Size of local recurrence(s) averaged 6.5 cm (range 1.9-12.2 cm) at largest diameter, with a median of 3 (range 2-8) foci of disease identifiable on pre-operative imaging. Two patients (20 %) developed a Grade 1B post-operative pancreatic fistula. There were no peri-operative mortalities. Median locoregional recurrence-free survival was 22.1 months at 19.3 months of median follow-up. 50 % of QoL survey respondents reported feeling recovered/back to baseline activity level within 4 months of surgery.
Conclusion:
Locoregional control can be obtained with reasonable success and acceptable morbidity in select patients with multifocal locoregionally recurrent left-sided ACC using a standardized left upper quadrant en bloc multi-visceral resection approach. Verification of the results of this technique is required in other experienced centers.