Comparative study of open and robot-assisted approaches to ureteropelvic junction obstruction in children ≤ 12 months: A multi-institutional retrospective analysis
Related Experiment Video
Updated: Sep 10, 2025

An Immature Murine Model of Reversible Unilateral Ureteral Obstruction
Published on: April 4, 2025
Suhaib Abdulfattah1, Aznive Aghababian1, Sahar Eftekharzadeh2
1Division of Urology, Children's Hospital of Philadelphia, Philadelphia, PA, USA.

Background:
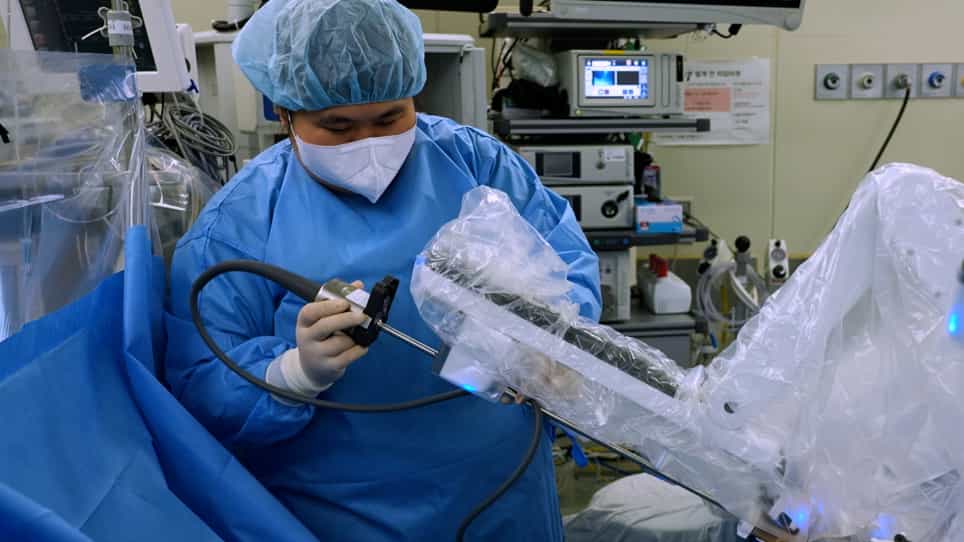
The utilization of robot-assisted laparoscopic pyeloplasty (RALP) for the surgical correction of ureteropelvic junction obstruction (UPJO) continues to increase. The aim of this study was to determine whether robot-assisted laparoscopic pyeloplasty (RALP) is a safe and equally efficacious procedure compared to open pyeloplasty (OP) in infants ≤12 months old.
Methods:
All patients ≤12 months old who underwent RALP or OP between January 2012 and January 2021 at five participating centers were included in this study. Patients who had pure laparoscopic approach, redo-pyeloplasty, ureterocalicostomy, abnormal nephro-ureteral anomalies, or lacked reviewable surgical records were excluded. Success was defined as lack of advanced endoscopic or re-do reconstructive intervention.
Results:
448 out of 497 patients met inclusion criteria: 151 RALP (34 %) and 297 OP (66 %). The median age at surgery was similar for both cohorts (p = 0.29). RALP compared to OP was associated with a higher usage of ureteral stent placement (100 % vs 88.9 %; p < 0.001) and longer procedure time (175 vs 160 min; p = 0.01), less administration of hospital morphine-equivalents post-operatively (p < 0.001) and similar length of stay (p = 0.96). There was no difference in the incidence of 30-day complications between the two groups, however higher-grade complications were seen in the OP group. Over a median follow of 26 months, the success rate after RALP and OP was 98.7 % and 89.6 % respectively (p < 0.001).
Conclusion:
In this large, multi-institutional comparative series of infant pyeloplasty, our results demonstrate that RALP is not only safe and feasible, but also confers the advantages of reduced opioid usage, decreased risk of high-grade complications and decreased need for additional interventions during follow-up.
Related Concept Videos
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:28
Imaging Studies I: Kidney, Ureter, and Bladder Studies
 01:25
Urinary Tract Calculi VI: Surgical Management