Related Experiment Video For adenocarcinoma lung
Updated: Jan 18, 2026
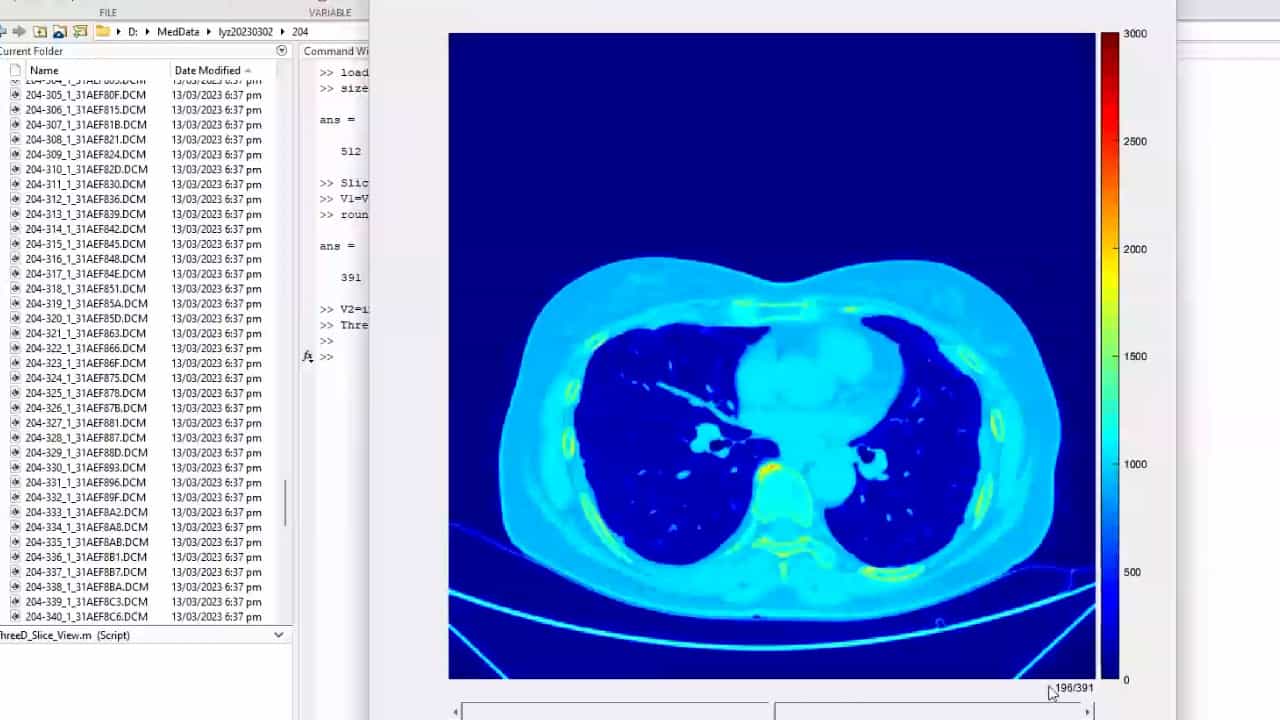

Author Spotlight: Advancing 3D Modeling for Enhanced Diagnosis and Treatment of Pulmonary Nodules in Early-Stage Lung Cancer
Published on: October 13, 2023
From Hypersensitivity Pneumonitis to Lung Adenocarcinoma: A Case Report Illustrating Diagnostic Complexity
Umesh Kumar Pabani1, Subirna Visvalingam2, Katie Jones3
1Internal Medicine, Queen's Hospital, London, GBR.

Abstract:
Adenocarcinoma of the lung is the most common type of lung cancer and is classified as one of the non-small cell lung cancers. It typically arises in the peripheral regions of the lungs, affecting the dense glandular tissues. Most patients diagnosed with pulmonary adenocarcinoma are current or former smokers and present with nonspecific respiratory symptoms such as a persistent cough and shortness of breath. Many also go on to develop B symptoms, including weight loss and night sweats. We present a case of an 84-year-old Caucasian woman, a lifelong nonsmoker and teetotaller, who presented with a two-week history of dry cough, shortness of breath, and chest heaviness following receipt of her influenza vaccination. Her past medical history included hypertension (treated with amlodipine and perindopril), glaucoma, and bilateral cataracts. Initial blood tests showed normal infection and inflammatory markers. However, her chest X-ray was suggestive of pulmonary fibrosis, with fibrotic changes predominantly in the bilateral lower lung zones. She was initially treated with a tapering course of prednisolone for suspected hypersensitivity pneumonitis. Lung function tests were arranged, and a computed tomography chest scan revealed tiny centrilobular nodules in both lungs, located in peribronchovascular, perifissural, and subpleural areas. Further history revealed regular exposure to a Western Rosella bird. She denied dampness, mold, or known asbestos exposure at home. Connective tissue disease screening and avian precipitins, however, were negative. She later presented again with worsening symptoms. Arterial blood gas analysis revealed type 1 respiratory failure. The patient was admitted to the intensive care unit and was intubated and ventilated. A repeat chest X-ray showed progressive parenchymal changes without regression. Intravenous 500 mg of methylprednisolone was started; however, she showed no improvement with it. The patient's case was discussed at the lung multidisciplinary team meeting, and a lung biopsy was recommended, which was carried out via bronchoscopy. Histopathology revealed fragmented cores of adenocarcinoma with lepidic and papillary growth patterns, mucinous type, consistent with a primary lung origin (T4N0M1a). The patient's condition continued to deteriorate despite intensive care support, and she sadly passed away two weeks after admission. This case underscores the need to maintain a broad differential diagnosis, particularly in patients who fail to improve with treatment. It also emphasizes the role of biopsy in resolving the diagnostic challenge, as imaging studies did not provide a clear diagnosis.
More Related Videos
 10:21
Author Spotlight: Exploring the Role of Inflammation in the Co-occurrence of Primary Sjogren's Syndrome and Lung Adenocarcinoma
Published on: September 20, 2024
 07:59
Author Spotlight: Advancements in Molecular Biomarker Testing for Non-Squamous Non-Small Cell Lung Cancer
Published on: September 8, 2023
