Related Experiment Video
Updated: Jan 18, 2026
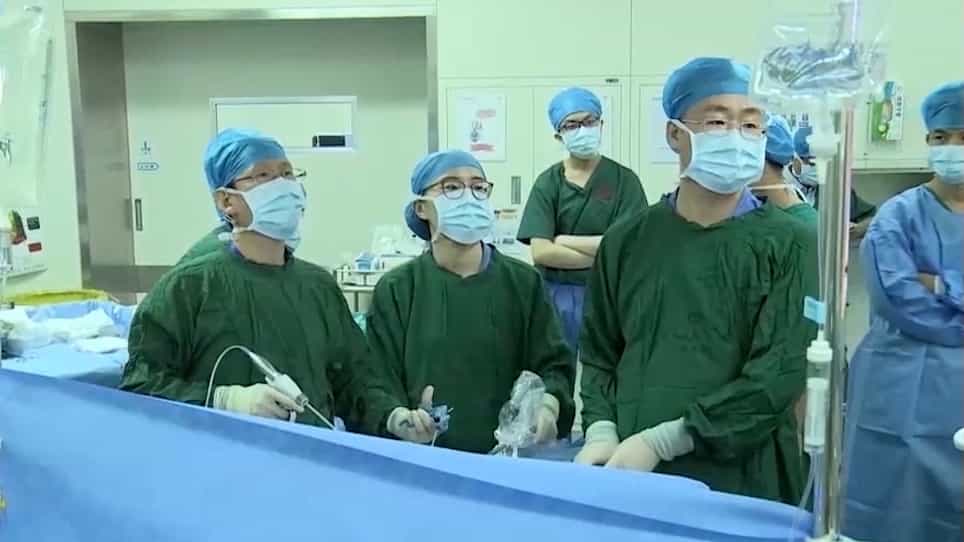
Laparoscopy-endoscopy Cooperative Surgery for the Treatment of Gastric Gastrointestinal Stromal Tumors
Published on: February 19, 2022
Solitary Fibrous Tumor of the Stomach: Diagnostic Pitfalls and Clinical Implications
Tadakazu Ao1, Eiji Shinto1, Tenma Ichisawa1
1Department of Surgery, Self-Defense Forces Central Hospital, Tokyo, Japan.

Introduction:
Solitary fibrous tumor (SFT) is a rare mesenchymal neoplasm that most commonly originates in the pleura but can also occur at extrapleural sites, including the abdominal cavity. Among these, primary SFT of the stomach is exceptionally rare. Due to overlapping clinical, endoscopic, and radiologic characteristics, distinguishing SFT from gastrointestinal stromal tumor (GIST) can be particularly challenging. Misdiagnosis may result in inappropriate treatment, such as unnecessary administration of imatinib. Therefore, accurate preoperative differentiation is essential for appropriate management.
Case Presentation:
A 74-year-old man was incidentally found to have a submucosal gastric tumor during a routine health checkup and was referred to our hospital for further evaluation and treatment. Upper gastrointestinal endoscopy revealed a 30-mm subepithelial lesion on the greater curvature of the gastric fundus. Endoscopic ultrasound-guided fine-needle aspiration (EUS-FNA) demonstrated isolated and clustered cells with ovoid to spindle-shaped nuclei. Although not definitive, the combined endoscopic and cytological findings led to a preoperative diagnosis of suspected GIST, and laparoscopy and endoscopy cooperative surgery (LECS) was subsequently performed for local resection. Histopathological examination of the resected specimen revealed an irregular proliferation of spindle cells and nuclear immunopositivity for signal transducer and activator of transcription 6 (STAT6), leading to a final diagnosis of SFT of the stomach. According to Demicco's risk stratification model, the tumor was classified as low risk. The patient underwent complete resection via LECS and has remained free of recurrence for more than 2.5 years postoperatively.
Conclusions:
This case highlights the difficulty in differentiating SFT from GIST preoperatively and underscores the importance of obtaining sufficient tissue samples to allow for immunohistochemical analysis, particularly STAT6 staining. Recognizing gastric SFT as part of the differential diagnosis is critical to avoid misdiagnosis and ensure appropriate therapeutic decision-making.
Related Concept Videos
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:30
Serum Laboratory Studies, Stool Test, Breath Test