Related Experiment Video
Updated: Jan 6, 2026
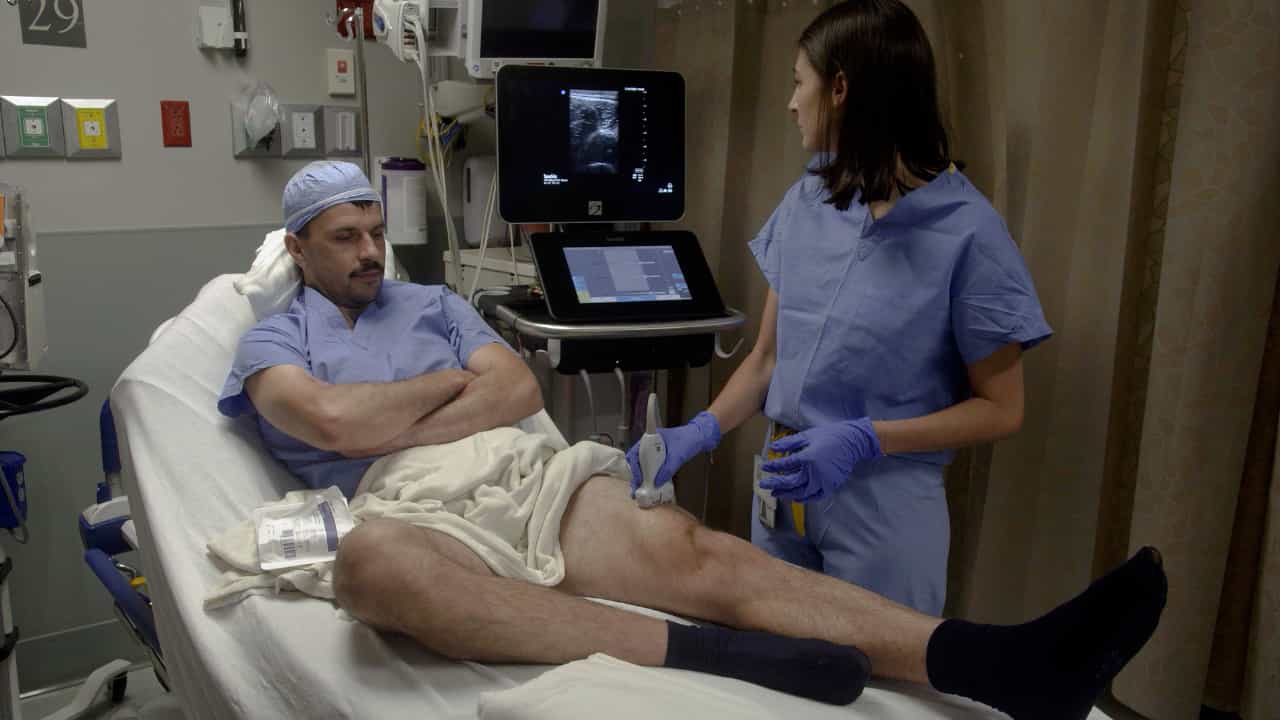

Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
The dynamic nature of frailty in metastatic spine disease patients
Oludotun Ogunsola1, Edward S Harake2, Sean Smith3
1Department of Neurosurgery, University of Michigan, Ann Arbor, MI, USA.

Purpose:
Frailty measures are critical for predicting outcomes in metastatic spine disease (MSD) patients. This study aimed to evaluate frailty measures throughout the disease process.
Methods:
This retrospective analysis measured frailty in MSD patients at multiple time points using a modified Metastatic Spinal Tumor Frailty Index (MSTFI). Scores were 0: "not frail," 1: "mild", 2: "moderate, and ≥ 3: "severe." Measurements were taken at cancer diagnosis, spine metastasis (SM) diagnosis, and 4-month intervals up to 2-years. The change in frailty distribution was described at the general cohort and patient levels. Two-year survival was assessed from baseline frailty status at SM diagnosis.
Results:
This study included 465 patients with an average age of 62.3 years (± 12.7), 33.8% female. Prostate cancer was most common (20.9%), followed by renal cell carcinoma (15.3%), non-small cell lung cancer (NSCLC, 13.5%), and others. Frailty changed dynamically, most significantly early in the disease. Initially, 79.4% were not frail; this dropped to 60.1% at SM diagnosis and to 42.7% at 4 months. Patients with short-term (4 month) data showed rapid frailty progression, with 57% becoming moderately to severely frail (p = 0.01), whereas 45% with long-term (24 months) data remained non-frail (p < 0.0001). Contributing factors included anemia (32.7%), electrolyte abnormalities (16.9%), and malnutrition (11.4%). Histological classification influenced frailty. Higher frailty scores at metastatic diagnosis correlated with worse 2-year survival outcomes (p: <0.001-0.04), underscoring frailty's prognostic significance.
Conclusion:
Frailty is dynamic, with a potential early intervention point to maintain or reverse it. Further research is needed to assess which frailty measures are most dynamic and amenable to intervention.


Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:21
Fatigue
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age