Related Experiment Video
Updated: Jan 17, 2026

Treatment of Ankle Osteoarthritis with Total Ankle Replacement Through a Lateral Transfibular Approach
Published on: January 24, 2018
[Modified medial wedge osteotomy for correction of double varus deformity and increased tibial slope]
Wolf Petersen1, Yizhou Ge2, Amelie Klaumünzer2
1Klinik für Orthopädie und Unfallchirurgie, Martin-Luther-Krankenhaus Berlin, Caspar Theyss Str. 27-33, 14193, Berlin, Deutschland. wolf.petersen@jsd.de.

Objective:
Correction of a double varus deformity and an increased tibial slope.
Indications:
Medial osteoarthritis (OA) and anterior instability in combination with a double varus deformity (MPTA < 84°, JLCA > 2°) and an increased tibial slope (> 12°).
Contraindications:
Femoral varus deformity with lateral distal femoral angle of > 91°, severe lateral cartilage damage, lateral OA, lateral loss of the meniscus.
Surgical Technique:
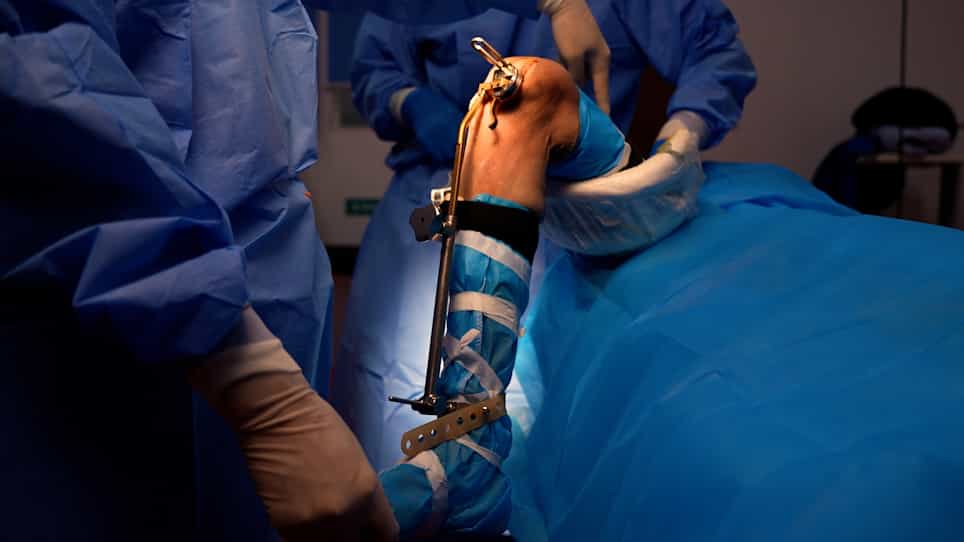
Skin incision medial to the tibial tuberosity of approximately 8-10 cm. Insertion of two converging guide wires directly above the pes anserinus, ascending obliquely above the fibula tip. Check the position of the wires with the image intensifier. Incomplete osteotomy below the guide wires with the oscillating saw. Complete osteotomy of the posterior tibial cortex with a chisel to move the hinge anterolateral. Insertion of two Schanz screws in the proximal and distal fragments from anterior. Ascending osteotomy and removal of a small anterior wedge. Careful opening of the osteotomy with chisels at the level of the posterior tibial cortex. Correction of the tibial reclination with the help of the Schanz screws ("joystick"). Check the correction with the image intensifier in two planes. Osteosynthesis with medial angle-stable plate.
Postoperative Management:
Partial weight bearing with 10 kg for 2-6 weeks, then gradually increase the load. Range of motion: free.
Results:
Using the described surgical technique, 28 patients (7 women, 21 men, age: 36.8 years) with chronic anterior instability or recurrent instability were treated. All patients had a double varus deformity (MPTA < 84°, JLCA > 2°) and a posterior tibial reclination of > 12°. The mean postoperative tibial reclination was 9.1°. The postoperative hip-knee-ankle angle was -0.4°. The Lysholm score increased from an average of 75.2 points to 90.3 points.