Related Experiment Video
Updated: Jan 17, 2026


Mouse Model of Metabolic Dysfunction-Associated Steatotic Liver Disease with Fibrosis
Published on: July 18, 2025
Differential Effects of Cardiometabolic Risk Factors on All-Cause Mortality in United States Adults With Metabolic
Matthew Dukewich1, Jennifer L Dodge2, Liyun Yuan1
1Division of Gastrointestinal and Liver Diseases, University of Southern California Keck School of Medicine, Los Angeles, California.

Background & Aims:
Metabolic dysfunction-associated steatotic liver disease (MASLD) is defined by abnormalities in cardiometabolic risk factors (CMRFs). Characterizing the contribution of individual CMRFs to clinical outcomes may guide prioritization of interventions. We evaluated the association of individual CMRFs with all-cause mortality in United States adults with MASLD.
Methods:
Participants in the National Health and Nutrition Examination Survey (NHANES) III (1988-1994) and continuous NHANES (1999-2018) were linked to mortality data through 2019. Adults >20 years of age were included if their Fatty Liver Index (FLI) was >60 and they had at least one CMRF (overweight/obesity, glucose intolerance, high blood pressure, triglycerides, or low high-density lipoprotein [HDL]). Cox regression analyzed risk of all-cause mortality adjusted for age, sex, and Fibrosis-4 (FIB-4).
Results:
Among 21,872 participants included (mean age, 50 years; 53% male), the mean body mass index (BMI) was 33.6 kg/m2 with a median of 3 CMRF (99.5% overweight/obese, 55% glucose intolerance, 58% high blood pressure, 67% high triglycerides, 40% low HDL). In adjusted analysis of individual CMRF, high blood pressure (adjusted hazard ratio [aHR], 1.39; 95% confidence interval [CI], 1.24-1.55; P < .001), glucose intolerance (aHR, 1.26; 95% CI, 1.16-1.38; P < .01), and low HDL (aHR, 1.15; 95% CI, 1.05-1.26; P = .003) exerted significant risks for mortality. When stratifying the overweight/obesity CMRF by discrete BMI ranges, a significantly greater risk for mortality was seen with BMI 35 to 40 kg/m2 (aHR, 1.18; 95% CI, 1.02-1.36; P = .03), BMI 40 to 45 kg/m2 (aHR, 1.55; 95% CI, 1.24-1.94; P < .001), and BMI >45 kg/m2 (aHR, 1.64; 95% CI, 1.27-2.14; P < .001) compared with those with a BMI 25 to 30 kg/m2. In age-adjusted analysis, the number of CMRFs was associated with greater risk for mortality (aHR, 1.15 per additional CMRF; 95% CI, 1.10-1.20; P < .001) CONCLUSIONS: The differential risk for mortality between individual CMRFs supports distinct clinical profiles in MASLD. This study found that high blood pressure and glucose intolerance exerted the greatest risk for all-cause mortality in those with MASLD, suggesting a role for prioritization of CMRF optimization.
Related Concept Videos
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:24
Overview of Lipid Metabolism
Lipolysis: The Breakdown of Lipids:
Lipolysis is the process of breaking down lipids, particularly triglycerides, into glycerol and fatty acids. This process typically occurs in the adipose tissue and is triggered by various hormones, including glucagon and...
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:14
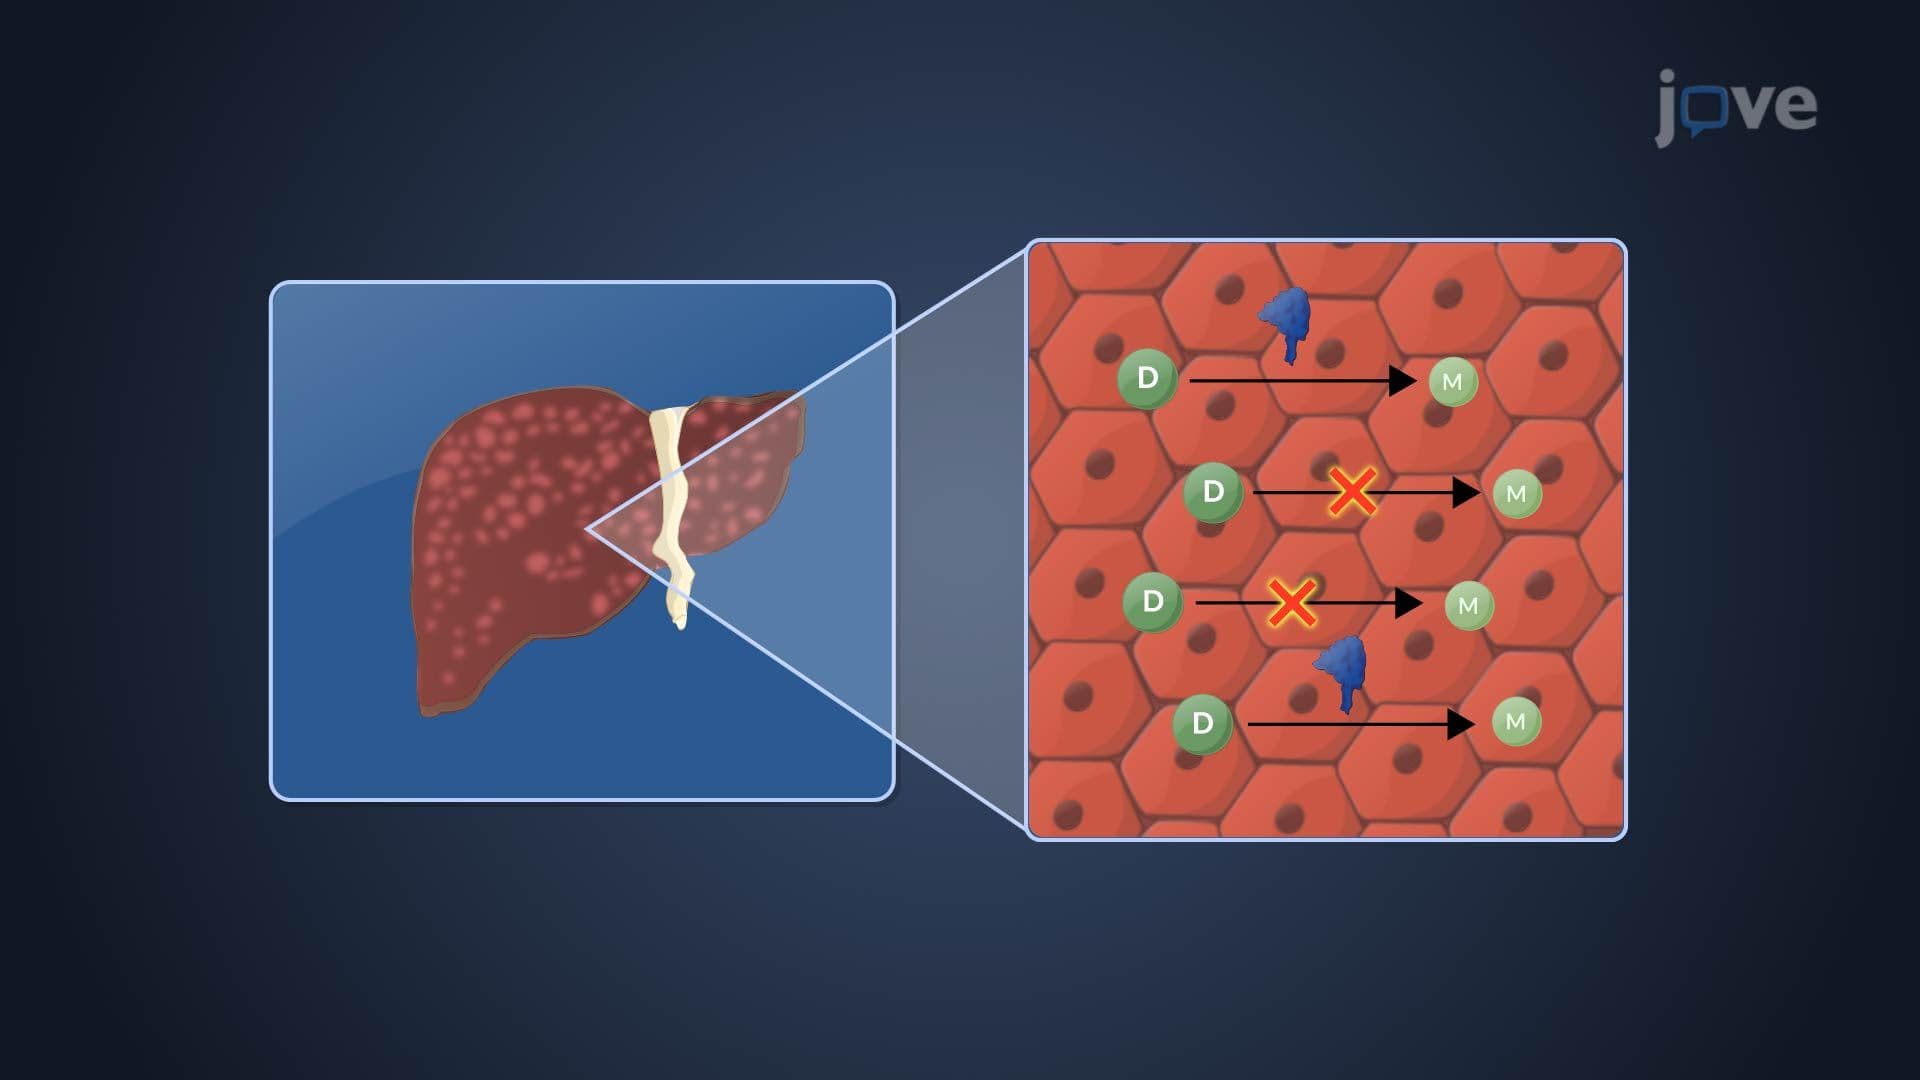
Effect of Hepatic Disease on Pharmacokinetics: Active Drug, Metabolite and Fraction of Metabolized Drug
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion