The Effects of Chronic Opioid Therapy on Achalasia and the Upper Esophageal Sphincter
Related Experiment Video
Updated: Jan 17, 2026

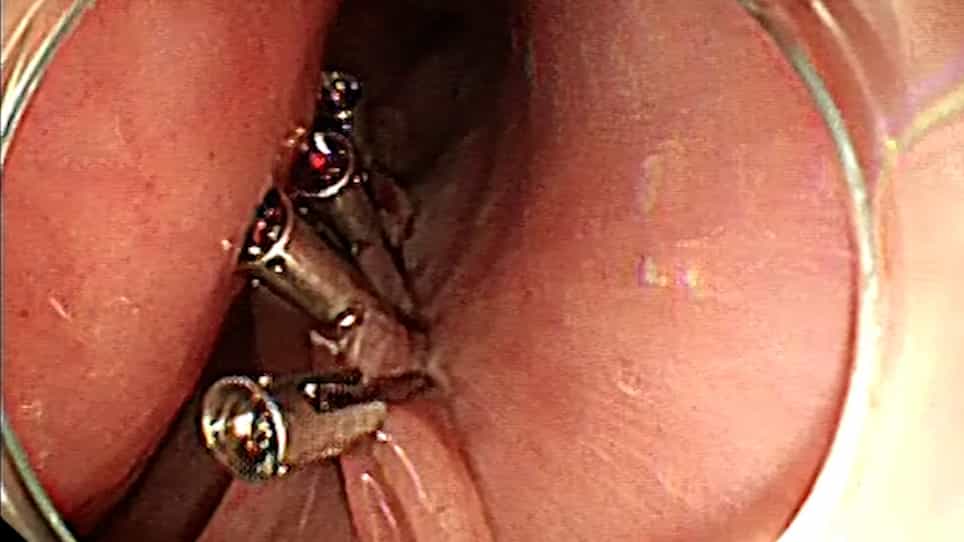
Robotic Myotomy and Partial Fundoplication for Achalasia
Published on: August 11, 2023
Joshua Kalapala1,2, Promila Banerjee1,2, Emma Schnittka3
1Loyola Stritch School of Medicine, MercyOne Hospital, North Iowa 2160 S 1st Ave, Maywood, IL 60153, USA.

Abstract:
Background: The rise of opioid drug usage in the U.S. correlates with increasing recognition of gastrointestinal side effects, especially in the esophagus. The literature has recently noted that abnormalities in the upper esophageal sphincter (UES) are a poor prognostic factor in Achalasia treatment response. A better understanding of the relationship between opioid therapy and esophageal motility and sphincter function may shape our management guidelines for esophageal dysmotilities. This study aimed to evaluate dysmotility patterns, specifically UES function, among the veteran population, where opioid use is reportedly high. Methods: We performed a retrospective search of all the veterans at a large urban veteran affairs hospital who had undergone esophageal manometry from 2013 to 2022, collecting data on patient demographics, indication for procedure, diagnosis, sphincter pressure values, and presence of chronic opioid use. Results: Of 395 patients, 29% had a history of chronic opioid therapy. Notably, patients that were diagnosed with Achalasia had a greater proportion of chronic opioid use as compared to those who were not. Additionally, there was a statistically significant lower average upper esophageal resting pressure in opioid patients compared to non-opioid patients. Conclusions: Veteran patients with Achalasia have a greater proportion of chronic opioid use as compared to those without. There are significant manometric pressure differences at the upper esophageal sphincter among chronic opioid users when compared to non-opioid users.
Related Concept Videos
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:11
Direct-Acting Cholinergic Agonists: Therapeutic Uses
 01:30
Indirect-Acting Cholinergic Agonists: Pharmacological Actions
At the neuromuscular junction, these agents work by inhibiting the breakdown of acetylcholine, allowing it to remain bound to the receptor and bind to nearby receptors. This process leads to repetitive firing of the endplate, causing muscle...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...