Related Experiment Video
Updated: Jun 10, 2026
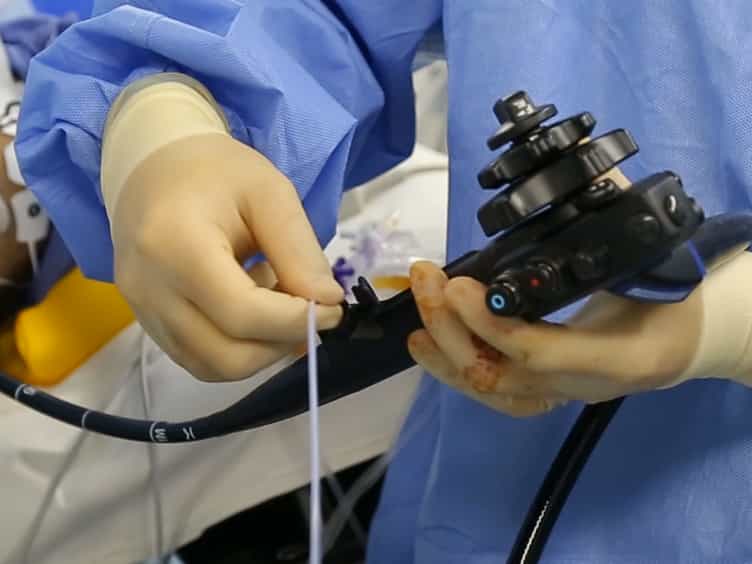

Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
Endoscopic full-thickness resection for early gastric cancer: a multicenter retrospective study from the National
Ke Han1, Xiaoliang Zhu2, Jiafeng Wang3
1Department of Endoscopy, General Hospital of Northern Theater Command, Shenyang, China.

Background:
Endoscopic full-thickness resection (EFTR) enables en bloc resection of the entire gastric wall along with high-quality pathological specimens, offering a minimally invasive and organ-preserving therapeutic option for EGC patients at higher risk of submucosal invasion or malignancy. This multicenter retrospective study aimed to evaluate the clinical feasibility and short-term oncological outcomes of EFTR for local resection of EGC, and to explore its potential role as a curative or salvage treatment strategy.
Methods:
A multicenter retrospective study was conducted via the National Early Gastrointestinal Cancer Cohort. Patients aged 18-80 years with histologically confirmed EGC (TisN0M0 or T1N0M0) and at least one high-risk feature of lymph node metastasis underwent EFTR or laparoscopic-assisted EFTR with regional lymphadenectomy. Primary outcomes evaluated were technical success (en bloc resection and R0 resection). Additional observations included tumor recurrence, adverse events, and overall procedural efficiency.
Results:
A total of 21 patients with 22 EGC lesions were enrolled from four tertiary hospitals. The mean patient age was 60.90 ± 9.72 years, with a male predominance (85.71%). Thirteen patients (61.90%) underwent sft-SMIR and 8 (38.10%) underwent laparoscopy-assisted EFTR with regional lymphadenectomy. All lesions were successfully resected en bloc with R0 margins. No serious intraoperative complications were observed. Postoperative complications included gastroparesis, anastomotic leak, and peritonitis. During a median follow-up period of 14 months, no cases of recurrence, metastasis, or death were observed.
Conclusions:
EFTR is a feasible, minimally invasive strategy for EGC, offering high technical success and R0 resection rates. For lesions with potential lymph node metastasis, limited nodal dissection preserves gastric function while maintaining oncological safety. Although sample size and follow-up were limited, this study underscores EFTR's potential to expand individualized EGC treatment, warranting further prospective research for long-term validation. Longer-term oncologic outcomes remain to be elucidated and standard practice.