Clinical frailty scale refines prognosis in acute pulmonary embolism beyond traditional risk scores
Related Experiment Video
Updated: Jan 16, 2026
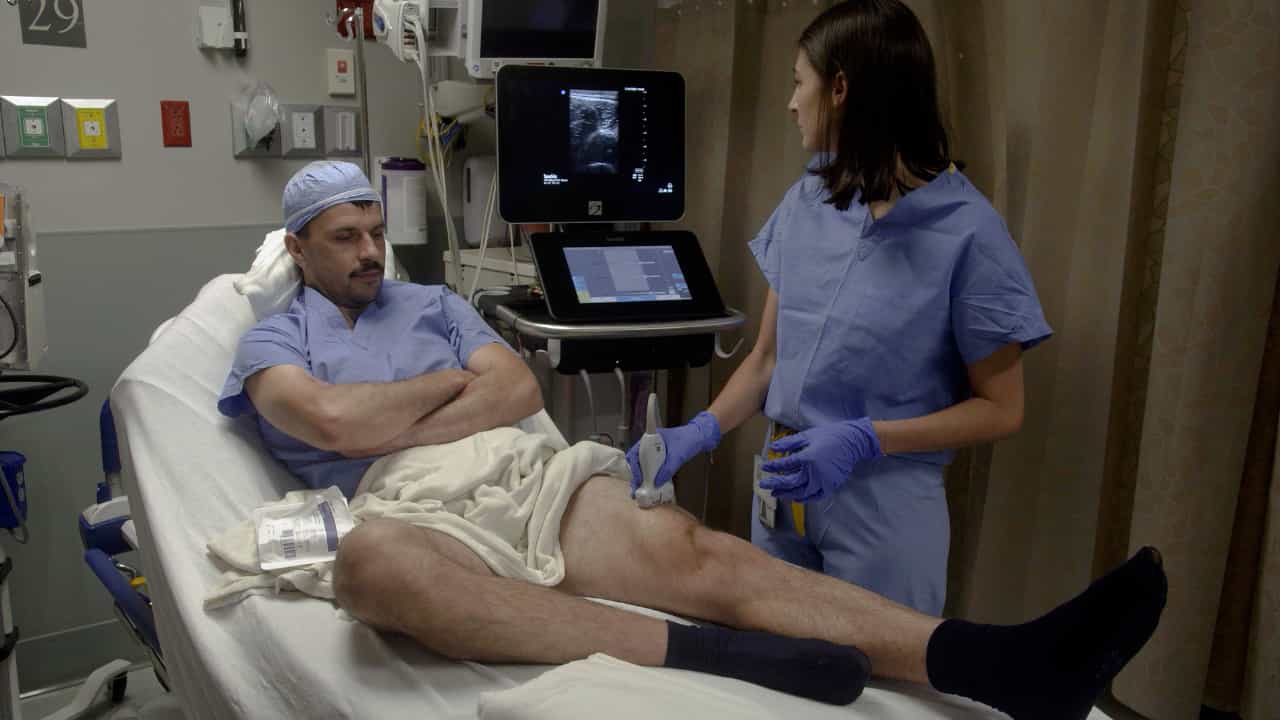
Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Jorge Sinclair De Frias1, Agostina Velo1, Abdul Rehman2
1Division of Pulmonary, Critical Care and Sleep Medicine, Department of Medicine, Icahn School of Medicine at Mount Sinai Health System, New York, USA.

Background:
The European Society of Cardiology (ESC) risk class and Pulmonary Embolism Severity Index (PESI) score can predict outcomes of patients with acute pulmonary embolism. However, whether the Clinical Frailty Scale (CFS) improves risk prediction in acute pulmonary embolism remains uncertain.
Methods:
We retrospectively reviewed patients aged ≥ 50 years with acute pulmonary embolism managed by the Pulmonary Embolism Response Team (PERT) at three hospitals within the Mount Sinai Health System (New York, NY) from January 2020 to June 2024. Frailty was defined as CFS > 4. Multivariable regression assessed association between outcomes (mortality, bleeding, 30-day readmission and hospital length of stay and risk scores (ESC, PESI and CFS).
Results:
Among 291 patients (median age: 69 years; 153 female), 99 (34.0%) were frail. Frailty was associated with higher odds of in-hospital mortality (odds ratio [OR]: 2.50), 30-day mortality (OR: 2.39), 30-day readmission (OR: 1.77) and longer length of stay (incidence rate ratio: 1.21). Incorporating CFS to models with ESC and PESI score improved prediction for 30-day mortality (net reclassification improvement [NRI]: 8.2%), 30-day major bleeding (NRI: 29.3%) and 30-day readmission (NRI: 29.3%).
Conclusion:
Frailty was independently associated with adverse outcomes in acute pulmonary embolism. Incorporating CFS improved the predictive performance of existing scores in patients with acute pulmonary embolism.


Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
Pulmonary Embolism I: Introduction
 01:27
Pulmonary Embolism III: Nursing Management
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Pneumonia III: Complications and Assessment