Related Experiment Video
Updated: May 12, 2026
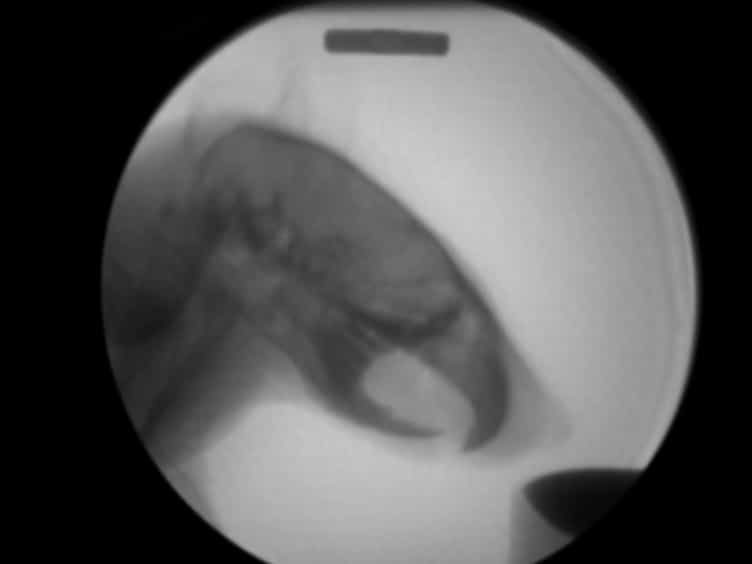
Adapting Human Videofluoroscopic Swallow Study Methods to Detect and Characterize Dysphagia in Murine Disease Models
Published on: March 1, 2015
Article Title: Impact of Dysphagia on Quality of Life in Machado-Joseph Disease
Joana Paz Mota1, Inês Tello Rodrigues2,3, Ana Filipa Ferreira4
1Serviço de Medicina Física e Reabilitação, Hospital do Divino Espírito Santo, Avenida D. Manuel I, Ponta Delgada, 9500-370, Portugal. joana.p.mota@azores.gov.pt.

Abstract:
Dysphagia is a frequent symptom of spinocerebellar ataxia type 3 (SCA3)/Machado-Joseph disease (MJD), being associated with alterations in nutritional intake and hydration, as well as an increased risk of aspiration pneumonia. This study aims to evaluate the impact of self-perceived dysphagia and its relationship with quality of life in SCA3/MJD mutation carriers. 41 SCA3/MJD mutation carriers from the Azorean cohort were recruited. The Swallowing Quality-of-Life Questionnaire (SWAL-QOL), the Eating Assessment Tool (EAT-10), the Functional Oral Intake Scale (FOIS), the Volume-Viscosity Swallow Test (V-VST), the Scale for the Assessment and Rating of Ataxia (SARA), the Inventory of Non-Ataxia Signs (INAS), and the Activities of Daily Living (ADL) were applied. Dysphagia was confirmed in 40% SCA3/MJD patients, whose SWAL-QOL was significantly decreased when compared to participants without dysphagia (p = 0.001). As expected, SCA3/MJD carriers with worse SWAL-QOL showed a high risk of dysphagia (p < 0.01), a worse functional oral intake of food and liquids (p < 0.01) and more severe ataxia (p < 0.01). Additionally, high severity of dysphagia reported on the INAS scale, (p < 0.01) and high frequency of swallowing disorders, perceived by SCA3/MJD carriers (p < 0.01) were observed in SCA3/MJD carriers with worse SWAL-QOL. Our findings confirm that dysphagia negatively impacts the quality of life of SCA3/MJD carriers, highlighting the need for permanent support by specialized healthcare professionals during disease progression. Additionally, we recommend that SCA3/MJD carriers with a score of 1 or higher on both the INAS dysphagia item and the ADL swallowing item be referred for specialized healthcare support in swallowing disorders.


Related Concept Videos
 01:20
Taste Buds and Receptors
 01:20
Gastrointestinal Motility Disorders
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:27
Esophageal Achalasia
 01:25
Gastroesophageal Reflux Disease
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications