Related Experiment Video
Updated: Jan 16, 2026

Application of End-to-end Anastomosis in Robotic Central Pancreatectomy
Published on: June 2, 2018
Robotic Pancreatoduodenectomy with Segmental Portomesenteric Venous Resection and Primary End-to-End Reconstruction:
Zhi Ven Fong1, Nabil Wasif2, Akash Kartik2
1Division of Oncologic and Endocrine Surgery, Department of Surgery, Mayo Clinic Arizona, Phoenix, AZ, USA. Fong.Zhi@mayo.edu.

Background:
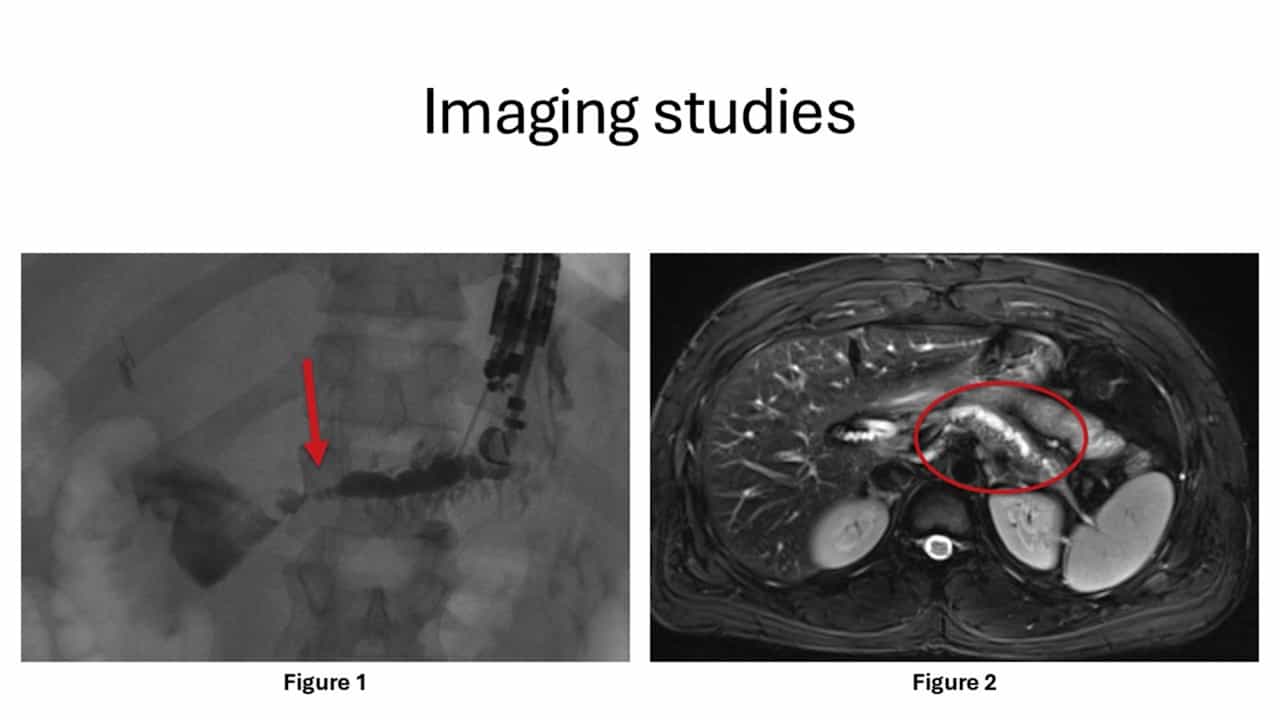
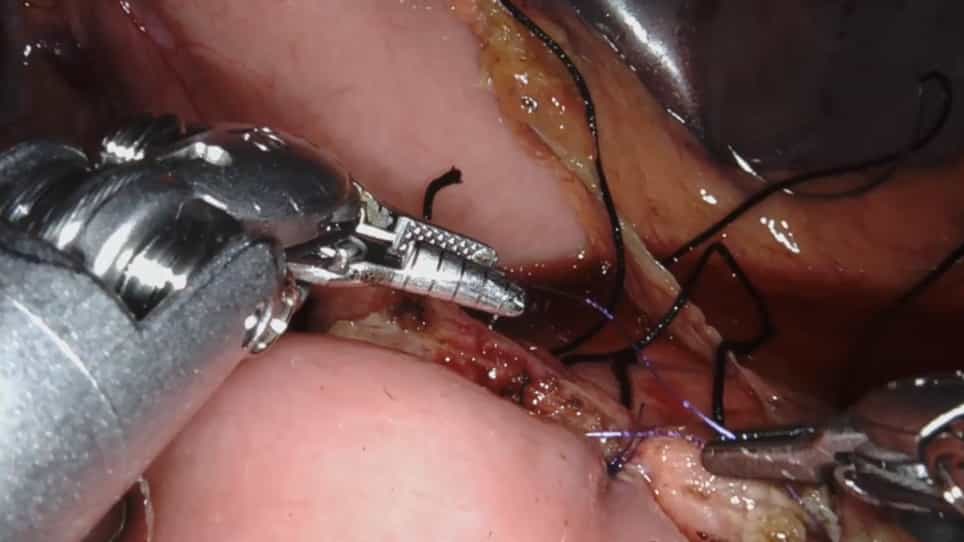
Robotic pancreatoduodenectomy (RPD) with portomesenteric venous (PMV) resection is a complex operation that can be performed as safely as the open approach at experienced centers.1,2 Patency rates vary with reconstruction techniques. The highest rate was observed in primary end-to-end reconstruction versus patch venoplasty or interposition graft.3 However, achieving a tension-free primary anastomosis can be challenging robotically. We demonstrate our approach to robotic PMV resection with primary end-to-end reconstruction, highlighting key steps that can facilitate a tension-free primary venous anastomosis robotically and facilitating an expeditious recovery.4,5 METHODS: A 78-year-old woman with an upfront resectable pancreatic ductal adenocarcinoma with progression after 2 months of gemcitabine with Abraxane but responded well to Chemoswitch to modified FOLFIRINOX therapy. Intraoperative findings demonstrated vein involvement that could not be separated safely. The portal vein was dissected distally into the hilum. The splenic and inferior mesenteric veins were divided to provide more laxity to the PMV. A segmental PMV resection was performed, and primary end-to-end anastomosis completed in a tension-free manner without the need for a graft.
Results:
The patient had an uncomplicated hospital course and was discharged on postoperative day 3. Pathology demonstrated a 1.7 cm poorly differentiated adenocarcinoma with two of 21 lymph nodes positive. All resection margins were negative, with the closest margin at the PMV groove with a 1.4-mm clearance.
Conclusions:
Robotic pancreatoduodenectomy with PMV resection and primary end-to-end reconstruction is feasible in a tension-free manner after adequate mobilization and division of the splenic and inferior mesenteric veins.