Related Experiment Video
Updated: Jan 16, 2026

The Creation of a Rat Model for Osteosarcopenia via Ovariectomy
Published on: February 21, 2025
High "sarcopenia index" reduce all-cause mortality in patients with acute myocardial infarction
Hui Pan1, C Yu Dong2, Z Cheng Yang3
1Department of Geriatric Medicine, Qilu Hospital of Shandong University, Key Laboratory of Cardiovascular Proteomics of Shandong Province, Qilu Hospital, Jinan, Shandong, 250012, China.

Insights
The Sarcopenia Index (Cr × eGFRcys) effectively predicts all-cause mortality in elderly acute myocardial infarction (AMI) patients. A higher Cr × eGFRcys indicates better survival outcomes, offering a valuable prognostic marker.
Area of Science:
- Cardiology
- Geriatrics
- Renal Medicine
Background:
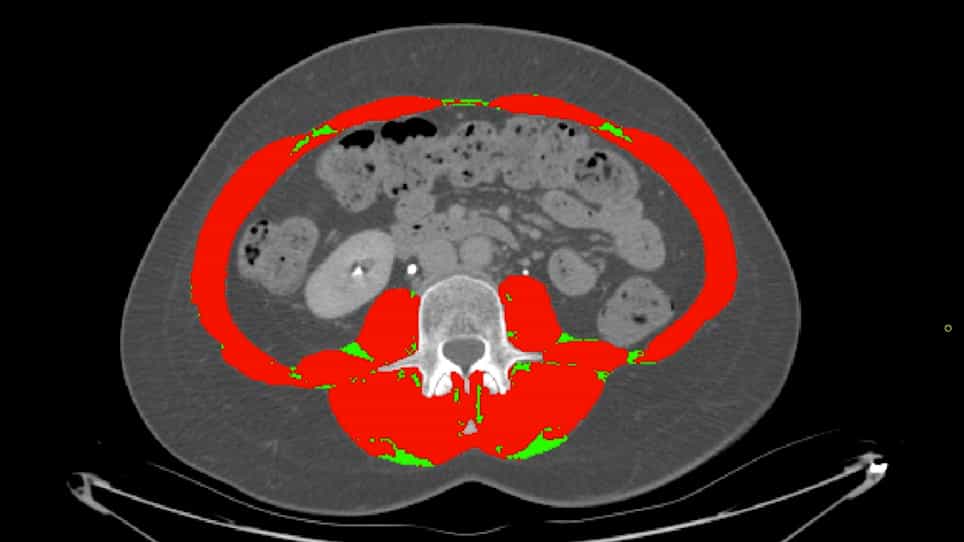
- The Sarcopenia Index (SI), calculated as the product of serum creatinine and cystatin C-based estimated glomerular filtration rate (Cr × eGFRcys), is a potential marker for sarcopenia.
- The predictive value of Cr × eGFRcys for all-cause mortality in elderly patients with acute myocardial infarction (AMI) remains uninvestigated.
Purpose of the Study:
- To investigate the association between Cr × eGFRcys and the risk of all-cause mortality in elderly patients diagnosed with AMI.
- To determine if Cr × eGFRcys can serve as an independent predictor of mortality in this patient population.
Main Methods:
- A retrospective cohort study analyzed 500 elderly (≥65 years) AMI patients.
- Patients were stratified into high and low Cr × eGFRcys groups based on ROC analysis.
- Kaplan-Meier curves and multivariable Cox proportional hazards models assessed survival and independent predictors of mortality.
Main Results:
- Patients in the high Cr × eGFRcys group exhibited significantly better survival rates (log-rank p < 0.0001).
- Incorporating Cr × eGFRcys improved the predictive accuracy of a baseline risk model for all-cause mortality, with significant enhancements in NRI, IDI, and C-index.
Conclusions:
- Cr × eGFRcys is significantly associated with all-cause mortality in elderly AMI patients.
- An optimal cut-off value of 53.56 for Cr × eGFRcys suggests its utility as a prognostic marker for all-cause mortality in this demographic.
Background:
The product of serum creatinine and cystatin C-based estimated glomerular filtration rate (hereinafter referred to as "Cr × eGFRcys"), serving as the formula for the Sarcopenia Index (SI), could be regarded as a representative marker for sarcopenia. However, no studies have investigated whether Cr × eGFRcys can predict all-cause mortality in elderly patients with acute myocardial infraction (AMI).
Aim:
To investigate the association between Cr × eGFRcys and all-cause mortality risk in elderly AMI patients.
Methods:
We conducted a retrospective cohort analysis of 500 elderly (≥65 years) AMI patients. Participants were stratified into high and low Cr × eGFRcys groups using the optimal cut-off determined by receiver operating characteristic (ROC) analysis, with all-cause mortality as the primary endpoint. Kaplan-Meier (hereinafter referred to as "K-M") survival curves assessed survival differences (log-rank test). Multivariable Cox proportional hazards models evaluated the independent association of Cr × eGFRcys (as continuous, categorical, or per-standard deviation increase) with mortality. The added predictive value beyond conventional risk factors was assessed through C-statistics, continuous net reclassification improvement (NRI), and integrated discrimination improvement (IDI).
Result:
Survival analysis revealed significantly better outcomes in the high Cr × eGFRcys group compared to the low group (log-rank p < 0.0001). Inclusion of Cr × eGFRcys significantly enhanced the predictive accuracy of the baseline risk model for all-cause mortality: NRI = 0.43 (95 % CI: 0.17-0.61, p < 0.01), IDI = 0.04 (95 % CI: 0.01-0.08, p = 0.02), and C-index = 0.93 (95 % CI: 0.90-0.96), all with p < 0.05.
Conclusion:
Cr × eGFRcys was significantly associated with all-cause mortality, and the optimal cut-off value for predicting all-cause mortality was 53.56, suggesting that Cr × eGFRcys may serve as a valid marker of all-cause mortality in elderly patients with AMI.

Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:30
Acute Coronary Syndrome I: Introduction
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Coronary Artery Disease I: Introduction
 01:26
Atherosclerosis III: Management