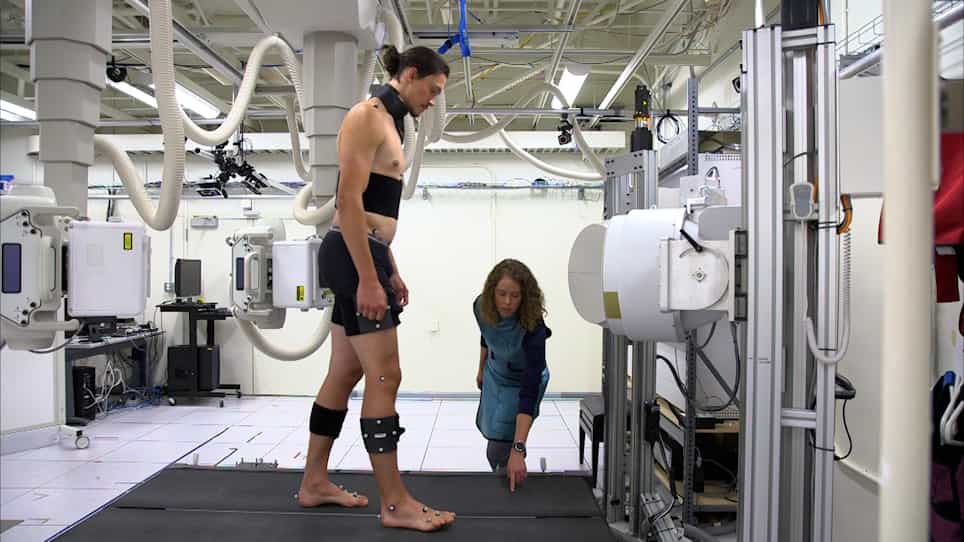
Related Experiment Video
Updated: Jan 15, 2026


The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Disparities in Patient-Reported Healthcare Affordability and Access Among Arthroplasty Patients in the All of Us
Michael J Farias1, Theodore Joaquin1, Gabriel Gonzalez1
1Warren Alpert Medical School, Brown University, Providence, Rhode Island.

Background:
While racial and ethnic disparities in postoperative outcomes for total hip and knee arthroplasty (THA/TKA) are well-documented, a significant gap remains in understanding patient-reported barriers to care. This study investigates racial and ethnic disparities in self-reported barriers to health care among THA/TKA patients.
Methods:
This cross-sectional study used data from the All of Us Research Program. Adult patients undergoing THA or TKA were identified using Current Procedural Terminology codes. Multivariable logistic regression was used to analyze 11 self-reported barriers across racial/ethnic groups (non-Hispanic White, Black, Hispanic, and Other). Odds ratios (ORs) were calculated from models after adjusting for age, sex, and/or neighborhood-level Community Deprivation Index (CDI).
Results:
A total of 4,419 patients were analyzed: 3,706 (83.9%) White, 325 (7.4%) Black, 235 (5.3%) Hispanic, and 153 (3.5%) Other. After adjusting for age, sex, and CDI, Black patients had significantly higher odds of delaying care because of cost of follow-up (OR 2.01, 95% confidence interval [CI] 1.26-3.21), general visits (OR 2.07, 95% CI 1.24-3.47), and co-pays (OR 2.31, 95% CI 1.44-3.71). Both Black (OR 1.99, 95% CI 1.32-2.98) and Hispanic (OR 1.79, 95% CI 1.13-2.82) patients had significantly higher odds of experiencing transportation-related delays.
Conclusion:
Significant racial and ethnic disparities in affordability and access persist among THA/TKA patients, even after controlling for neighborhood-level socioeconomic deprivation. Black and Hispanic patients experience multifaceted barriers, underscoring that interventions should address not only individual patient circumstances but also structural community-level factors to achieve equitable arthroplasty care.
Level Of Evidence:
Level III. See Instructions for Authors for a complete description of levels of evidence.