Related Experiment Video
Updated: Jul 26, 2026

Increasing Pulmonary Artery Pulsatile Flow Improves Hypoxic Pulmonary Hypertension in Piglets
Published on: May 11, 2015
Hemodynamic outcomes in patients undergoing bidirectional cavopulmonary connection with additional or antegrade
Kernfan Puthikitakawiwong1, Chodchanok Vijarnsorn1, Teerapong Tocharoenchok2
1Department of Pediatrics, Faculty of Medicine Siriraj Hospital, Mahidol University, Bangkok, Thailand.

Background:
The bidirectional cavopulmonary connection (BCPC) is a pivotal stage in the surgical palliation of single-ventricle patients. However, there is ongoing debate regarding the benefits and drawbacks of BCPC with additional or antegrade pulmonary blood flow (AAPBF) in optimizing the subsequent stage-total cavopulmonary connection (TCPC).
Objective:
To determine the influence of BCPC with AAPBF on pulmonary artery growth and hemodynamic outcomes.
Methods:
A retrospective review was conducted of 167 single-ventricle patients who underwent BCPC at Siriraj Hospital between 2006 and 2022. Patients were categorized into two groups based on AAPBF status: group 1 (with AAPBF, n = 44) and group 2 (without AAPBF, n = 123). Variables from pre-BCPC and pre-TCPC cardiac catheterization-including pulmonary artery growth, McGoon ratio, Nakata index, mean pulmonary arterial pressure (mPAP), ventricular end-diastolic pressure (EDP), and indexed pulmonary vascular resistance (PVRi)-were compared between groups. Pulmonary artery branch z-scores were analyzed and adjusted using analysis of covariance (ANCOVA). Survival rate, all-cause mortality, and incidence of atrioventricular valve regurgitation (AVVR) and pulmonary arteriovenous malformation (AVM) were also assessed.
Results:
Median ages at pre-BCPC assessment were 1.06 years (group 1) and 2.17 years (group 2), and at pre-TCPC assessment were 6.19 and 7.27 years, respectively. Median age at BCPC operation was similar between groups (1.58 vs. 1.51 years). Over a median follow-up of 64.33 months, group 1 showed significantly greater increases in right and left pulmonary artery size compared to group 2 (RPA: 3.27 vs. 1.6 mm (p = 0.019); LPA: 2.38 vs. 0.88 mm (p = 0.004)). The Nakata index increased in group 1 but decreased in group 2 (26.70 vs. -84.67 mm2/m2, p < 0.001). Z-scores confirmed significant growth in both pulmonary arteries when adjusted for body surface area (p < 0.001). No significant differences were found in pre-BCPC mPAP (16 vs. 15 mmHg, p = 0.38), EDP (12 vs. 12 mmHg, p = 0.584), or PVRi (1.77 vs. 2.03 WU m2, p = 0.890). Survival rates did not differ significantly between groups (p = 0.350).
Conclusions:
BCPC with AAPBF effectively promotes pulmonary artery growth without adversely affecting ventricular volume loading or pulmonary artery pressure. Further investigation into the development of arteriovenous malformations is recommended.
More Related Videos
Related Concept Videos
 01:19
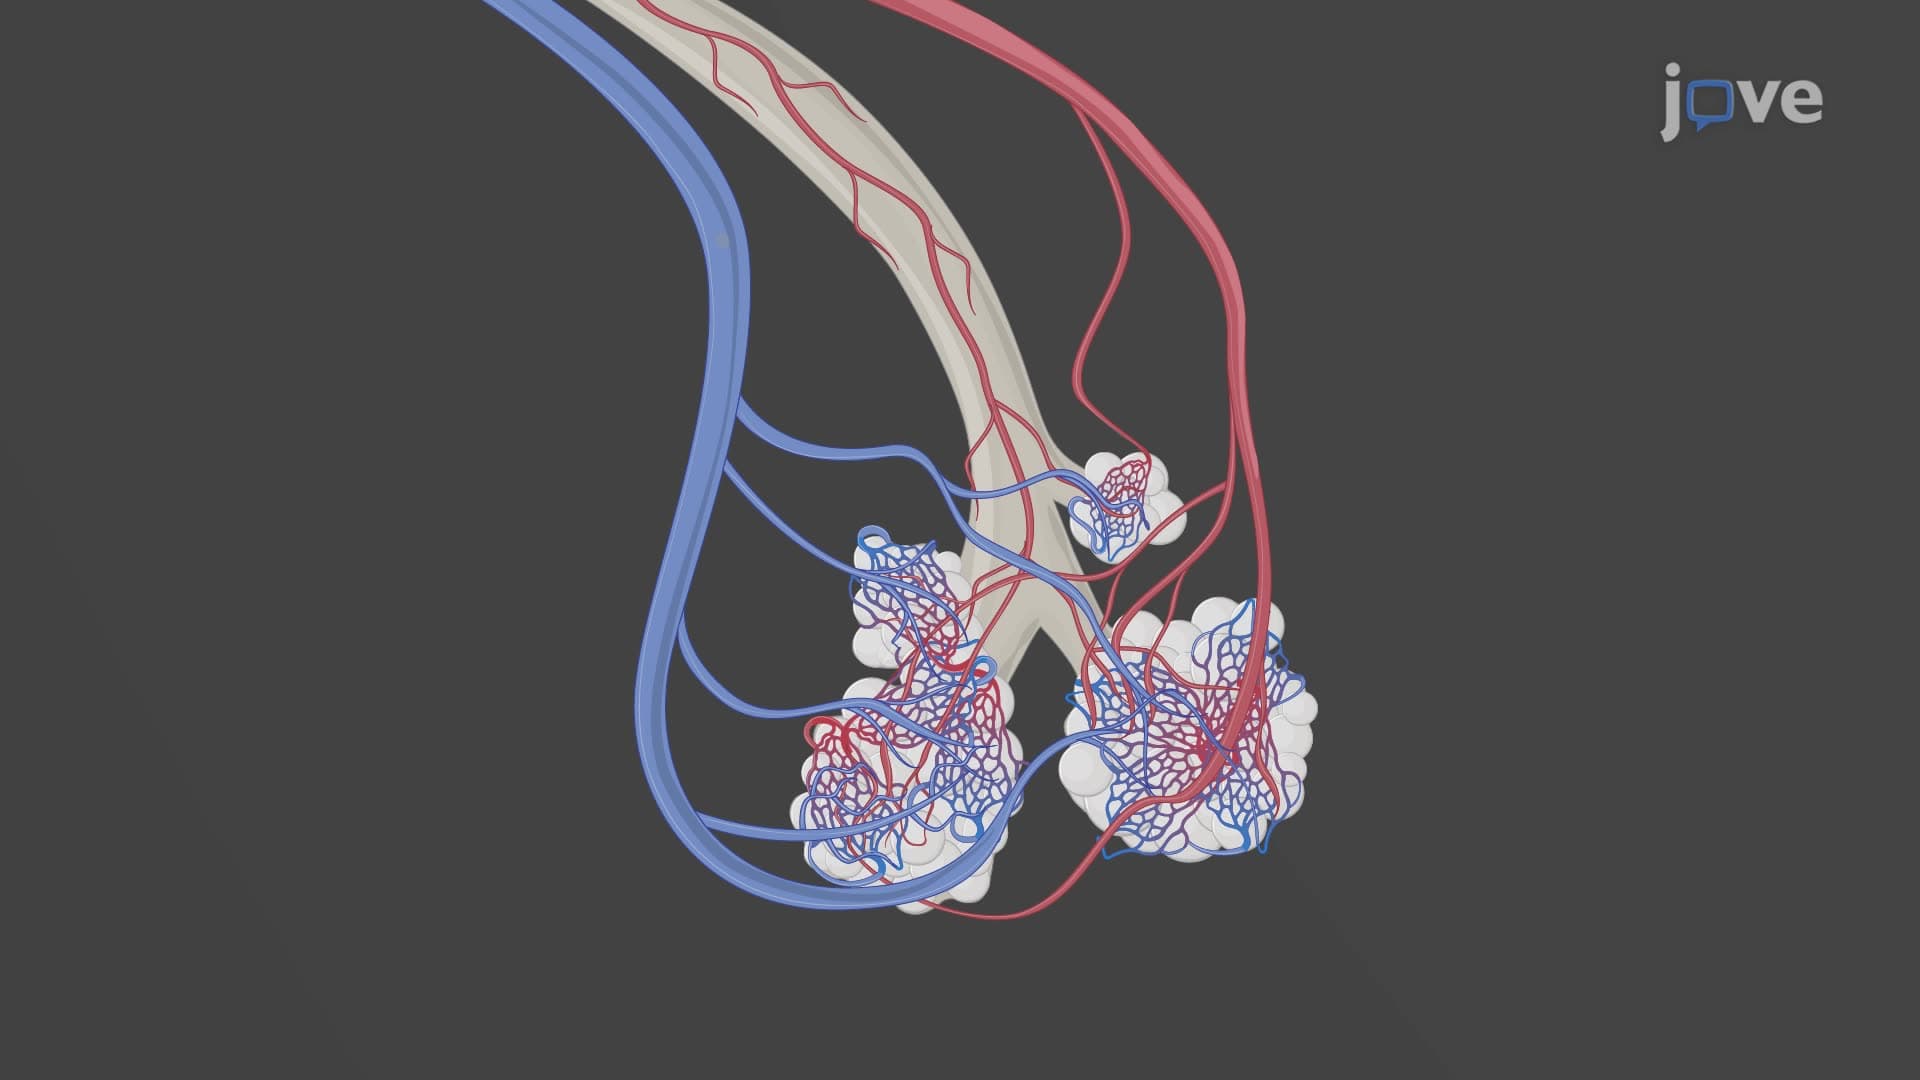
Overview of Pulmonary Circulation
The process begins with the right ventricle of the heart pumping deoxygenated blood into the pulmonary trunk. This large vessel extends about 5 centimeters before splitting into the left and right pulmonary arteries. These arteries...
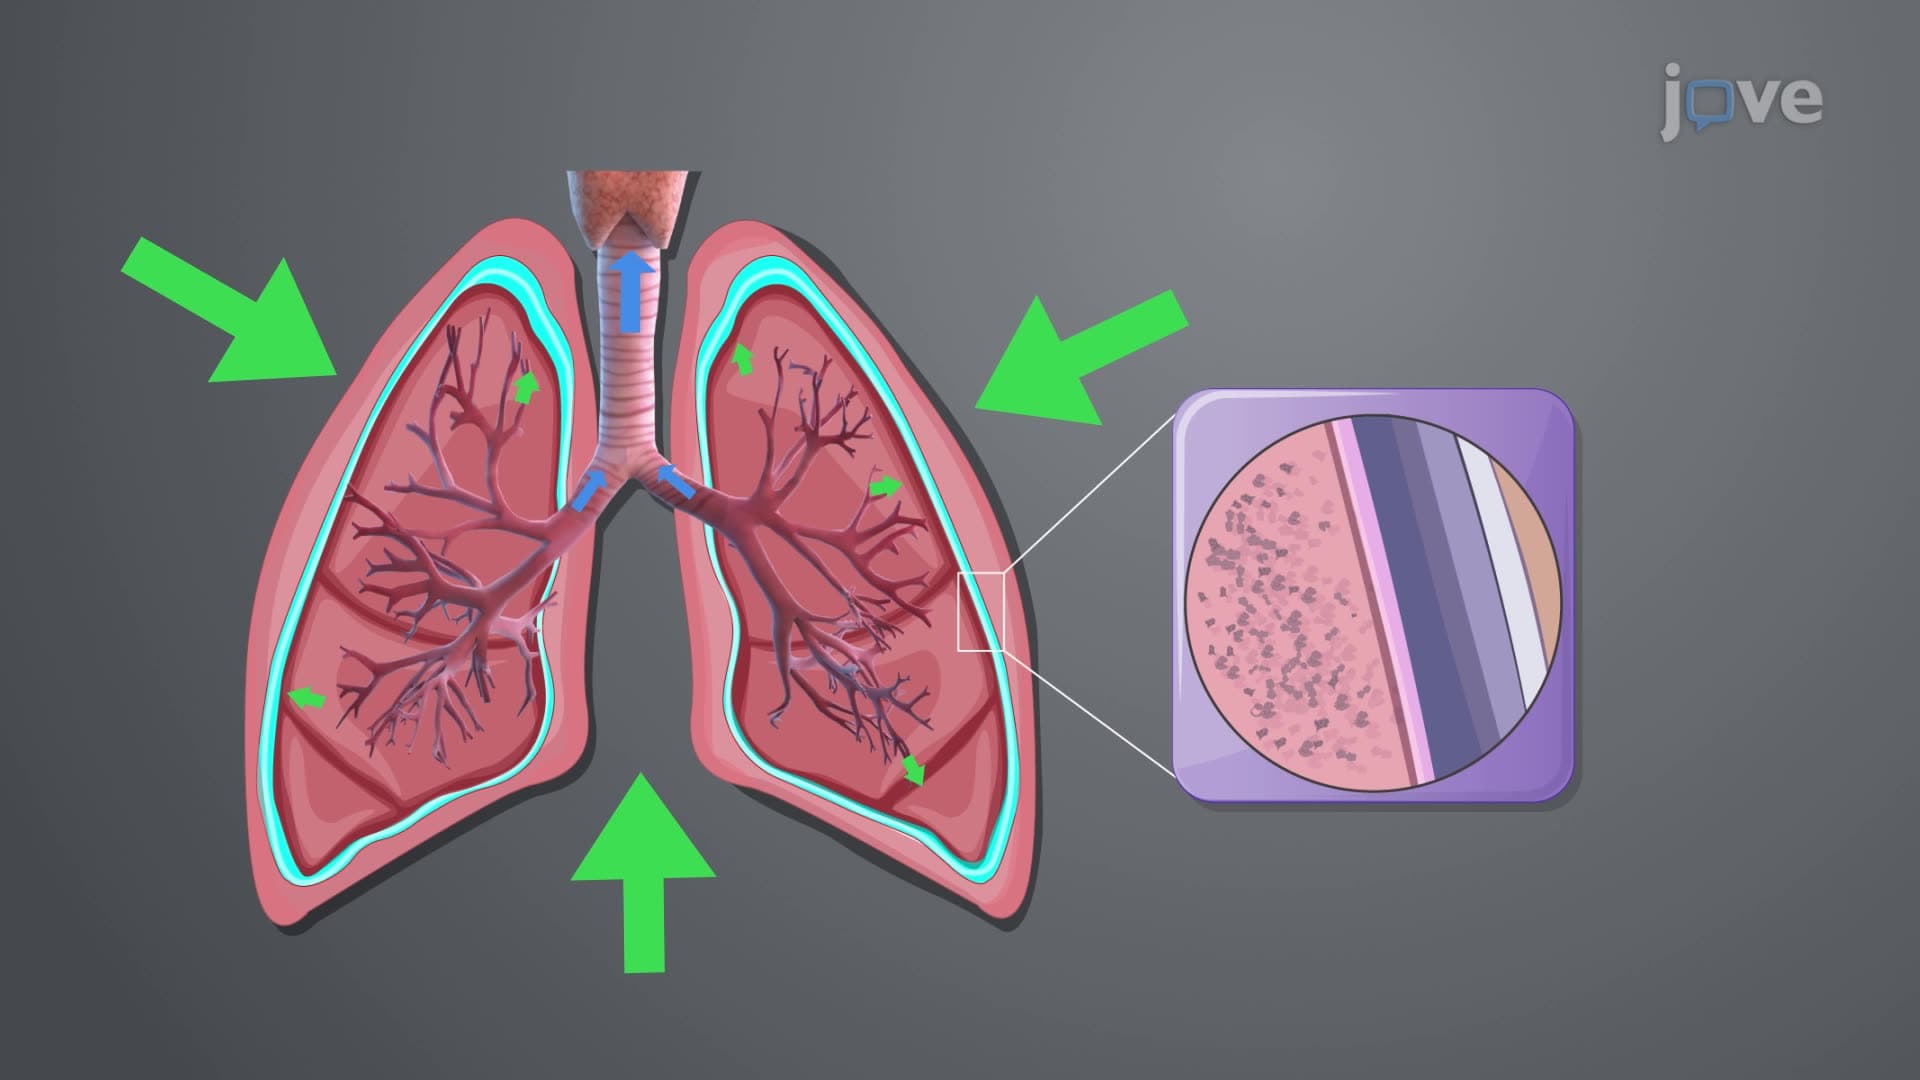 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:08
Pneumothorax II: Pathophysiology
 01:10
Atelectasis II: Pathophysiology