Related Experiment Video
Updated: Jan 15, 2026
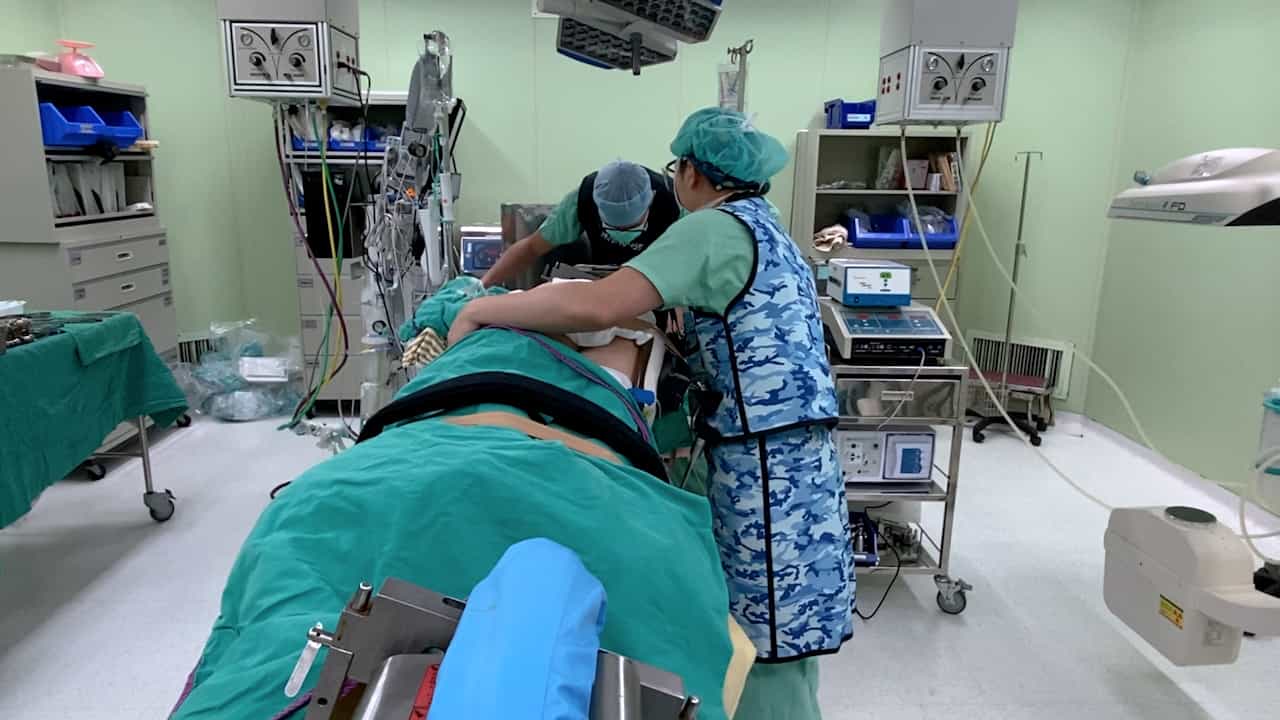

Prone Lateral Minimally Invasive Retropleural Corpectomy Using a Rotatable Radiolucent Jackson Table
Published on: July 3, 2025
Rhabdomyolysis After Tracheobronchoplasty: Incidence, Predictors, and Association With Postoperative Outcomes
Paolo de Angelis1, Jae Cho1, Alma V Burbano1
1Division of Thoracic Surgery and Interventional Pulmonology, Department of Surgery, Beth Israel Deaconess Medical Center, Boston, Massachusetts.

Introduction:
Prolonged intraoperative immobility during tracheobronchoplasty (TBP) can cause rhabdomyolysis. We investigated the incidence of rhabdomyolysis after TBP and its association with postoperative outcomes.
Methods:
We conducted a single-center review of TBP patients between 2008 and 2024. Patients were dichotomized by the severity of rhabdomyolysis. Outcomes included postoperative acute kidney injury (AKI), complications, readmissions, hospital length of stay, and disposition. The Fisher's exact test, Wilcoxon rank sum test, and stepwise logistic regression were used for analyses.
Results:
A total of 232 patients were included; 11 (4.7%) did not develop rhabdomyolysis. In total, 131 (56.4%) developed mild, 85 (36.6%) developed moderate, and 5 (2.1%) developed severe rhabdomyolysis. Patients with moderate/severe rhabdomyolysis had higher body mass index (BMI; 33.5 versus 32.3, P = 0.02), more frequently underwent open TBP (96.7% versus 71.8%, P < 0.01), and had longer operations (424 versus 406 min, P = 0.02). AKI was more prevalent in the moderate/severe group (18.9% versus 11%, P = 0.01). There were no differences in other complications, intensive care unit, and hospital length of stay, discharge disposition, and readmissions. Predictors of moderate/severe rhabdomyolysis included age (odds ratio [OR] 0.944, 95% confidence interval [CI] 0.914-0.974, P < 0.001), male sex (OR 2.907, 95% CI 1.372-6.161, P = 0.005), BMI (OR 1.080, 95% CI 1.022-1.140, P = 0.006), open approach (OR 54.014, 95% CI 10.579-275.771, P < 0.001), and operative time (OR 1.009, 95% CI 1.003-1.015, P = 0.001).
Conclusions:
Most TBP patients develop rhabdomyolysis; few develop severe cases. Moderate/severe rhabdomyolysis is linked to younger age, male sex, higher BMI, open approach, and longer operations. Despite higher incidence of AKI, complication rates are similar, likely due to timely recognition of high-risk patients.
More Related Videos
 04:43
Endotracheal Intubation via Tracheotomy and Subsequent Thoracotomy in Rats for Non-Survival Applications
Published on: March 15, 2024
 07:48
Intraoperative Video Consultation Following Bile Duct Transection Facilitates Direct OR Transfer for Robotic Hepaticojejunostomy at Tertiary Center
Published on: January 9, 2026
Related Concept Videos
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes: