
Diagnostic and Prognostic Utility of High-Sensitivity Troponin T (hs-TNT) and HEART Score in Risk Stratification of
Muhammad Tayyab1, Muhammad Farooq2, Muhammad Subhan Javed Butt3,4
1Trauma and Orthopaedics, Hayatabad Medical Complex Peshawar, Peshawar, PAK.

Insights
High-sensitivity troponin T (hs-TnT) and the HEART score effectively identify patients at risk of major adverse cardiac events (MACE). Combining hs-TnT with HEART scoring improves prediction accuracy for chest pain patients in the emergency department.
Area of Science:
- Cardiology
- Emergency Medicine
- Biomarkers
Background:
- Chest pain is a frequent emergency department presentation requiring prompt risk assessment.
- Early identification of patients at risk for major adverse cardiac events (MACE) is crucial.
Purpose of the Study:
- To assess the diagnostic and prognostic value of high-sensitivity troponin T (hs-TnT) and the HEART score.
- To predict 30- and 45-day MACE in chest pain patients.
Main Methods:
- Observational study of 864 adult patients with non-traumatic chest pain.
- Measured initial and serial hs-TnT levels; calculated HEART scores.
- Adjudicated 30- and 45-day MACE (myocardial infarction, revascularization, cardiac death).
Main Results:
- Elevated hs-TnT (>52 ng/L) and HEART score (≥7) were associated with significantly higher MACE risk.
- Combined hs-TnT and HEART score (≥4) improved MACE prediction sensitivity (84.2%) and NPV (97.2%).
- Combined model showed the highest AUC (0.86) for predicting MACE.
Conclusions:
- Hs-TnT and HEART score are valuable, complementary tools for early MACE risk stratification.
- Serial hs-TnT measurements and combined HEART scoring enhance predictive accuracy.
- Integration into ED protocols can improve patient management for chest pain.
Background:
Chest pain is a common emergency department (ED) presentation, and early risk stratification is essential to identify patients at risk of major adverse cardiac events (MACE).
Objective:
This study aimed to evaluate the diagnostic and prognostic utility of high-sensitivity troponin T (hs-TnT) and the HEART (history, ECG, age, risk factors, and troponin) score in predicting 30- and 45-day MACE among patients presenting with chest pain.
Methodology:
This descriptive observational study was conducted in two tertiary-care EDs in Pakistan (June 2021-May 2022). A total of 864 adult patients with non-traumatic chest pain were enrolled. Baseline demographics, clinical features, and risk factors were recorded. Initial hs-TnT levels were measured at presentation and serially at one and three hours. HEART scores were calculated at admission. MACE (myocardial infarction, revascularization, or cardiac death) within 30 and 45 days was defined according to standard criteria and adjudicated independently by blinded cardiologists. Associations between hs-TnT and outcomes were analyzed using chi-square tests for categorical variables and independent t-tests for continuous variables. Missing data were excluded from the analysis.
Results:
Among 864 patients (mean age 57.8 ± 13.1 years; 62% male), 144 (16.7%) developed 30-day MACE and 166 (19.2%) 45-day MACE. Patients with hs-TnT >52 ng/L had markedly higher MACE risk (30-day: 58.6%; 45-day: 63.8%) compared with those with hs-TnT <5 ng/L (30-day: 1.7%; 45-day: 1.9%, p<0.001). A HEART score ≥7 predicted 30-day MACE with 51.2% sensitivity, 87.3% specificity, a positive predictive value (PPV) of 28.2%, and a negative predictive value (NPV) of 94.6%. hs-TnT >52 ng/L alone showed 73.2% sensitivity, 79.4% specificity, PPV 35.7%, and NPV 95.9%. Combining hs-TnT >52 ng/L with HEART score ≥4 improved sensitivity to 84.2% and NPV to 97.2%. The area under the receiver operating characteristic (ROC) curve (AUC) for hs-TnT alone was 0.81 (95% CI: 0.77-0.85), for HEART score ≥7 was 0.76 (95% CI: 0.72-0.80), and for the combined model was 0.86 (95% CI: 0.83-0.89).
Conclusion:
Hs-TnT and the HEART score are effective, complementary tools for early identification of patients at risk of MACE. Serial hs-TnT measurement and combined use with HEART scoring significantly improve predictive accuracy, supporting their integration into ED risk stratification protocols.
More Related Videos
 06:16
Signal Acquisition, Score Interpretation, and Economics of a Non-Invasive Point-of-Care Test for Coronary Artery Disease
Published on: August 9, 2024
 07:40
Impact of High-intensity Interval Exercise and Moderate-Intensity Continuous Exercise on the Cardiac Troponin T Level at an Early Stage of Training
Published on: October 10, 2019
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:29
Angina III: Clinical Manifestations and Assessment
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:26
Exercise Stress Test
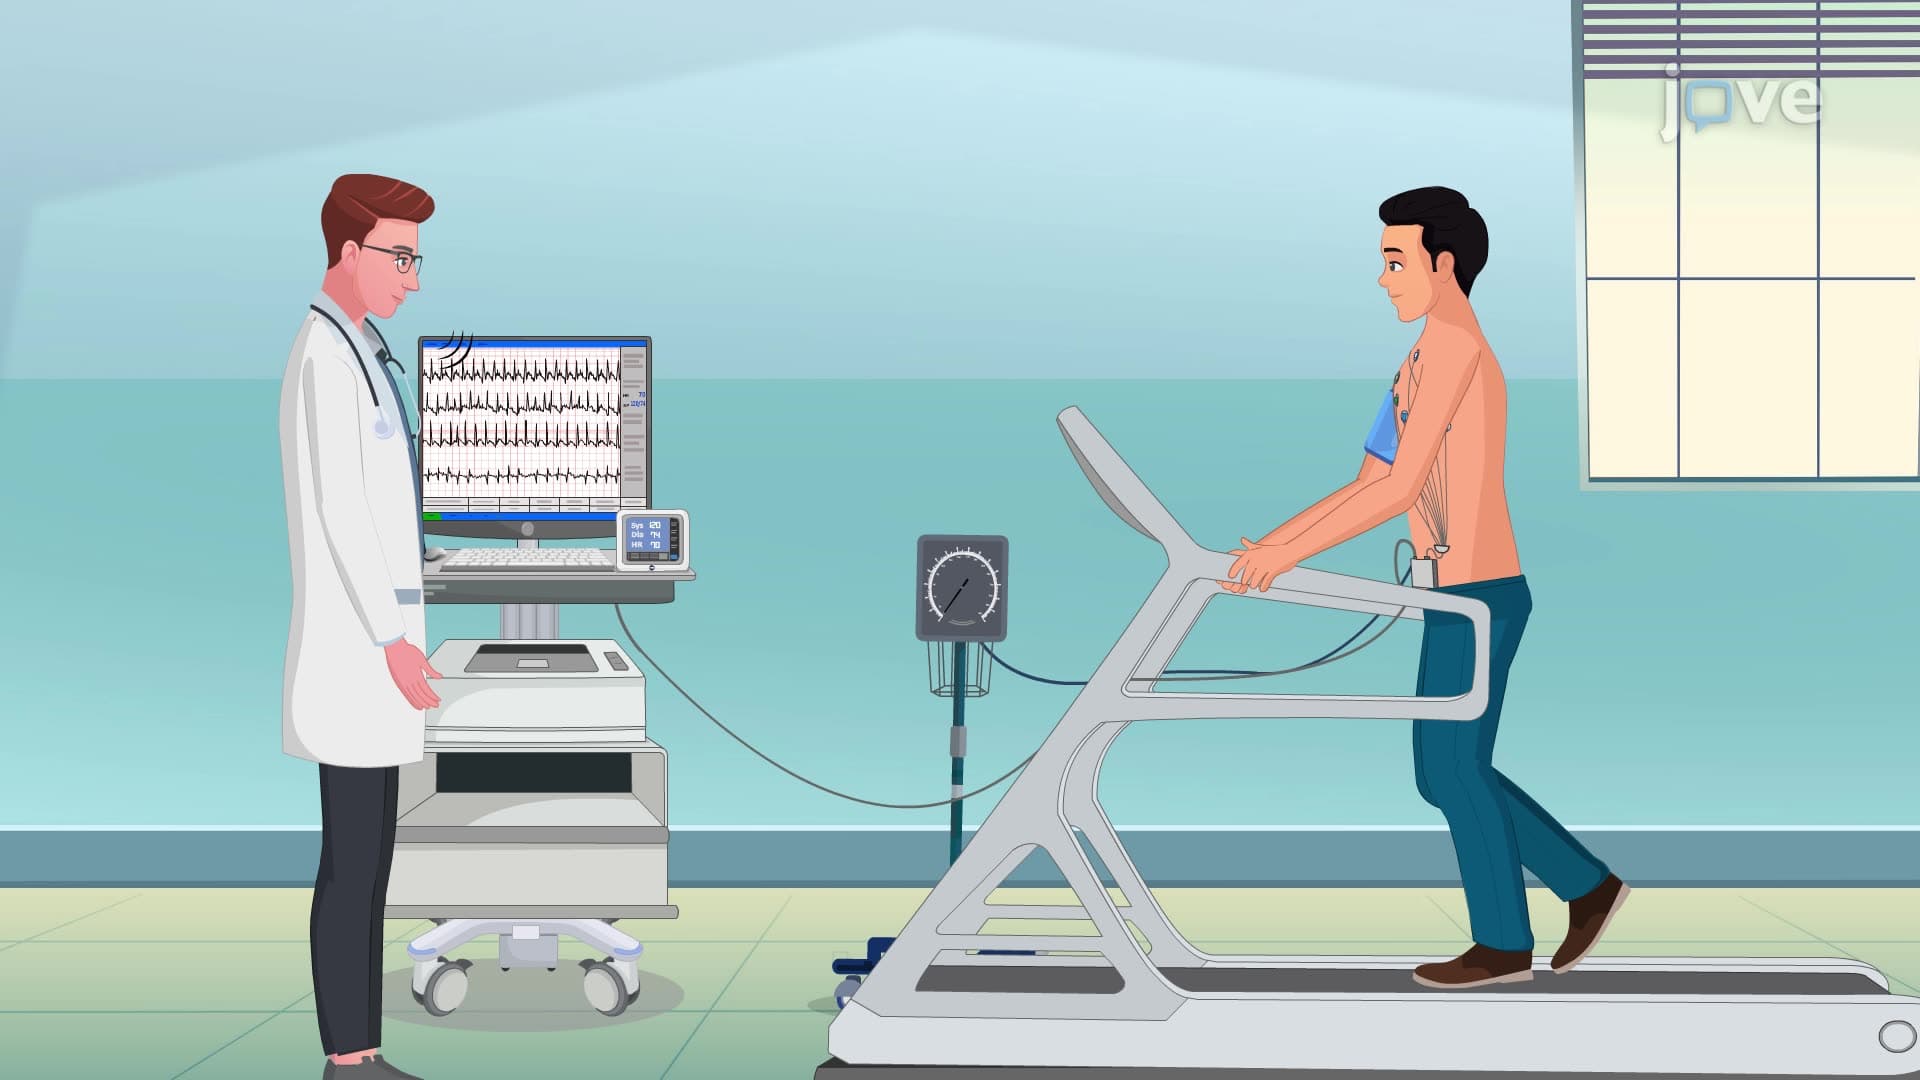
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes