Related Experiment Video
Updated: Jan 14, 2026
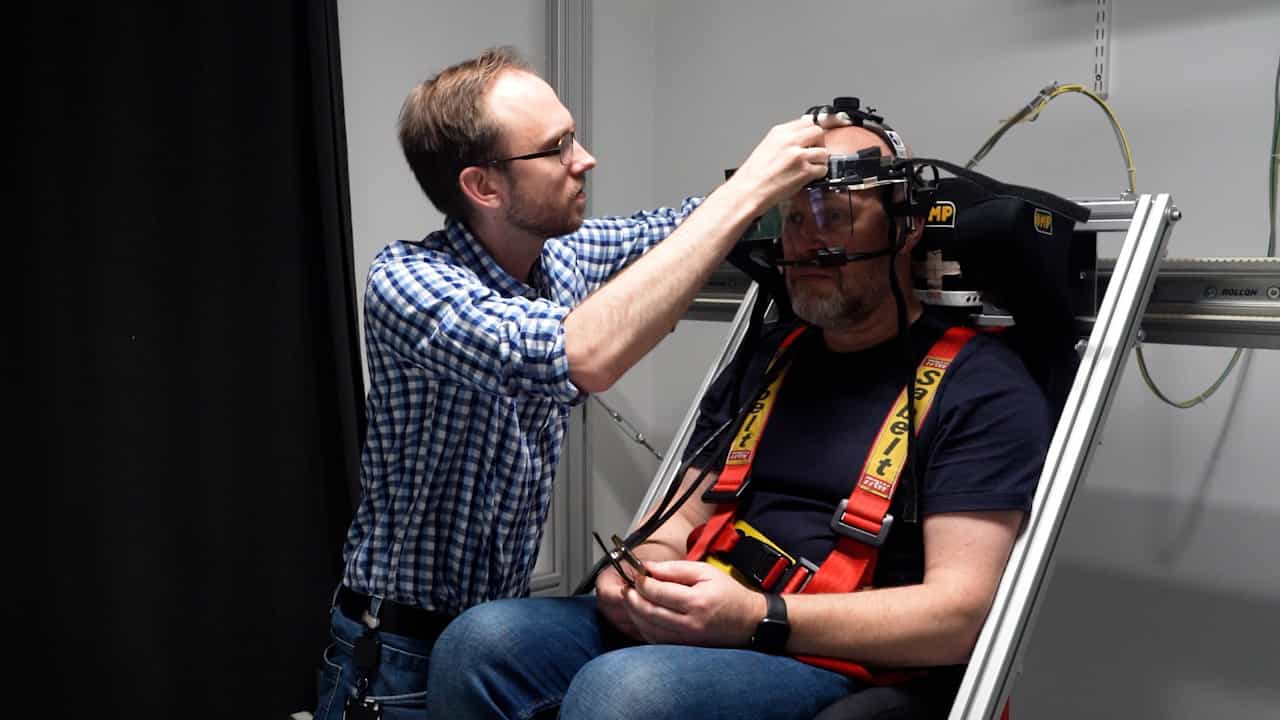
Using Eye-tracking to Assess the Relative Importance of Visual and Vestibular Input to Subcortical Motion Processing in the Roll Plane
Published on: August 22, 2025
Impact of head orientation and head movement in traditional manual diagnostics of benign paroxysmal positional
Malene Hentze1,2, Dan Dupont Hougaard1,2, Herman Kingma1,2
1Balance and Dizziness Centre, Department of Otorhinolaryngology, Head and Neck Surgery and Audiology, Aalborg University Hospital, Aalborg, Denmark.

Background:
Tradititional manual diagnostics of Benign Paroxysmal Positional Vertigo (BPPV) include Supine Roll test (SRT) and Dix-Hallpike test (DHT). However, the influence of head orientation and -movement on the diagnostic performance remains unclear.
Objective:
To assess how head orientation and -movement affect the diagnostic performance of the manual SRT and DHT.
Method:
This prospective, randomized, crossover study was conducted at a tertiary university hospital outpatient clinic. Participants with suspected BPPV (n = 198) underwent (in random order) both manual and mechanical rotation chair (MRC)-based (gold standard) SRT and DHT. BPPV diagnosis required characteristic positional nystagmus. Participants were grouped as: (1) true positives (manual and MRC diagnostics detection the same BPPV nystagmus) and (2) false negatives (manual: negative, MRC: positive). Primary outcome was difference in head orientation and -movement between groups. Secondary outcome was minimal head orientation required for BPPV nystagmus detection in the manual tests.
Results:
With manual SRT, yaw head angles were substantially below the 90° target [right: 70.3° (95% CI: 68.7, 71.9); left: -66.2° (95% CI: -67.7, -64.6)]. Manual SRT missed a large proportion of BPPV (right: 63.3%; left: 62.5%). A minimum yaw angle of approximately ±55° appeared necessary for BPPV nystagmus detection. For the pitch angle, overshooting the -60° target (to -75°) seemed more effective than undershooting. For manual DHT, yaw angles were closer to target ±45°, though left DHT was less accurate [right: 47.4° (95% CI: 46.2, 48.7); left: -33.3° (95% CI: -34.6, -31,9)]. BPPV detection rates were higher (right: 73.2%; left: 65.9%), with a tendency toward better outcome when yaw head angle was overshot, and pitch angle ranged from -100° to -120°. Head movements varied narrowly, making it challenging to determine minimal values. No differences in head movements were found between true positive and false negative groups.
Conclusion:
Manual DHT effectively detected posterior BPPV. In contrast, manual SRT (without truncal rotation), lacking sufficient yaw rotation, missed most lateral BPPV. Therefore, we recommend performing manual SRT with full-body rotation or upper trunk rotation. Future research is encouraged to define optimal head orientation and -movement in BPPV diagnostics.
Clinical Trial Registration:
ClinicalTrials.gov, identifier, NCT05846711.
More Related Videos
 08:57
Measuring the Influence of Magnetic Vestibular Stimulation on Nystagmus, Self-Motion Perception, and Cognitive Performance in a 7T MRT
Published on: March 3, 2023
 05:02
Using Unidirectional Rotations to Improve Vestibular System Asymmetry in Patients with Vestibular Dysfunction
Published on: August 30, 2019
