Related Experiment Video
Updated: Jan 14, 2026
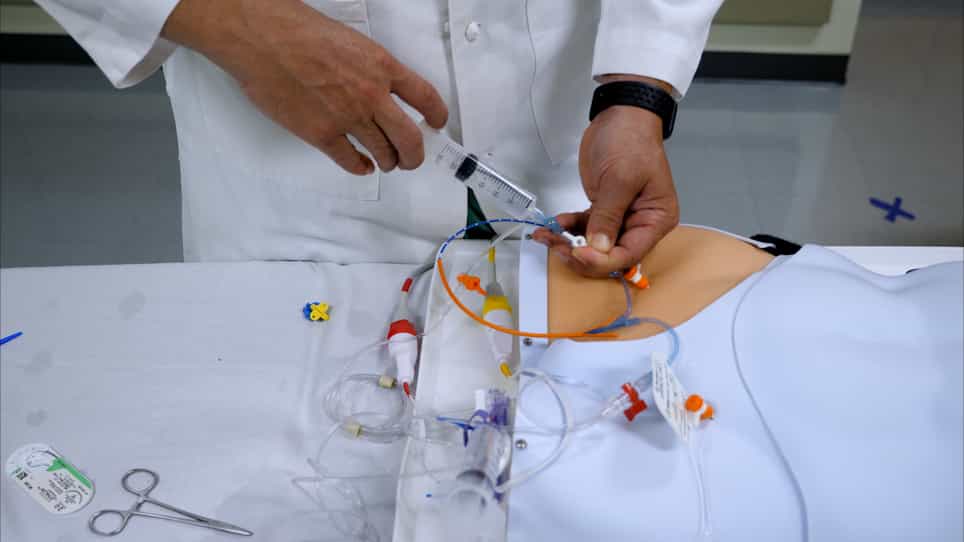
Complete and Partial Resuscitative Endovascular Balloon Occlusion of the Aorta for Hemorrhagic Shock
Published on: May 19, 2022
Five to excellence: The path to resuscitative endovascular balloon occlusion of the aorta proficiency
Ernest E Moore1, Jorge Lopez, Jessica Raley
1From the Department of Surgery (E.E.M.), Ernest E Moore Shock Trauma Center, Denver Health, Denver, Colorado; Department of Clinical Research (J.L., J.R.), Prytime Medical Devices, Boerne, Texas; Department of Surgery (C.S.), Mount Carmel Health System, Columbus, Ohio; Department of Surgery (K.M.), Loma Linda University Health, Loma Linda, California; Department of Surgery (M.R.), OhioHealth Grant Medical Center, Columbus, Ohio; Department of Surgery (J.N.), Morehouse School of Medicine, Atlanta, Georgia; Department of Surgery (A.B., J.R-N.), University of Toronto, Toronto, Ontario, Canada; Department of Surgery, Tulane School of Medicine Health Science Center (A.S.), New Orleans, Louisiana; Department of Surgery (M.V.), Northeast Georgia Medical Center, Gainesville, Georgia; and Department of Surgery (B.D.), Vanderbilt University Medical Center, Nashville, Tennessee.

Background:
Resuscitative endovascular balloon occlusion of the aorta (REBOA) is an emergent intervention for life-threatening hemorrhage, yet its clinical adoption is inconsistent, often because of technical challenges and variability in training. This study aims to characterize the learning curve associated with the pREBOA-PRO catheter Prytime Medical (Boerne, TX) at both the individual surgeon and institutional levels.
Methods:
Between March 2021 and June 2024, 377 REBOA procedures were performed at select Level I trauma centers as part of a quality improvement initiative. Structured debriefings were conducted within 48 hours postprocedure to assess technical challenges in three domains: femoral access, catheter removal, and sheath management. Learning curves were analyzed using cubic regression models for 24 surgeons (each with ≥8 cases; 251 cases total) and 8 institutions (each with ≥20 cases; 330 cases total).
Results:
Technical challenges were most frequent during the initial 5 cases for individual surgeons (63%) and the first 10 cases for institutions. Catheter removal emerged as the most common challenge (37% for individuals, 46% for institutions). Cubic regression models best fit the learning curves, demonstrating a marked reduction in technical issues by the fifth case for individuals and the tenth for institutions. Statistically significant differences in challenge rates were observed between early and later cases ( p < 0.01).
Conclusion:
Resuscitative endovascular balloon occlusion of the aorta demonstrates a relatively short learning curve, with proficiency typically achieved after 5 cases for individual surgeons and 10 for institutions. Focused training in vascular access, sheath management, and catheter removal is essential to optimize performance. These findings support the feasibility of rapid adoption of REBOA in high-volume centers and potentially in resource-limited settings, emphasizing the importance of structured training programs to enhance procedural proficiency and patient outcomes.
Level Of Evidence:
Therapeutic/Care Management; Level IV.

Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:26
Aneurysm III: Interprofessional Care
 01:21
Cardiopulmonary Resuscitation I: Adult