

The contribution of lower limbs to Pelvic Tilt: A baseline and postoperative full-body analysis
Marc Khalifé1, Renaud Lafage2, Bassel Diebo3
1Department of Orthopedic Surgery, Hôpital Européen Georges Pompidou, Paris, France; Université Paris-Cité, Paris, France; Department of Orthopedic Surgery, Northwell Health, Lenox Hill Hospital, New York, NY, USA.

Background:
Pelvic tilt (PT) has been a parameter of interest in biomechanics of spinal deformity for decades. It remains unclear how patients achieve different values of PT pre- and postoperatively.
Research Question:
This study aimed at assessing the relative contribution of hip extension, knee flexion and ankle extension to PT, factoring malalignment and hip osteoarthritis (OA).
Methods:
This retrospective study included Adult Spinal Deformity (ASD) patients with preoperative full-body radiographs from a multicenter database, with a sub-analysis of patients with complete 1-year follow-up (1yFU). Age and PI-adjusted normative PT (NormPT) and offset from norm (OffPT) were calculated, as for sacro-femoral angle (SFA), knee flexion angle (KA) and ankle angle (AA). Multivariate linear regression models controlling for age, frailty, severe hip OA, pelvic incidence (PI), SFA, and KA were used to predict PT at baseline, and offset from NormPT. Another model was generated to predict PT change.
Results:
600 patients at baseline and 336 with 1yFU were included. Mean age was 61 ± 15, 70.2 % were females and 40 % were revision cases. At baseline, regression analysis revealed that 0.9° increase in hip extension (SFA) and a 0.6° increase in knee flexion (KA) amounted to 1° increase in PT. Knee and ankle contribution to PT significantly increased for while hip extension decreased as TPA augmented (p < 0.001). Patients with low deformity compensated with hip extension, while knee flexion was the largest contributor of PT in high deformity patients: 70.7 % (44.7 - 111.9). Median contribution of knee flexion to PT was larger for patients who presented hip OA.
Significance:
This study demonstrated that PT is a phenomenon driven by extension of the hips and flexion of the knees and proposed values to predict PT from those two compensatory mechanisms. Magnitude of spinal deformity and hip OA alters the magnitude of SFA/KA contribution to PT.
More Related Videos
 08:40
Quantifying Arms and Legs Contributions during Repetitive Electrically-Assisted Sit-To-Stand Exercise in Paraplegics: A Pilot Study
Published on: November 11, 2022
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Related Concept Videos
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...
 01:26
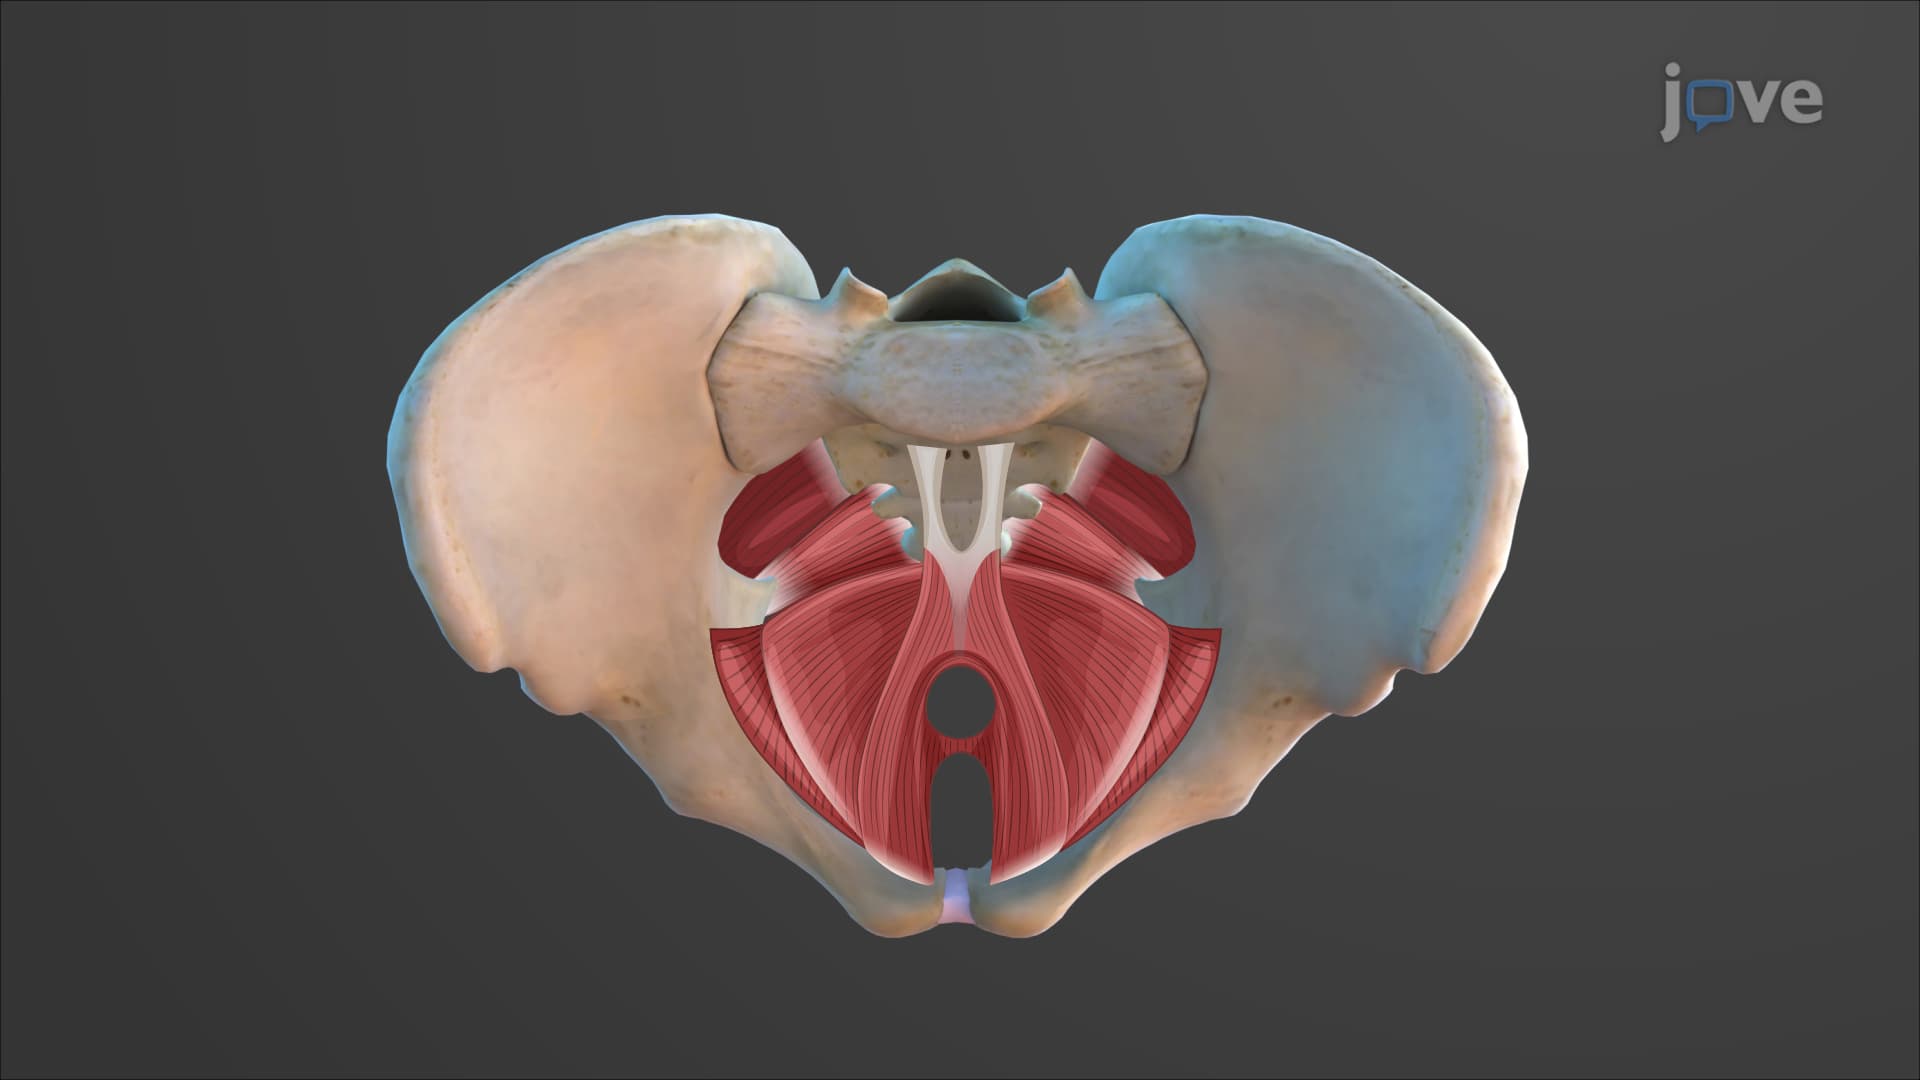
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...