Related Experiment Video
Updated: Sep 27, 2026
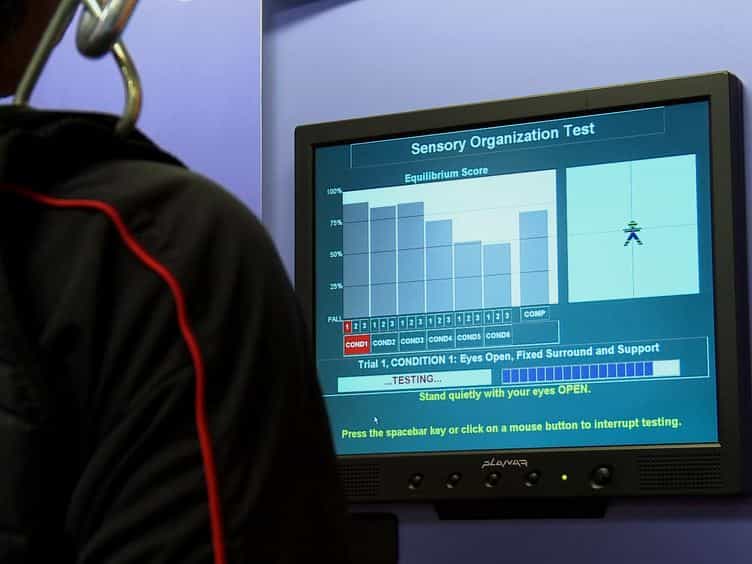

Computerized Dynamic Posturography for Postural Control Assessment in Patients with Intermittent Claudication
Published on: December 11, 2013
Prospective Evaluation of Peripheral Arterial Intervention Using Air Plethysmography
Anastasios G Potouridis1, Dimitrios A Chatzelas1, Apostolos G Pitoulias2
12nd Department of Surgery-Division of Vascular Surgery, "G. Gennimatas" General Hospital, Faculty of Medicine, Aristotle University of Thessaloniki, 54635 Thessaloniki, Greece.

Abstract:
Background and Objectives: Air plethysmography (APG), also referred to as pulse volume recording, provides a physiological assessment of lower-extremity perfusion, but its role in contemporary surveillance after peripheral arterial revascularization remains uncertain. This prospective study aimed to evaluate the ability of APG to monitor hemodynamic recovery and predict procedural failure after open and endovascular interventions. Materials and Methods: Consecutive patients undergoing infrainguinal revascularization for symptomatic peripheral arterial disease were prospectively enrolled and followed for 24 months. Standardized clinical assessment, ankle-brachial index, Duplex ultrasonography, and APG were performed preoperatively and at 1, 6, 12, and 24 months. Longitudinal hemodynamic changes, diagnostic accuracy for restenosis, patency, and predictors of procedural failure were analyzed. Results: A total of 120 patients were included, of whom 108 (90.0%) completed a 24-month follow-up. Mean pulse volume amplitude increased from 5.8 ± 2.3 mm preoperatively to 14.6 ± 4.1 mm at one month (p < 0.001) and remained significantly improved throughout follow-up. Systolic upstroke time decreased from 192 ± 31 to 128 ± 24 ms (p < 0.001), while waveform morphology also improved substantially. Longitudinal analysis demonstrated a significant effect of time (p < 0.001) and group-by-time interaction (p = 0.031). Among secondary outcomes, APG deterioration preceded fulfillment of the predefined Duplex criteria for significant restenosis in 26 of 34 failures, with a mean observed interval of 3.8 ± 1.2 months. A ≥25% reduction in pulse volume amplitude showed good discrimination for restenosis, while APG deterioration was independently associated with procedural failure (HR = 2.80, 95% CI 1.65-5.37; p < 0.001). Conclusions: APG is a reproducible, non-invasive surveillance adjunct that objectively reflects hemodynamic recovery and may identify physiological deterioration before fulfillment of predefined Duplex criteria for significant restenosis. These findings support further evaluation of APG as a complementary physiological modality within structured surveillance following lower-extremity revascularization.


Related Concept Videos
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:27
Peripheral Artery Disease III: Interprofessional Care
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:30
Peripheral Artery Disease I: Introduction